
Community Acquired Pneumonia: 8 Essential ATS/IDSA Rules
Clinical Practice Update — Severity Triage, Antibiotic Selection, MRSA/Pseudomonas Coverage, Steroids, and Duration in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based management of community acquired pneumonia in immunocompetent adults
- Target Audience
- Internists, emergency physicians, hospitalists, intensivists, residents
- Setting
- Primary care, emergency department, hospital inpatient, ICU
- Source Evidence
- •ATS/IDSA 2019 Guideline on Community-Acquired Pneumonia
- •BTS/NICE Guidelines on Community-Acquired Pneumonia (2019)
- •CAPE COD Trial — Hydrocortisone in Severe CAP (NEJM, 2023)
- •El Moussaoui — Short vs Longer Duration Antibiotics (BMJ, 2006)
- •ESCAPe Trial — Methylprednisolone in Severe CAP (JAMA IM, 2022)
Key Clinical Takeaways
Effective management of community acquired pneumonia comes down to three sequential decisions: stratify severity, pick the right empiric antibiotic, and decide when to stop. The ATS/IDSA 2019 framework organises these decisions around site of care and pathogen risk, with the CAPE COD trial adding a role for corticosteroids in severe CAP. The points below translate this into actionable rules.
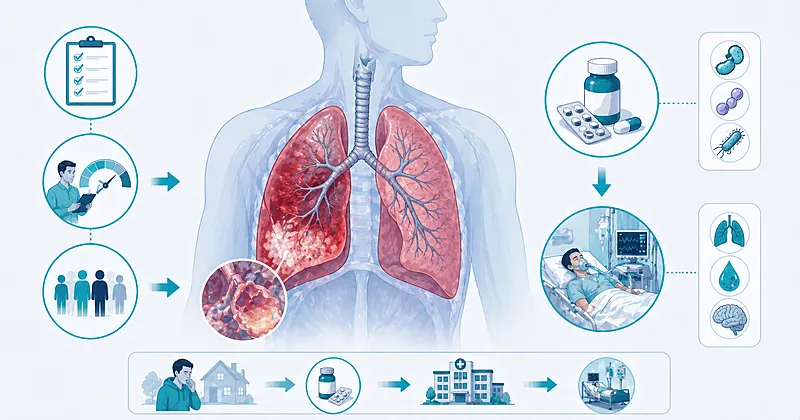
- 1Use CURB-65 plus clinical judgement for severity triage; apply the ATS/IDSA minor-criteria set to identify severe CAP needing ICU care → Severity
- 2Start amoxicillin or doxycycline for healthy outpatients; escalate to combination therapy if comorbidities → Antibiotics
- 3Give a beta-lactam plus a macrolide (or respiratory fluoroquinolone alone) to inpatients with non-severe CAP → Antibiotics
- 4Add MRSA or Pseudomonas coverage only when specific local risk factors are present — not routinely → MRSA/Pseudomonas
- 5Abandon the term “healthcare-associated pneumonia” — rely on individual pathogen risk factors instead → MRSA/Pseudomonas
- 6Give hydrocortisone 200 mg/day for 4–7 days in ICU-level severe CAP — CAPE COD changed the evidence base → Steroids
- 7Stop antibiotics after 5 days if the patient is clinically stable and afebrile for 48–72 hours → Duration
- 8Extend to 7 days (or longer) only when MRSA, Pseudomonas, or complicated infection are documented → Duration
- 9Do not order routine follow-up chest imaging in patients who recover clinically → Monitoring
- 10Switch from IV to oral antibiotics within 48–72 hours of clinical stability → Monitoring
Severity Triage in Community Acquired Pneumonia
Severity assessment is the gateway decision in community acquired pneumonia because it determines site of care, empiric coverage, and intensity of monitoring. ATS/IDSA uses a three-tier framework (outpatient, inpatient non-severe, inpatient severe), with severe CAP defined by one major criterion or three minor criteria. Clinical judgement, not a score alone, drives the final disposition.
Calculate CURB-65 (or PSI where available) and combine the result with oxygenation, comorbidities, and social circumstances. Scores are aids, not substitutes for clinical judgement.
Strong Rec High Evidence ATS/IDSA 2019 BTS/NICE 2019Apply the ATS/IDSA minor-criteria checklist (respiratory rate ≥30, PaO₂/FiO₂ ≤250, multilobar infiltrates, confusion, BUN ≥20, WBC <4000, platelets <100,000, hypothermia, hypotension needing fluids) in every admitted patient. Three or more criteria define severe CAP.
Strong Rec Moderate Evidence ATS/IDSA 2019Admit to ICU any patient with mechanical ventilation or septic shock requiring vasopressors (major criteria) — either alone defines severe CAP regardless of the minor count.
Strong Rec High Evidence ATS/IDSA 2019Do not use procalcitonin to decide whether to start antibiotics in community acquired pneumonia. Once the clinical and radiographic diagnosis is made, treat empirically regardless of procalcitonin value.
Against Moderate Evidence ATS/IDSA 2019Severity Tiers and Site of Care at a Glance
| Severity Tier | Defining Features | Typical CURB-65 | Site of Care | Key Action |
|---|---|---|---|---|
| Non-severe outpatient | No hypoxia, no sepsis, few comorbidities | 0–1 | Home | Oral amoxicillin or doxycycline; review at 48–72h |
| Non-severe inpatient | Needs supplemental oxygen or hemodynamic monitoring; fewer than 3 minor criteria | 2 | General ward | Beta-lactam + macrolide or respiratory fluoroquinolone |
| Severe (ICU) | 1 major or ≥3 minor ATS/IDSA criteria | ≥3 (often) | ICU | Combination antibiotics + consider hydrocortisone per CAPE COD |
| Complicated (any tier) | Empyema, lung abscess, necrotising pneumonia | Variable | Inpatient ± ICU | Extended duration + drainage consultation |
Antibiotic Selection for Community Acquired Pneumonia
Empiric antibiotic choice in community acquired pneumonia is driven by site of care, comorbidities, allergy history, and local resistance patterns. ATS/IDSA 2019 broke cleanly with the old CAP/HCAP dichotomy and now stratifies by pathogen risk at the individual level. For most patients, Streptococcus pneumoniae, Haemophilus influenzae, Mycoplasma, Chlamydia, and respiratory viruses remain the dominant targets.
Prescribe amoxicillin 1 g three times daily or doxycycline 100 mg twice daily as first-line for otherwise healthy adult outpatients without comorbidities. Macrolide monotherapy is acceptable only where local pneumococcal resistance to macrolides is under 25%.
Strong Rec Moderate Evidence ATS/IDSA 2019For outpatients with significant comorbidities (chronic heart, lung, liver, or renal disease; diabetes; alcohol use disorder; immunosuppression), prescribe amoxicillin-clavulanate (or an oral cephalosporin) plus a macrolide or doxycycline, or respiratory fluoroquinolone monotherapy (levofloxacin 750 mg daily or moxifloxacin 400 mg daily).
Strong Rec Moderate Evidence ATS/IDSA 2019For hospitalised adults with non-severe community acquired pneumonia, start a beta-lactam (ceftriaxone, ceftaroline, ampicillin-sulbactam, or ertapenem) plus a macrolide (azithromycin or clarithromycin). Respiratory fluoroquinolone monotherapy is an acceptable alternative.
Strong Rec Moderate Evidence ATS/IDSA 2019For ICU-level severe CAP, combine a beta-lactam with either a macrolide or a respiratory fluoroquinolone. Macrolide-containing regimens are associated with better outcomes in several observational datasets.
Strong Rec Moderate Evidence ATS/IDSA 2019Start antibiotics within 4 hours of arrival for hospitalised patients, and within 1 hour if septic shock is present. Do not delay empiric therapy to obtain microbiological samples.
Strong Rec High Evidence ATS/IDSA 2019 SSC 2021Empiric Regimens by Patient Profile
| Patient Profile | Preferred Regimen | Alternative | Practical Tips |
|---|---|---|---|
| Healthy outpatient | Amoxicillin 1 g TID × 5 days | Doxycycline 100 mg BID | Avoid macrolide monotherapy where resistance >25% |
| Outpatient with comorbidities | Amox-clav 875/125 BID + azithromycin 500 mg daily | Levofloxacin 750 mg daily | Reserve fluoroquinolones for allergy or intolerance |
| Inpatient, non-severe | Ceftriaxone 1–2 g IV daily + azithromycin 500 mg IV daily | Levofloxacin 750 mg IV/PO daily | Switch to oral within 48–72h of stability |
| Inpatient, severe (ICU) | Ceftriaxone 2 g IV daily + azithromycin 500 mg IV daily | Ceftriaxone + levofloxacin | Consider hydrocortisone 200 mg/day; assess MRSA/Pseudomonas risk |
| Beta-lactam allergy (non-severe) | Doxycycline + macrolide, or respiratory fluoroquinolone | Aztreonam + macrolide (if cephalosporin also excluded) | Most “penicillin allergy” labels can be safely delabelled |
| Pregnancy | Amoxicillin + azithromycin | Ceftriaxone + azithromycin | Avoid doxycycline and fluoroquinolones |
MRSA and Pseudomonas Coverage
ATS/IDSA 2019 retired the “healthcare-associated pneumonia” category. Empiric MRSA or Pseudomonas coverage is now added only when a patient has specific individual risk factors, not simply because they have had recent hospital contact. This shift has reduced over-treatment without increasing mortality.
Add empiric MRSA coverage (vancomycin 15–20 mg/kg IV q8–12h or linezolid 600 mg IV q12h) only when the patient has prior respiratory isolation of MRSA, recent hospitalisation with IV antibiotics within 90 days, or a locally validated MRSA risk marker.
Strong Rec Moderate Evidence ATS/IDSA 2019Add antipseudomonal coverage (piperacillin-tazobactam, cefepime, ceftazidime, imipenem, or meropenem) only when the patient has prior respiratory isolation of Pseudomonas, structural lung disease (bronchiectasis, advanced COPD), or recent hospitalisation with IV antibiotics.
Strong Rec Moderate Evidence ATS/IDSA 2019Obtain blood cultures, sputum Gram stain and culture, urinary pneumococcal and Legionella antigens, and nasopharyngeal PCR for influenza in patients with severe CAP or documented MRSA/Pseudomonas risk — these tests shape de-escalation.
Strong Rec Moderate Evidence ATS/IDSA 2019De-escalate broad-spectrum therapy at 48 hours if cultures do not identify MRSA or Pseudomonas and the patient is improving. Continuing unnecessary coverage drives resistance, C. difficile, and drug toxicity.
Strong Rec High Evidence ATS/IDSA 2019Adjunctive Corticosteroids in Severe CAP
The role of steroids in community acquired pneumonia shifted meaningfully with the CAPE COD trial in 2023. Hydrocortisone 200 mg/day reduced 28-day mortality in ICU-admitted severe CAP patients without influenza. The evidence does not extend to non-severe CAP, where steroids remain not routinely indicated.
Give hydrocortisone 200 mg IV daily for 4–7 days (then taper over a further 4–7 days) in patients admitted to ICU with severe CAP, based on the CAPE COD trial. Avoid in influenza pneumonia pending further data.
Moderate Rec Moderate Evidence CAPE COD 2023Do not use corticosteroids in non-severe CAP, whether outpatient or on the general ward. ATS/IDSA explicitly recommended against routine steroids in this population, and ESCAPe found no mortality benefit of methylprednisolone in severe CAP outside the ICU.
Against Moderate Evidence ATS/IDSA 2019 ESCAPe 2022Monitor for hyperglycaemia, secondary infection, and neuropsychiatric effects if corticosteroids are given. Screen glucose at least every 6 hours during the infusion period.
Strong Rec Low Evidence CAPE COD 2023Duration of Therapy
Shorter is better for most adults with community acquired pneumonia. Randomised trials and meta-analyses consistently show non-inferiority of 5-day courses compared with 7–10 days when the patient is clinically stable. Extension beyond 5 days should be driven by specific pathogens or complications, not by habit.
Treat for a minimum of 5 days. Stop antibiotics once the patient has reached clinical stability (afebrile 48–72 hours, stable vitals, eating, breathing comfortably on room air or baseline oxygen).
Strong Rec High Evidence ATS/IDSA 2019 BTS/NICE 2019Extend to 7 days when MRSA or Pseudomonas is documented, and for 7–21 days when lung abscess, empyema, or necrotising pneumonia is present. Individualise beyond 7 days based on imaging and drainage response.
Moderate Rec Moderate Evidence ATS/IDSA 2019Switch from IV to oral antibiotics once the patient is afebrile, hemodynamically stable, able to swallow, and has a functioning gastrointestinal tract — typically within 48–72 hours. Early switch shortens length of stay without increasing relapse.
Strong Rec High Evidence ATS/IDSA 2019Do not order routine follow-up chest imaging in patients whose community acquired pneumonia resolves clinically. Reserve repeat imaging for persistent symptoms, smokers over 50, or where occult malignancy is a concern.
Against Moderate Evidence ATS/IDSA 2019Clinical Decision Pathway
A question-based pathway for managing confirmed community acquired pneumonia from first contact to discharge. Work through the questions in order.
Monitoring and Follow-Up
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| Clinical review | Daily during admission; 48–72h post-discharge | Defervescence, oxygen weaning, return of appetite | Changing antibiotics at 24h because fever persists — give it 48–72h first |
| CRP / procalcitonin | Baseline and again at 48–72h | Trend, not absolute value; CRP should fall by ≥50% by day 3–4 | Checking daily — lags clinical improvement by 24–48h |
| Oxygen saturation | Continuous until weaned; at each clinical check | Ability to maintain SpO₂ ≥92% on room air before discharge | Discharging patients who desaturate on ambulation |
| Glucose (if on steroids) | Every 6h during steroid course | Hyperglycaemia needing insulin | Stopping monitoring when steroids taper |
| Pneumococcal vaccination | Before discharge | Update PCV20 or PPSV23 per age/risk schedule | Missing the teachable moment of an admission |
| Follow-up chest X-ray | Only if persistent symptoms or high-risk (smoker >50) | Resolution or occult malignancy | Ordering on every patient — not needed for routine recovery |
Evidence in Context
Where the major guidelines agree, where they differ, and what the landmark trials tell us.
Where ATS/IDSA and BTS/NICE Agree
Both frameworks converge on the central role of severity stratification, the primacy of beta-lactam antibiotics as first-line for most patients, and the safety of 5-day therapy in uncomplicated CAP. Both recommend against routine procalcitonin-guided initiation and emphasise early mobilisation, oxygen titration, and oral switch once clinically stable.
Where They Differ
Outpatient regimens: ATS/IDSA endorses amoxicillin, doxycycline, or a macrolide for healthy outpatients, and dual therapy for those with comorbidities. BTS/NICE recommends amoxicillin alone for low-severity CAP with macrolide reserved for atypical concerns.
Severity framework: ATS/IDSA uses the major/minor criteria system for ICU disposition; BTS/NICE relies primarily on CRB-65/CURB-65 with clinical judgement.
HCAP: ATS/IDSA has explicitly abandoned the category. BTS/NICE had not formalised the term to the same degree.
Short-Course Antibiotics: What the Trials Show
El Moussaoui and several subsequent trials randomised hospitalised CAP patients to 3 or 5 days of antibiotics after clinical stability versus longer courses. Cure rates were equivalent, relapse rates were equivalent, and shorter courses meant less C. difficile and resistance. Meta-analyses confirm non-inferiority of 5-day regimens in uncomplicated CAP.
CAPE COD and the Steroid Question
CAPE COD randomised 800 ICU patients with severe CAP to hydrocortisone (200 mg/day for 4–7 days, then taper) versus placebo. The trial was stopped early for efficacy: 28-day mortality fell from 11.9% to 6.2%, with lower rates of mechanical ventilation and vasopressor use. Hyperglycaemia was more common in the steroid arm but did not lead to clinically important harm. The earlier ESCAPe trial, which used methylprednisolone, did not show a mortality benefit — the difference is likely the steroid dose, duration, timing, and population.
The HCAP Story
From 2005 to 2019, patients with any healthcare contact were labelled HCAP and empirically given vancomycin plus piperacillin-tazobactam. Subsequent cohorts showed this dramatically increased antibiotic exposure without improving survival — and in some analyses, increased mortality. ATS/IDSA 2019 replaced the category with individualised MRSA and Pseudomonas risk assessment, one of the biggest shifts in antimicrobial stewardship of the decade.
What We Still Don’t Know
Several important questions remain unresolved. The optimal biomarker for duration decisions is still debated. The role of steroids in influenza pneumonia or COVID-19 CAP is distinct and evolving. Whether rapid syndromic molecular panels can safely narrow therapy faster than conventional cultures is being actively studied, as is the place of newer beta-lactam/beta-lactamase inhibitor combinations in severe CAP with resistance concerns.
References
- 1.Metlay JP, Waterer GW, Long AC, et al. Diagnosis and Treatment of Adults with Community-Acquired Pneumonia. An Official Clinical Practice Guideline of the ATS and IDSA. Am J Respir Crit Care Med. 2019;200(7):e45–e67. doi:10.1164/rccm.201908-1581ST
- 2.NICE Guideline [NG138]. Pneumonia (community-acquired): antimicrobial prescribing. 2019. nice.org.uk/guidance/ng138
- 3.Dequin PF, Meziani F, Quenot JP, et al. Hydrocortisone in Severe Community-Acquired Pneumonia (CAPE COD). N Engl J Med. 2023;388(21):1931–1941. doi:10.1056/NEJMoa2215145
- 4.Meduri GU, Shih MC, Bridges L, et al. Low-Dose Methylprednisolone Treatment in Critically Ill Patients With Severe Community-Acquired Pneumonia (ESCAPe). JAMA Intern Med. 2022;182(6):624–633. doi:10.1001/jamainternmed.2022.1148
- 5.el Moussaoui R, de Borgie CAJM, van den Broek P, et al. Effectiveness of discontinuing antibiotic treatment after three days versus eight days in mild to moderate-severe community acquired pneumonia. BMJ. 2006;332(7554):1355. doi:10.1136/bmj.332.7554.1355
- 6.Lim WS, Baudouin SV, George RC, et al. BTS guidelines for the management of community acquired pneumonia in adults: update 2009. Thorax. 2009;64(Suppl 3):iii1–iii55. doi:10.1136/thx.2009.121434
How to Read the Evidence Tags
Every recommendation carries two tags for strength and evidence quality, plus a source tag — Medaptly’s own simplified interpretations.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |