
Acute Limb Ischemia: 7 Critical Revascularization Rules
Clinical Practice Update — Diagnosis, Rutherford Staging, and Time-Critical Revascularization
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based recognition, staging, and revascularization of acute limb ischemia in adults
- Target Audience
- Emergency physicians, vascular surgeons, interventional radiologists, hospitalists, intensivists
- Setting
- Emergency department, interventional suite, vascular operating theatre, post-op ICU
- Source Evidence
- •ESVS Clinical Practice Guidelines on Acute Limb Ischaemia (2020)
- •ACC/AHA Guideline on Peripheral Artery Disease (2016)
- •TASC II — Inter-Society Consensus on Management of Peripheral Arterial Disease
- •STILE Trial — Surgery vs Thrombolysis for Lower Extremity Ischemia
- •TOPAS Trial — Thrombolysis or Peripheral Arterial Surgery
Key Clinical Takeaways
Effective acute limb ischemia care depends on three decisions made fast: recognising the limb is ischemic, staging it using the Rutherford system, and matching the revascularization strategy to the category. The rules below summarise the evidence at the bedside.
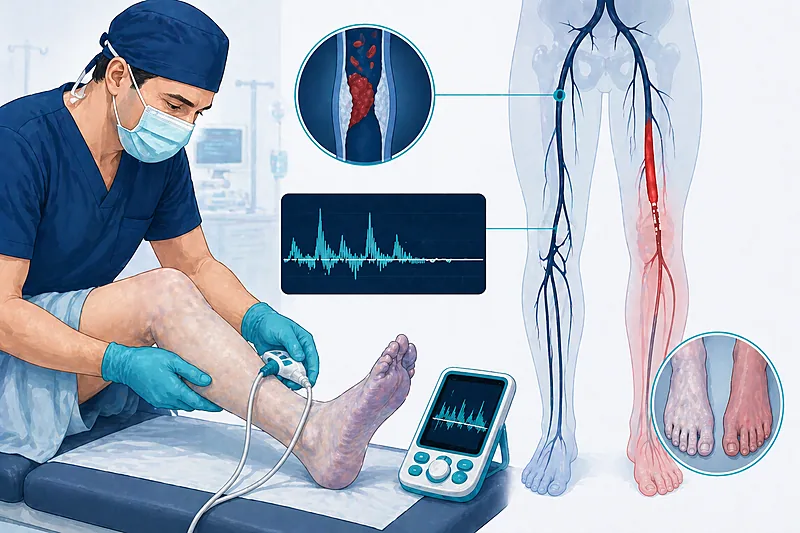
- 1Examine for the six P’s and palpate peripheral pulses on both limbs — compare side to side → Recognition
- 2Classify with Rutherford within 30 minutes — Category IIb loses muscle every hour without flow → Rutherford Staging
- 3Start IV unfractionated heparin the moment acute limb ischemia is suspected → Initial Management
- 4Category IIb limbs go straight to open thrombectomy or hybrid revascularization — no time for thrombolysis → Strategy
- 5Category I and IIa limbs are candidates for catheter-directed thrombolysis in a centre with interventional coverage → CDT
- 6Perform prophylactic four-compartment fasciotomy after ischemia ≥6 hours, especially in Rutherford IIb → Fasciotomy
- 7Anticipate reperfusion syndrome — check potassium, creatine kinase, lactate, and ECG immediately after flow is restored → Reperfusion Care
- 8Investigate the underlying cause — atrial fibrillation, thrombophilia, or graft occlusion — before discharge → Aetiology
Recognising Acute Limb Ischemia at the Bedside
The diagnosis of acute limb ischemia is clinical. The classic six P’s — pain, pallor, pulselessness, paresthesia, paralysis, and poikilothermia — appear in different combinations; waiting for all six means waiting too long. Rapid recognition is the single biggest determinant of limb salvage.
Examine both limbs in parallel when acute limb ischemia is suspected — compare temperature, colour, pulses, and neurological signs side to side.
Strong Rec Moderate Evidence ESVS 2020Ask directly about atrial fibrillation, recent myocardial infarction, known aneurysm, prior bypass or stent, and underlying peripheral artery disease — the aetiology guides the operation.
Strong Rec Moderate Evidence ESVS 2020 TASC IIPerform bedside hand-held Doppler at the ankle and over the femoral and popliteal arteries — audible monophasic or absent signals prompt urgent referral.
Strong Rec Moderate Evidence ESVS 2020Do not delay vascular surgical consultation to wait for CT angiography in a limb with sensory or motor deficit — imaging should not come before referral.
Against Low Evidence ESVS 2020Classifying Acute Limb Ischemia: The Rutherford System
The Rutherford classification is the common language for acute limb ischemia. It uses three bedside elements — sensory loss, motor weakness, and Doppler signals — to stratify limbs into four categories that dictate management tempo and technique.
Assign a Rutherford category to every patient with suspected acute limb ischemia within 30 minutes of presentation — record it explicitly in the notes.
Strong Rec Moderate Evidence ESVS 2020 ACC/AHA 2016Reassess the Rutherford category every 1–2 hours while awaiting definitive intervention — a IIa limb can drift into IIb within an hour.
Moderate Rec Low Evidence ESVS 2020Rutherford Categories at the Bedside
| Category | Sensory / Motor Findings | Doppler Signals | What It Means Practically |
|---|---|---|---|
| I — Viable | None; full movement | Audible arterial & venous | Not immediately threatened — time for imaging and planned CDT |
| IIa — Marginally threatened | Minimal (toes) or none; full movement | Often inaudible arterial; audible venous | Salvageable with prompt revascularization; CDT still possible |
| IIb — Immediately threatened | Beyond toes; mild to moderate weakness | Inaudible arterial; audible venous | Emergency open or hybrid revascularization — no time for CDT |
| III — Irreversible | Profound anaesthesia; paralysis / rigor | Inaudible arterial and venous | Primary amputation — revascularization causes harm |
Initial Management Before Revascularization
Systemic anticoagulation, basic resuscitation, pain control, and a focused workup run in parallel with the call to vascular surgery. These steps buy time without delaying the decision.
Initiate intravenous unfractionated heparin as soon as acute limb ischemia is suspected, typically an 80 units/kg bolus followed by an 18 units/kg/hour infusion, targeting an aPTT of 60–80 seconds.
Strong Rec Moderate Evidence ESVS 2020 ACC/AHA 2016Perform CT angiography in Rutherford I and IIa limbs to map the occlusion and plan revascularization — but only if it does not delay definitive care.
Strong Rec Moderate Evidence ESVS 2020Optimise perfusion pressure with gentle IV fluids, avoid vasoconstrictors when possible, and keep the limb dependent and warm to maximise collateral flow.
Moderate Rec Low Evidence ESVS 2020Send baseline full blood count, renal panel, creatine kinase, lactate, coagulation, and group & save before revascularization.
Strong Rec Low Evidence ESVS 2020Revascularization Strategy in Acute Limb Ischemia
The revascularization decision in acute limb ischemia pivots on Rutherford category, the time since onset, and the underlying anatomy. Open surgery, catheter-directed thrombolysis, percutaneous thrombectomy, and hybrid approaches each have a place — the error is picking the slow option for a fast-dying limb.
Transfer Rutherford IIb limbs directly to the operating theatre or hybrid suite — open thrombo-embolectomy or endovascular aspiration thrombectomy are the standard options; reserve CT angiography for on-table runs.
Strong Rec High Evidence ESVS 2020 STILEConsider catheter-directed thrombolysis in Rutherford I and selected IIa limbs with ischemia duration under 14 days — STILE and TOPAS showed equivalent limb salvage with fewer open procedures.
Moderate Rec High Evidence STILE TOPASDo not offer catheter-directed thrombolysis in Rutherford IIb or III limbs — thrombolysis takes hours that a motor-deficit limb does not have.
Against Moderate Evidence ESVS 2020Evaluate for primary amputation in Rutherford III limbs (fixed skin mottling, muscle rigor, profound anaesthesia) — attempts at revascularization will precipitate life-threatening reperfusion syndrome.
Strong Rec Moderate Evidence ESVS 2020 TASC IIMatching Strategy to Rutherford Category
| Rutherford Category | Preferred Strategy | Alternatives | Practical Tips |
|---|---|---|---|
| I — Viable | Catheter-directed thrombolysis | Percutaneous thrombectomy | Admit to monitored bed; check fibrinogen q6h |
| IIa — Marginally threatened | CDT or aspiration thrombectomy | Open thrombectomy if CDT unavailable | Reassess neurology every hour on CDT |
| IIb — Immediately threatened | Open or hybrid thrombectomy | Mechanical thrombectomy as bridge | Expect fasciotomy; have a vascular anaesthetist |
| III — Irreversible | Primary amputation | Palliation if operatively unfit | Treat hyperkalaemia and AKI aggressively |
Catheter-Directed Thrombolysis
Catheter-directed thrombolysis (CDT) delivers a local fibrinolytic infusion through a multi-side-hole catheter placed across the thrombus. It avoids an open operation and frequently unmasks the underlying lesion for targeted angioplasty, but takes hours to work and carries a meaningful bleeding risk.
Prescribe alteplase (tPA) at 0.5–1.0 mg/hour as the most commonly used CDT agent, with concurrent subtherapeutic heparin to prevent pericatheter thrombosis.
Moderate Rec Moderate Evidence ESVS 2020Monitor fibrinogen every 6 hours during CDT and stop the infusion if the level falls below 1.0 g/L or the patient develops bleeding.
Strong Rec Moderate Evidence ESVS 2020Do not offer thrombolysis to patients with active internal bleeding, recent major surgery or stroke within 3 months, or intracranial pathology — the risk of catastrophic haemorrhage outweighs limb benefit.
Against High Evidence ESVS 2020 TASC IIReassess the limb and underlying lesion with on-table angiography after clot lysis — an unmasked stenosis or graft anastomosis usually needs angioplasty or stenting to prevent re-occlusion.
Strong Rec Moderate Evidence ESVS 2020Compartment Syndrome and Fasciotomy
Compartment syndrome can follow any successful revascularization but is particularly common after Rutherford IIb reperfusion. Pain out of proportion to the examination, tense compartments, and rising creatine kinase should trigger immediate fasciotomy decision-making.
Perform prophylactic four-compartment lower leg fasciotomy at the time of revascularization in Rutherford IIb limbs and in any limb with ischemia lasting more than 6 hours.
Strong Rec Moderate Evidence ESVS 2020Measure compartment pressures only when the clinical picture is uncertain — a delta pressure (diastolic BP minus compartment pressure) below 30 mmHg confirms the diagnosis.
Moderate Rec Moderate Evidence ESVS 2020Do not close fasciotomy wounds primarily at the index operation — use delayed primary closure, split-thickness grafts, or dermal traction systems after muscle oedema resolves.
Against Low Evidence ESVS 2020When to Reach for Fasciotomy
| Clinical Scenario | Approach | Timing | Common Pitfall |
|---|---|---|---|
| Rutherford IIb limb post-revascularization | Prophylactic 4-compartment fasciotomy | At index operation | Waiting for pressures to confirm — too late |
| Ischemia ≥6 hours, any category | Prophylactic fasciotomy | Immediately post-reperfusion | Doing only anterior compartment |
| Rising CK, tense limb post-op | Therapeutic fasciotomy | Immediate return to theatre | Attributing pain to surgical site |
| Short ischemia (<4 h), Rutherford I/IIa | Close monitoring; fasciotomy if signs develop | At any sign of compartment tension | Discharging to ward without pressure checks |
Reperfusion Care and Post-Op Management
Restoring flow is not the end of the story. Reperfusion syndrome — hyperkalaemia, metabolic acidosis, rhabdomyolysis, and acute kidney injury — can kill the patient after the limb is saved.
Obtain an ECG, potassium, lactate, creatinine, and creatine kinase immediately after unclamping or clot extraction — and every 4–6 hours for the first 24 hours.
Strong Rec Moderate Evidence ESVS 2020Start aggressive intravenous crystalloid resuscitation aimed at a urine output of 1–2 mL/kg/hour to flush myoglobin in suspected rhabdomyolysis.
Strong Rec Moderate Evidence ESVS 2020Investigate the aetiology before discharge — 12-lead ECG, transthoracic echocardiography, and consideration of thrombophilia screen or graft surveillance duplex depending on context.
Strong Rec Moderate Evidence ESVS 2020 ACC/AHA 2016Prescribe lifelong anticoagulation in embolic acute limb ischemia from atrial fibrillation, with a DOAC or warfarin guided by standard stroke-risk scoring.
Strong Rec High Evidence ACC/AHA 2016Clinical Decision Pathway
A practical, question-based approach to managing the patient in front of you with a cold, painful limb. Work through the questions in order.
Monitoring and Follow-Up
| Parameter | When to Check | Action Threshold | Common Pitfalls |
|---|---|---|---|
| Limb examination | Hourly for first 24 h, then as per ward | Any loss of Doppler, rising pain, tense calf → theatre | Attributing pain to the wound rather than to ischaemia |
| Potassium & ECG | At unclamping then q4–6 h for 24 h | K >6.0 mmol/L or peaked T waves → treat | Waiting to repeat a haemolysed sample |
| Creatine kinase | At admission and q12 h for 48 h | Rising trend or >5000 U/L → aggressive hydration | Stopping fluids once urine output normalises |
| Creatinine & urine output | Daily for 5 days | Rising creatinine → nephrology involvement | Missing early AKI in a polyuric phase |
| Graft / stent patency | Duplex at 6 weeks, 6 months, then annually | Flow velocity >300 cm/s or new stenosis → re-intervene | Dropping surveillance once asymptomatic |
Evidence in Context
What the landmark trials show, where the major guidelines agree, and where honest evidence gaps remain.
Where ESVS and ACC/AHA Agree
Both frameworks agree on the Rutherford classification, immediate systemic heparinisation, the need for emergency open or hybrid revascularization in IIb limbs, prophylactic fasciotomy after prolonged ischaemia, and identification and treatment of the underlying cause.
Where ESVS and ACC/AHA Differ
Mechanical thrombectomy: ESVS gives more weight to percutaneous aspiration and mechanical thrombectomy devices, reflecting broader availability in European centres. ACC/AHA emphasises the traditional balance between CDT and open surgery.
Both acknowledge that local expertise and resource availability drive real-world choice.
What STILE and TOPAS Showed
STILE and TOPAS were the defining trials comparing CDT with open surgery for acute and subacute limb ischaemia. They showed no overall survival or amputation advantage for either arm but suggested CDT reduced the need for open surgery in patients with ischaemia of less than 14 days.
The bleeding rate with lytic therapy was not trivial, particularly in patients over 80, and this shaped the modern restricted indications for CDT.
Evidence Gaps We Still Face
Direct comparisons between modern percutaneous mechanical thrombectomy devices and open surgery are still limited. There is no robust randomised evidence to guide management of acute limb ischaemia in patients on DOACs, and the optimal antithrombotic regimen after revascularization remains an area of active debate.
References
- 1. Björck M, Earnshaw JJ, Acosta S, et al. Editor’s Choice — European Society for Vascular Surgery (ESVS) 2020 Clinical Practice Guidelines on the Management of Acute Limb Ischaemia. Eur J Vasc Endovasc Surg. 2020;59(2):173–218. doi:10.1016/j.ejvs.2019.09.006
- 2. Gerhard-Herman MD, Gornik HL, Barrett C, et al. 2016 AHA/ACC Guideline on the Management of Patients With Lower Extremity Peripheral Artery Disease. Circulation. 2017;135(12):e726–e779. doi:10.1161/CIR.0000000000000471
- 3. Norgren L, Hiatt WR, Dormandy JA, et al. Inter-Society Consensus for the Management of Peripheral Arterial Disease (TASC II). J Vasc Surg. 2007;45(1 Suppl):S5–S67. doi:10.1016/j.jvs.2006.12.037
- 4. The STILE Investigators. Results of a prospective randomized trial evaluating surgery versus thrombolysis for ischemia of the lower extremity. Ann Surg. 1994;220(3):251–266. doi:10.1097/00000658-199409000-00003
- 5. Ouriel K, Veith FJ, Sasahara AA. A comparison of recombinant urokinase with vascular surgery as initial treatment for acute arterial occlusion of the legs (TOPAS). N Engl J Med. 1998;338(16):1105–1111. doi:10.1056/NEJM199804163381603
How to Read the Evidence Tags
Every recommendation in this article carries two tags — recommendation strength and evidence quality. These are Medaptly’s simplified interpretations, designed for bedside use.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | Evidence favours this action for most patients. |
| Conditional Rec | Benefit is less certain — individualise based on patient factors. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |