
Diverticulitis Management: Essential 2026 Surgical Guide
Clinical Practice Update — Hinchey Classification, Selective Antibiotic Use, Percutaneous Drainage, and Colectomy Decisions
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based diverticulitis management in immunocompetent adults across outpatient, inpatient, and surgical settings
- Target Audience
- General surgeons, colorectal surgeons, emergency physicians, hospitalists, primary care physicians, surgical residents
- Setting
- Primary care, emergency department, surgical ward, operating room
- Source Evidence
- •ASCRS Clinical Practice Guidelines for Left-Sided Colonic Diverticulitis (2020)
- •WSES Guidelines on Acute Colonic Diverticulitis (2020 update)
- •DIABOLO Trial — Observation vs Antibiotics in Uncomplicated Diverticulitis (BJS, 2017)
- •LADIES Trial — Laparoscopic Lavage vs Sigmoidectomy (Lancet, 2015)
Key Clinical Takeaways
Effective diverticulitis management in 2026 depends on three decisions made in rapid sequence: confirm the diagnosis with CT, stratify severity using the Hinchey classification, and choose between observation, selective antibiotics, drainage, or surgery. The evidence landscape has shifted — antibiotics are no longer automatic for uncomplicated disease, drainage has displaced early surgery for most abscesses, and elective resection is now a shared decision rather than a rule-based reflex.
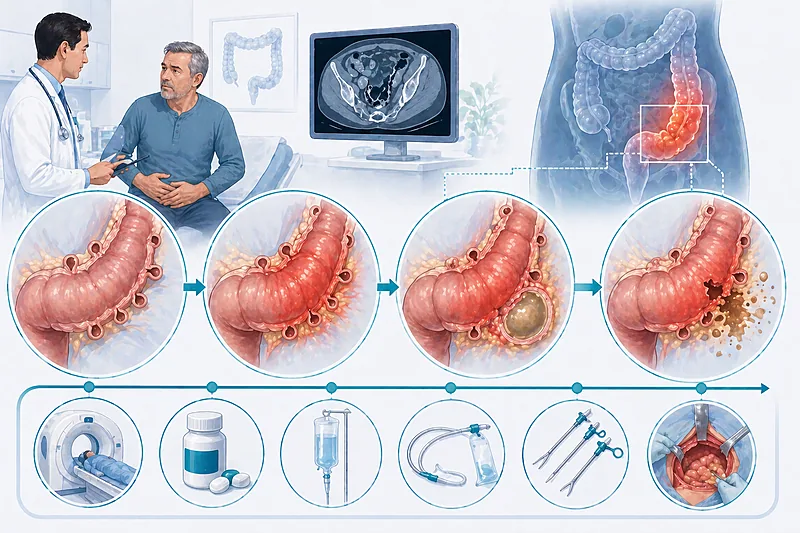
- 1Confirm acute diverticulitis with contrast-enhanced CT of the abdomen and pelvis — clinical suspicion alone overestimates the diagnosis → Initial Assessment
- 2Apply the Hinchey classification to every CT-confirmed case — it anchors every subsequent management decision → Initial Assessment
- 3Withhold antibiotics in selected immunocompetent adults with uncomplicated disease — observational trials show non-inferior outcomes → Antibiotic Use
- 4Offer outpatient care to most patients with uncomplicated disease who can tolerate oral intake → Antibiotic Use
- 5Treat abscesses larger than 3–4 cm (Hinchey Ib–II) with image-guided percutaneous drainage before considering surgery → Percutaneous Drainage
- 6Reserve emergency colectomy for purulent (Hinchey III) or faecal (Hinchey IV) peritonitis and for patients who fail drainage → Surgical Decisions
- 7Prefer primary anastomosis with or without diverting ileostomy over Hartmann procedure in selected stable patients → Surgical Decisions
- 8Do not recommend elective sigmoid resection based on episode count alone — individualise on symptom burden, complications, and patient values → Surgical Decisions
- 9Perform interval colonoscopy 6–8 weeks after a complicated episode to exclude malignancy → Monitoring
- 10Counsel patients on lifestyle measures: dietary fibre, smoking cessation, weight optimisation, and selective NSAID use → Monitoring
Initial Assessment in Diverticulitis Management
Accurate diagnosis and severity stratification are the two anchors of diverticulitis management. Clinical diagnosis alone — left-lower-quadrant pain, fever, and leukocytosis — misclassifies a meaningful proportion of patients, so modern practice routes all suspected cases through cross-sectional imaging before committing to a treatment pathway.
Perform contrast-enhanced CT of the abdomen and pelvis as first-line imaging in every adult with suspected acute diverticulitis. It confirms the diagnosis, identifies abscesses, free air, and extra-luminal contrast, and anchors the Hinchey classification.
Strong Rec High Evidence ASCRS 2020 WSES 2020Apply the Hinchey classification to every CT-confirmed case. It is the common language that distinguishes uncomplicated disease from micro-perforation, pericolic abscess, pelvic abscess, and frank peritonitis — each with a different treatment pathway.
Strong Rec Moderate Evidence ASCRS 2020 WSES 2020Check CRP and white cell count at presentation. A CRP above 150 mg/L correlates with complicated disease and should prompt closer observation even when initial CT appears uncomplicated.
Moderate Rec Moderate Evidence WSES 2020Do not perform colonoscopy during an acute episode. The risk of perforation outweighs any diagnostic gain when CT has already confirmed the diagnosis.
Against Moderate Evidence ASCRS 2020Consider ultrasound as a first-line alternative in young, thin patients or when CT is contraindicated — a stepwise ultrasound-first, CT-if-uncertain strategy reduces radiation exposure without missing complicated disease.
Conditional Rec Moderate Evidence WSES 2020Admit patients with any of the following: Hinchey Ib or higher, inability to tolerate oral intake, immunosuppression, uncontrolled comorbidity, poor social support, or clinical deterioration despite initial outpatient care.
Strong Rec Moderate Evidence ASCRS 2020Hinchey Classification Applied to Clinical Decisions
| Hinchey Stage | CT Picture | First-Line Pathway | Role of Surgery | Practical Pitfalls |
|---|---|---|---|---|
| 0 / Ia | Pericolic inflammation; no abscess | Outpatient; consider observation without antibiotics in immunocompetent adults | None acutely | Do not prescribe reflexively; reassess at 72 h if not improving |
| Ib | Pericolic abscess | Admission, IV antibiotics, drain if >3–4 cm | Rescue only if drainage fails | Small abscesses (<3 cm) often resolve with antibiotics alone |
| II | Distant/pelvic abscess | Percutaneous drainage + IV antibiotics | Elective sigmoidectomy only if recurrence or fistula | Multiloculated collections may need catheter repositioning |
| III | Purulent peritonitis | Emergency surgery (resection preferred over lavage) | Primary role; primary anastomosis preferred when stable | LADIES trial showed higher reintervention with lavage |
| IV | Faecal peritonitis | Emergency resection (Hartmann or resection with anastomosis + loop ileostomy) | Primary role; damage-control approach in unstable patients | Hartmann reversal rate is only ~50% — counsel in advance |
Antibiotic Use in Diverticulitis Management
Routine antibiotic therapy for every episode of uncomplicated disease has been one of the biggest shifts in modern diverticulitis management. Two large randomised trials — AVOD in Sweden and DIABOLO in the Netherlands — showed no significant difference in complications, recurrence, or recovery time between observation and antibiotic treatment in selected immunocompetent adults with CT-confirmed uncomplicated disease. Both ASCRS and WSES now endorse selective rather than universal antibiotic use.
Consider observation without antibiotics in immunocompetent adults with CT-confirmed uncomplicated diverticulitis (Hinchey 0/Ia), no significant comorbidities, and reliable follow-up.
Moderate Rec High Evidence ASCRS 2020 DIABOLO 2017Prescribe antibiotics for patients who are immunosuppressed, pregnant, frail, have significant comorbidities, or present with Hinchey Ib or higher — these groups were excluded from observational trials and the evidence for antibiotic omission does not apply to them.
Strong Rec Moderate Evidence ASCRS 2020 WSES 2020Start oral amoxicillin-clavulanate 875/125 mg twice daily for 4–7 days as the preferred outpatient antibiotic regimen, covering Gram-negative and anaerobic coliforms implicated in diverticulitis.
Strong Rec Moderate Evidence ASCRS 2020Use ciprofloxacin plus metronidazole only in patients with documented beta-lactam allergy — not as a routine first-line option, given the FDA black-box warnings attached to fluoroquinolones.
Conditional Rec Moderate Evidence ASCRS 2020 FDA Safety CommunicationStart IV piperacillin-tazobactam 4.5 g every 8 hours for inpatients with complicated disease, and step down to oral amoxicillin-clavulanate as soon as clinical improvement allows — typically within 48–72 hours.
Strong Rec Moderate Evidence WSES 2020Limit total antibiotic course to 4–7 days in uncomplicated disease and 7–10 days in complicated disease responding to source control — longer courses do not improve outcomes and increase adverse effects.
Moderate Rec Moderate Evidence WSES 2020Antibiotic Options: A Practical Regimen Guide
| Regimen | Route & Dose | Best Clinical Fit | Practical Tips |
|---|---|---|---|
| Amoxicillin-clavulanate | PO 875/125 mg BID × 4–7 d | Outpatient, uncomplicated — first-line | Dose-adjust in renal impairment; take with food to reduce GI upset |
| Piperacillin-tazobactam | IV 4.5 g every 8 h | Inpatient, complicated — first-line | Step down to oral at 48–72 h when afebrile and tolerating diet |
| Ceftriaxone + metronidazole | IV 2 g daily + 500 mg TID | Inpatient alternative when piperacillin unavailable | Avoid in neonates; monitor for C. difficile on prolonged courses |
| Ciprofloxacin + metronidazole | PO 500 mg BID + 400 mg TID | Beta-lactam allergy only — not first-line | FDA black-box warnings (tendinopathy, aortic dissection, neuropathy) |
| Meropenem | IV 1 g every 8 h | Severe sepsis, ESBL risk, or recent broad antibiotic exposure | Reserve to protect carbapenem stewardship; de-escalate with cultures |
Percutaneous Drainage of Diverticular Abscess
Image-guided drainage has largely replaced upfront surgery for Hinchey II disease. Drainage provides source control, allows inflammation to subside, and preserves the option of elective single-stage resection later — or, in many cases, avoids the need for resection altogether.
Refer for percutaneous drainage by interventional radiology when the abscess exceeds 3–4 cm and is anatomically accessible. A CT- or ultrasound-guided pigtail catheter provides source control with lower morbidity than emergency surgery.
Strong Rec Moderate Evidence ASCRS 2020 WSES 2020Treat abscesses smaller than 3 cm with antibiotics alone in the first instance, reserving drainage for those that fail to respond clinically within 48–72 hours.
Moderate Rec Low Evidence ASCRS 2020Reassess at 48–72 hours after drain insertion. Falling CRP, declining drain output, resolving fever, and return of appetite together indicate successful source control; persistent sepsis signals failure and warrants surgical review.
Strong Rec Moderate Evidence WSES 2020Remove the drain when output falls below roughly 20 mL per 24 hours, the tract has matured, and repeat imaging confirms resolution of the collection.
Moderate Rec Low Evidence ASCRS 2020Surgical Decisions in Diverticulitis Management
Surgery for diverticulitis now divides into two distinct conversations: emergency operations for peritonitis or drainage failure, and elective operations for recurrent or complicated disease. The shift in surgical decisions over the last decade has been toward resection over lavage in the emergency setting, and toward shared decision-making rather than rule-of-thumb resection in the elective setting.
Emergency Surgery
Perform emergency colectomy for Hinchey III (purulent peritonitis) or Hinchey IV (faecal peritonitis), and for patients with complicated disease who fail medical therapy or drainage.
Strong Rec High Evidence ASCRS 2020 WSES 2020Prefer primary anastomosis with or without diverting loop ileostomy over Hartmann procedure in haemodynamically stable patients with Hinchey III disease. Stoma-reversal rates favour primary anastomosis, and overall morbidity is comparable.
Moderate Rec Moderate Evidence ASCRS 2020 LADIES/DIVA 2019Reserve Hartmann procedure for unstable patients, those with severe contamination, significant comorbidity, or when operative conditions preclude safe anastomosis.
Moderate Rec Moderate Evidence ASCRS 2020Do not use laparoscopic lavage as a routine alternative to resection in Hinchey III disease — the LADIES and DILALA trials showed higher rates of reoperation and persistent abscess with lavage alone.
Against High Evidence LADIES 2015 DILALA 2016Elective Surgery
Do not recommend elective sigmoid resection based purely on the number of prior episodes. Individualise the decision around symptom burden, quality-of-life impact, complications, fitness for surgery, and the patient’s own values.
Strong Rec Moderate Evidence ASCRS 2020Consider elective laparoscopic sigmoid resection in patients with recurrent diverticulitis that causes persistent symptoms, chronic smouldering inflammation, fistulising disease (colovesical, colovaginal, coloenteric), or stricture producing obstructive symptoms.
Moderate Rec Moderate Evidence ASCRS 2020Discuss elective resection earlier in immunosuppressed patients and transplant recipients — recurrence in this population carries substantially higher perforation and mortality risk.
Moderate Rec Low Evidence ASCRS 2020Plan elective surgery at least 6–8 weeks after the most recent acute episode to allow inflammation to settle and reduce operative morbidity.
Moderate Rec Low Evidence ASCRS 2020Ensure the distal resection margin reaches the proximal rectum at the level of the sacral promontory — leaving diseased sigmoid behind predicts recurrence regardless of how extensive the proximal resection was.
Strong Rec Moderate Evidence ASCRS 2020Clinical Decision Pathway
A question-based walk-through of diverticulitis management from presentation to disposition. Follow the questions in order.
Monitoring and Follow-Up
Follow-up closes the loop in diverticulitis management: it excludes occult malignancy, catches recurrence early, and addresses modifiable lifestyle risk factors.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| CRP and WBC | 48–72 h after admission or drain placement | At least 50% reduction in CRP from peak | Do not recheck daily — lags clinical picture; trend matters more than single values |
| Clinical review | 48–72 h post-treatment | Temperature, appetite, pain, tolerance of diet | Do not switch antibiotics at 24 h for persistent fever alone |
| Follow-up CT | Only for clinical deterioration or failure to improve | New or expanding collection, free air, missed pathology | Routine repeat CT is unnecessary if the patient is recovering |
| Interval colonoscopy | 6–8 weeks after a complicated episode | Occult colorectal malignancy mimicking diverticulitis | Not needed if recent high-quality screening colonoscopy and uncomplicated episode |
| Lifestyle review | At outpatient follow-up | Dietary fibre, smoking, weight, NSAID use | Avoid blanket “no nuts or seeds” advice — not supported by evidence |
Evidence in Context
Where ASCRS and WSES agree, where they differ, and the trials that have shaped modern diverticulitis management.
Where ASCRS and WSES Agree
Both societies agree on the central role of contrast CT for diagnosis, the Hinchey classification as the shared language of severity, percutaneous drainage as the first-line intervention for Hinchey II disease, and resection (rather than laparoscopic lavage) as the preferred approach for peritonitis. They also agree that observation without antibiotics is acceptable for selected immunocompetent patients with uncomplicated disease, and that elective resection should be individualised rather than triggered by episode count.
Where the Guidelines Differ
WSES is generally more permissive about antibiotic omission in uncomplicated disease, citing a broader reading of the DIABOLO and AVOD trials. ASCRS retains slightly more caution, particularly in North American settings where outpatient follow-up infrastructure varies. On the surgical side, ASCRS leans more strongly toward primary anastomosis with diverting ileostomy in Hinchey III, while WSES acknowledges Hartmann procedure as acceptable in a wider range of scenarios including surgeon experience and anatomic factors.
Antibiotics vs Observation: AVOD and DIABOLO
The Swedish AVOD trial (2012) and the Dutch DIABOLO trial (2017) together randomised more than 1,200 patients with CT-confirmed uncomplicated disease to antibiotics or observation. Neither trial found a significant difference in complications, recurrence, or recovery time. Long-term follow-up of DIABOLO has shown that these findings persist out to 24 months. This evidence underpins the modern selective-antibiotic paradigm in diverticulitis management.
Laparoscopic Lavage: LADIES and DILALA
The LADIES (Lancet, 2015) and DILALA trials tested laparoscopic peritoneal lavage against resection in Hinchey III disease. Lavage offered a tempting alternative — no stoma, shorter operation — but both trials showed higher rates of reoperation, persistent abscess, and failure to control sepsis. The result is that lavage is no longer considered a first-line alternative to resection for purulent peritonitis.
Primary Anastomosis vs Hartmann: The DIVA Analysis
The Ladies-DIVA arm and subsequent meta-analyses showed that primary anastomosis with diverting loop ileostomy produces similar short-term morbidity to Hartmann procedure but higher rates of eventual stoma reversal and better quality of life. This is the main reason primary anastomosis is now preferred in stable patients with adequate tissue conditions, while Hartmann remains the fallback when conditions are unfavourable.
What We Still Don’t Know
Important evidence gaps remain. The optimal antibiotic duration in complicated disease responding to drainage has not been established by randomised data. Long-term outcomes of observation-only strategies in older, multi-morbid patients are under-studied. The role of mesalazine, probiotics, and rifaximin in preventing recurrence remains uncertain despite repeated enthusiasm, and the ideal threshold for elective resection in the post-episode-count era is largely an exercise in clinical judgement.
References
- 1.Hall J, Hardiman K, Lee S, et al. The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Treatment of Left-Sided Colonic Diverticulitis. Dis Colon Rectum. 2020;63(6):728–747. doi:10.1097/DCR.0000000000001679
- 2.Sartelli M, Weber DG, Kluger Y, et al. 2020 update of the WSES guidelines for the management of acute colonic diverticulitis in the emergency setting. World J Emerg Surg. 2020;15(1):32. doi:10.1186/s13017-020-00313-4
- 3.Daniels L, Ünlü Ç, de Korte N, et al. Randomized clinical trial of observational versus antibiotic treatment for a first episode of CT-proven uncomplicated acute diverticulitis. Br J Surg. 2017;104(1):52–61. doi:10.1002/bjs.10309
- 4.Vennix S, Musters GD, Mulder IM, et al. Laparoscopic peritoneal lavage or sigmoidectomy for perforated diverticulitis with purulent peritonitis: a multicentre, parallel-group, randomised, open-label trial. Lancet. 2015;386(10000):1269–1277. doi:10.1016/S0140-6736(15)61168-0
- 5.Chabok A, Påhlman L, Hjern F, et al. Randomized clinical trial of antibiotics in acute uncomplicated diverticulitis (AVOD). Br J Surg. 2012;99(4):532–539. doi:10.1002/bjs.8688
- 6.Schultz JK, Yaqub S, Wallon C, et al. Laparoscopic Lavage vs Primary Resection for Acute Perforated Diverticulitis: The SCANDIV Randomized Clinical Trial. JAMA. 2015;314(13):1364–1375. doi:10.1001/jama.2015.12076
How to Read the Evidence Tags
Every recommendation in this Practice Update carries three inline tags: recommendation strength, evidence quality, and source. These are Medaptly’s own simplified interpretations — not reproductions of any single guideline body’s classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise to the patient. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |