
Endometrial Cancer Workup: 7 Essential Diagnostic Steps
Clinical Practice Update — Sampling Thresholds, Staging Imaging, and Molecular Classification
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based endometrial cancer workup covering sampling thresholds, staging imaging, and molecular classification
- Target Audience
- Gynecologists, gynecologic oncologists, family physicians, residents, and trainees
- Setting
- Outpatient gynecology, primary care, gynecologic oncology referral
- Source Evidence
- •ESGO/ESTRO/ESP Guidelines for Management of Endometrial Carcinoma (2021)
- •NCCN Clinical Practice Guidelines: Uterine Neoplasms (Version 2.2024)
- •ACOG Committee Opinion on Endometrial Hyperplasia and Carcinoma Evaluation
- •The Cancer Genome Atlas (TCGA) Integrated Genomic Characterization of Endometrial Carcinoma (Nature, 2013)
- •PORTEC-3 Molecular Substudy (Lancet Oncology, 2020)
Key Clinical Takeaways
A modern endometrial cancer workup rests on three pillars: prompt tissue sampling when bleeding patterns cross defined thresholds, focused staging imaging tailored to risk, and molecular classification that now guides both prognosis and treatment intensity. The points below distill current evidence into bedside-ready rules.
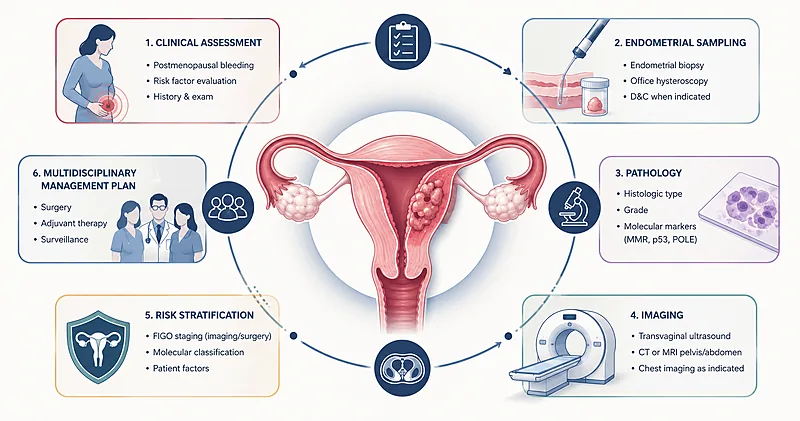
- 1Any postmenopausal bleeding warrants prompt evaluation — do not wait for a second episode. → Recognizing Presentation
- 2Endometrial thickness of 4 mm or more on transvaginal ultrasound is the standard sampling threshold in postmenopausal women. → Sampling Thresholds
- 3Pipelle office endometrial biopsy is first-line; hysteroscopy with directed biopsy follows when results are inadequate or bleeding persists. → Sampling Thresholds
- 4Pelvic MRI is the preferred local staging study because it best defines myometrial invasion and cervical stromal involvement. → Staging Imaging
- 5Reserve CT chest/abdomen/pelvis for high-grade or non-endometrioid histology and clinically suspected extrauterine disease. → Staging Imaging
- 6Perform molecular classification on every newly diagnosed endometrial carcinoma to assign one of four prognostic subgroups. → Molecular Classification
- 7Universal mismatch-repair (MMR) immunohistochemistry screens for Lynch syndrome and identifies candidates for immunotherapy. → Molecular Classification
- 8Total hysterectomy with bilateral salpingo-oophorectomy via minimally invasive surgery is the standard initial procedure for apparent uterine-confined disease. → Initial Surgery
- 9Sentinel lymph node mapping with indocyanine green has replaced routine pelvic lymphadenectomy for apparent early-stage disease. → Initial Surgery
- 10Refer all suspected or biopsy-confirmed cases to gynecologic oncology before definitive surgery. → Initial Surgery
Recognizing the Presentation: When to Suspect Endometrial Cancer
Roughly nine in ten women with endometrial cancer present with abnormal vaginal bleeding, which is also why the disease is often diagnosed at an early, curable stage. Any postmenopausal bleeding — including spotting — carries a baseline malignancy risk of about 9 to 10 percent and must be investigated rather than observed.
In premenopausal women, the workup is triggered by patterns rather than thresholds: prolonged anovulatory bleeding, intermenstrual bleeding in the presence of obesity, polycystic ovary syndrome, tamoxifen exposure, or a family history suggestive of Lynch syndrome.
Evaluate every episode of postmenopausal bleeding, including a single spotting event. Do not attribute bleeding to atrophy without first excluding malignancy.
Strong Rec High Evidence ACOG 2018 NCCN 2024Initiate an endometrial cancer workup in any woman aged 45 years or older who presents with abnormal uterine bleeding, regardless of menopausal status.
Strong Rec Moderate Evidence ACOG 2018Consider an endometrial cancer workup in women younger than 45 with persistent abnormal bleeding plus risk factors: obesity (BMI ≥30), unopposed estrogen exposure, anovulation, tamoxifen use, or Lynch syndrome.
Moderate Rec Moderate Evidence ACOG 2018 NCCN 2024Counsel patients with confirmed or suspected Lynch syndrome on annual endometrial sampling from age 30–35, and offer risk-reducing hysterectomy with bilateral salpingo-oophorectomy after childbearing is complete.
Strong Rec Moderate Evidence SGO 2014 NCCN 2024Sampling Thresholds: Initiating Endometrial Cancer Workup
The decision to sample the endometrium is the most consequential step of the endometrial cancer workup. Get the threshold wrong and either you miss a malignancy or you commit a woman to an unnecessary procedure. The current standard combines transvaginal ultrasound (TVUS) for triage in postmenopausal women with direct office sampling for premenopausal women whose risk profile justifies it.
Postmenopausal women: the 4 mm rule
An endometrial thickness below 4 mm on TVUS in postmenopausal women with bleeding has a negative predictive value above 99 percent for endometrial cancer. Above 4 mm, sampling is required. Below 4 mm, sampling can be safely deferred unless bleeding recurs.
Perform transvaginal ultrasound as the initial triage test in postmenopausal women with bleeding. Measure endometrial thickness in the sagittal plane on the thickest segment.
Strong Rec High Evidence ACOG 2018 NCCN 2024Proceed to endometrial sampling when the endometrial thickness is 4 mm or greater in a postmenopausal woman with bleeding.
Strong Rec High Evidence ACOG 2018Sample the endometrium regardless of thickness if bleeding is persistent, recurrent, or accompanied by hematometra, or if the endometrium cannot be adequately measured.
Strong Rec Moderate Evidence ACOG 2018 ESGO 2021Do not rely on endometrial thickness alone to exclude malignancy in premenopausal women with abnormal bleeding. The 4 mm threshold is validated only in the postmenopausal context.
Against Moderate Evidence ACOG 2018Choosing the sampling method
Office endometrial biopsy (typically with a Pipelle device) has roughly 90 percent sensitivity for endometrial cancer when adequate tissue is obtained, and it can be performed in a single outpatient visit. Hysteroscopy with directed biopsy is the fallback when the office biopsy is inconclusive, when bleeding persists despite a negative biopsy, or when a focal lesion is seen on imaging.
Perform office endometrial biopsy (Pipelle or equivalent) as the first-line sampling method when the cervical canal is patent and the patient tolerates the procedure.
Strong Rec High Evidence ESGO 2021 NCCN 2024Refer for hysteroscopy with directed biopsy when the office biopsy is inadequate or non-diagnostic, when bleeding persists despite benign histology, or when a focal endometrial lesion is suspected.
Strong Rec Moderate Evidence ESGO 2021Avoid routine dilatation and curettage as the first sampling step. Reserve it for cases where hysteroscopy is unavailable or anesthesia is otherwise required.
Conditional Rec Moderate Evidence ESGO 2021Document tissue adequacy on every pathology report. A scant or non-diagnostic specimen in the setting of ongoing bleeding requires repeat sampling, not reassurance.
Strong Rec Moderate Evidence ACOG 2018Hysteroscopy with directed biopsy is indicated when any of the following are present: an inadequate or non-diagnostic Pipelle specimen, persistent bleeding despite a benign biopsy, a focal endometrial lesion on TVUS or saline-infusion sonography, or cervical stenosis preventing office sampling.
Staging Imaging in Endometrial Cancer Workup
Pre-operative imaging is not formal staging — endometrial cancer remains a surgically staged disease — but it informs the operative plan, identifies patients who need referral to a high-volume center, and detects extrauterine disease that would change the procedure entirely. Pelvic MRI is the workhorse; CT and PET-CT have narrower indications.
Local staging with pelvic MRI
Multiparametric pelvic MRI — T2-weighted, diffusion-weighted, and dynamic contrast-enhanced sequences — achieves about 85 percent accuracy for the depth of myometrial invasion and around 90 percent for cervical stromal involvement. Both are central to the endometrial cancer workup because they predict the need for lymph node assessment and adjuvant therapy.
Obtain multiparametric pelvic MRI before definitive surgery to assess myometrial invasion, cervical stromal involvement, and adnexal disease.
Strong Rec High Evidence ESGO 2021 ESUR 2018When MRI is contraindicated (pacemaker, severe claustrophobia, advanced renal failure precluding contrast), substitute expert transvaginal ultrasound performed by a gynecologic ultrasonographer.
Moderate Rec Moderate Evidence ESGO 2021Do not use pelvic ultrasound alone to assess depth of myometrial invasion outside of expert centers. Operator dependency and limited soft-tissue contrast reduce reliability.
Against Moderate Evidence ESUR 2018Distant staging: when to add CT or PET-CT
Obtain contrast-enhanced CT of the chest, abdomen, and pelvis in high-grade endometrioid (G3), serous, clear-cell, or carcinosarcoma histology, or whenever extrauterine disease is clinically suspected.
Strong Rec Moderate Evidence NCCN 2024 ESGO 2021Consider PET-CT for selected cases of suspected recurrent or metastatic disease and for surveillance imaging in advanced-stage tumors. Do not use it routinely for initial staging.
Conditional Rec Moderate Evidence NCCN 2024Check baseline CA-125 in serous, clear-cell, or carcinosarcoma histology. It may help monitor response and detect recurrence; it has limited value in low-grade endometrioid tumors.
Conditional Rec Low Evidence NCCN 2024Molecular Classification: The Modern Approach to Endometrial Cancer Workup
The Cancer Genome Atlas (TCGA) reorganized endometrial cancer into four molecular subgroups whose prognosis and treatment response differ more reliably than histologic grade. The ProMisE classifier — using POLE sequencing, MMR immunohistochemistry, and p53 staining — reproduces these subgroups in routine practice and is now embedded in the ESGO/ESTRO/ESP framework. Molecular classification is therefore part of the modern endometrial cancer workup, not an academic add-on.
The four molecular subgroups
| Subgroup | Defining Test | Approx. Frequency | Prognosis | Practical Implication |
|---|---|---|---|---|
| POLE-ultramutated | POLE exonuclease-domain sequencing | 7–10% | Excellent | De-escalation candidate; adjuvant therapy often omitted in Stage I–II |
| MMR-deficient / MSI-H | MMR IHC (MLH1, PMS2, MSH2, MSH6) | 25–30% | Intermediate | Trigger Lynch syndrome workup; immunotherapy responsive in advanced disease |
| p53-abnormal | p53 IHC (mutant pattern) | 10–15% | Poor | Escalate adjuvant therapy; chemotherapy plus radiotherapy commonly used |
| No specific molecular profile (NSMP) | Diagnosis of exclusion | ~50% | Intermediate | Treat per histopathologic risk; ER/PR status helps refine further |
Perform molecular classification on every newly diagnosed endometrial carcinoma, ideally on the diagnostic biopsy so the result is available before definitive surgery.
Strong Rec High Evidence ESGO 2021 NCCN 2024Perform universal MMR immunohistochemistry on every endometrial cancer specimen for Lynch syndrome screening, regardless of age or family history.
Strong Rec High Evidence SGO 2014 NCCN 2024Reflex to MLH1 promoter methylation testing when MLH1/PMS2 loss is detected on IHC. Refer to genetics if methylation is absent or if MSH2, MSH6, or PMS2 is lost in isolation.
Strong Rec High Evidence SGO 2014Test for POLE exonuclease-domain mutations in all high-grade endometrial cancers and in any case where the molecular result will change adjuvant therapy decisions.
Strong Rec High Evidence ESGO 2021Interpret p53 immunohistochemistry as “abnormal” (mutant pattern) when staining shows diffuse strong overexpression, complete absence, or unusual cytoplasmic staining. A wild-type pattern is not equivalent to a normal result if other markers conflict.
Moderate Rec Moderate Evidence ESGO 2021Initial Surgical Management Decisions
The endometrial cancer workup ends and treatment begins with definitive surgery. The standard operation is total hysterectomy with bilateral salpingo-oophorectomy and surgical staging, typically performed via a minimally invasive approach. Sentinel lymph node mapping has largely supplanted routine pelvic lymphadenectomy for apparent uterine-confined disease.
Refer every biopsy-confirmed or strongly suspected endometrial cancer to a gynecologic oncologist before definitive surgery. Outcomes are demonstrably better at high-volume centers.
Strong Rec High Evidence SGO 2014 NCCN 2024Perform total hysterectomy with bilateral salpingo-oophorectomy as the standard initial operation, with a minimally invasive route (laparoscopic or robotic) preferred over open surgery whenever feasible.
Strong Rec High Evidence LAP2 Trial NCCN 2024Perform sentinel lymph node mapping with indocyanine green and cervical injection in apparent Stage I–II disease. It detects nodal metastasis with sensitivity above 95 percent while sparing the morbidity of full lymphadenectomy.
Strong Rec High Evidence FIRES Trial NCCN 2024Add omental biopsy and peritoneal washings in serous, clear-cell, or carcinosarcoma histology, mirroring the staging principles used in ovarian cancer.
Moderate Rec Moderate Evidence NCCN 2024Discuss fertility-sparing treatment (continuous progestin therapy with close surveillance biopsy) only in carefully selected women with Stage IA, grade 1 endometrioid carcinoma who have completed an adequate endometrial cancer workup and accept the recurrence risk.
Conditional Rec Moderate Evidence ESGO 2021 NCCN 2024Clinical Decision Pathway
A practical, question-based approach to the endometrial cancer workup, from first presentation to operative planning.
Sampling and Imaging Reference
Sampling triggers by clinical scenario
A clinician-facing summary of when to sample, how to sample, and what to do with the result. Organised by clinical scenario rather than by guideline section.
| Clinical Scenario | Initial Test | Sample If | Practical Tip |
|---|---|---|---|
| Postmenopausal bleeding | TVUS | Endometrium ≥4 mm, focal lesion, or persistent bleeding | If bleeding recurs after benign biopsy, escalate to hysteroscopy |
| Abnormal bleeding, age ≥45 | Office endometrial biopsy | Always — do not rely on TVUS | TVUS still useful for structural lesions |
| Abnormal bleeding, age <45 + risk factors | Office endometrial biopsy | Persistent bleeding despite medical therapy | Counsel on Lynch syndrome screening if family history positive |
| Tamoxifen user with bleeding | Office endometrial biopsy | Always — TVUS is unreliable due to subepithelial cysts | Consider hysteroscopy first-line in this group |
| Asymptomatic Lynch syndrome carrier | Annual TVUS + endometrial biopsy | From age 30–35 onwards | Offer risk-reducing surgery after childbearing |
Imaging by histology and risk
| Histology / Risk | Pelvic MRI | CT C/A/P | PET-CT | CA-125 |
|---|---|---|---|---|
| Grade 1–2 endometrioid | Yes | Only if suspected extrauterine disease | No | No |
| Grade 3 endometrioid | Yes | Yes | Selectively | Optional |
| Serous / clear-cell | Yes | Yes | Consider | Yes — baseline |
| Carcinosarcoma | Yes | Yes | Consider | Yes — baseline |
Monitoring and Follow-Up
Surveillance after primary treatment is risk-stratified by stage, histology, and now molecular subgroup. The majority of recurrences occur within the first three years and most are detected on symptom-driven evaluation, not routine imaging.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| Clinical exam (incl. pelvic and vaginal vault) | Every 3–6 months for 3 years, then every 6–12 months | Vaginal vault nodularity, palpable mass, lymphadenopathy | Skipping the speculum exam in asymptomatic patients |
| CA-125 (high-risk histology only) | Each visit if elevated at baseline | Sustained doubling from nadir | Reacting to small fluctuations in low-grade tumors where the marker is unreliable |
| Imaging (CT or MRI) | Symptom-driven; routine surveillance imaging not required for low-risk disease | New mass, nodal disease, peritoneal nodules | Over-imaging in low-risk patients; under-imaging in high-grade or p53-abnormal tumors |
| Symptom counselling | Every visit | Vaginal bleeding, pelvic pain, weight loss, persistent cough | Patient under-reports symptoms; provide a written checklist |
Counsel every patient on warning symptoms (new vaginal bleeding, pelvic pain, weight loss) and the importance of prompt re-evaluation rather than waiting for the next scheduled visit.
Strong Rec Moderate Evidence ESGO 2021 NCCN 2024Discuss menopausal symptom management, sexual health, and lifestyle modification — obesity persists as the dominant risk factor for second primary endometrial cancer.
Strong Rec Moderate Evidence ESGO 2021Evidence in Context
What the evidence shows, where the major guideline bodies agree, and where the open questions still sit.
Where ESGO, NCCN, and ACOG agree
All three frameworks converge on the 4 mm postmenopausal endometrial thickness threshold, the centrality of office endometrial biopsy, the use of pelvic MRI for local staging, and the now-universal recommendation for molecular classification on every newly diagnosed tumor. Sentinel lymph node mapping is endorsed by all three for apparent uterine-confined disease.
Where the guidelines differ
Premenopausal sampling age cutoff: ACOG uses 45 years; some European guidelines suggest 40. POLE testing penetration: ESGO recommends it for every case; NCCN positions it as appropriate when results will alter management. Adjuvant therapy for POLE-ultramutated Stage I: The RAINBO PORTEC-4a trial supports de-escalation, but uptake varies.
What TCGA changed
The 2013 TCGA analysis showed that endometrioid and serous carcinomas are not crisp morphologic categories but overlap on a molecular spectrum — a meaningful subset of grade 3 endometrioid tumors carry p53 mutations and behave like serous cancers, while a smaller subset of serous-appearing tumors are POLE-ultramutated and behave indolently. The endometrial cancer workup now leans on the molecular result to resolve such mismatches.
Sentinel lymph node mapping: what the FIRES trial showed
The FIRES trial established that sentinel lymph node mapping with indocyanine green and cervical injection identifies nodal metastasis with a sensitivity above 95 percent, with a false-negative rate of about 3 percent. The morbidity reduction compared with full lymphadenectomy is substantial — particularly lower-extremity lymphedema, which can affect quality of life for years.
References
- 1.Concin N, Matias-Guiu X, Vergote I, et al. ESGO/ESTRO/ESP guidelines for the management of patients with endometrial carcinoma. Int J Gynecol Cancer. 2021;31(1):12–39. doi:10.1136/ijgc-2020-002230
- 2.Cancer Genome Atlas Research Network, Kandoth C, Schultz N, et al. Integrated genomic characterization of endometrial carcinoma. Nature. 2013;497(7447):67–73. doi:10.1038/nature12113
- 3.León-Castillo A, de Boer SM, Powell ME, et al. Molecular Classification of the PORTEC-3 Trial for High-Risk Endometrial Cancer: Impact on Prognosis and Benefit From Adjuvant Therapy. J Clin Oncol. 2020;38(29):3388–3397. doi:10.1200/JCO.20.00549
- 4.Rossi EC, Kowalski LD, Scalici J, et al. A comparison of sentinel lymph node biopsy to lymphadenectomy for endometrial cancer staging (FIRES trial): a multicentre, prospective, cohort study. Lancet Oncol. 2017;18(3):384–392. doi:10.1016/S1470-2045(17)30068-2
- 5.ACOG Committee Opinion No. 734: The Role of Transvaginal Ultrasonography in Evaluating the Endometrium of Women With Postmenopausal Bleeding. Obstet Gynecol. 2018;131(5):e124–e129. doi:10.1097/AOG.0000000000002631
- 6.Walker JL, Piedmonte MR, Spirtos NM, et al. Recurrence and survival after random assignment to laparoscopy versus laparotomy for comprehensive surgical staging of uterine cancer: Gynecologic Oncology Group LAP2 Study. J Clin Oncol. 2012;30(7):695–700. doi:10.1200/JCO.2011.38.8645
How to Read the Evidence Tags
Every recommendation in this article carries two tags — one for the strength of the recommendation, one for the quality of the underlying evidence — alongside the source body. These are Medaptly’s simplified interpretations and do not reproduce any guideline’s full classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise to the patient. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |