
Heavy Menstrual Bleeding Treatment: 7 Proven Outpatient Steps
Clinical Practice Update — Hormonal, Non-Hormonal, and Procedural Options for Adult Women
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based outpatient heavy menstrual bleeding treatment in adult women without confirmed structural pathology
- Target Audience
- Family physicians, gynecologists, primary care nurse practitioners, residents in obstetrics and gynecology
- Setting
- Primary care, outpatient gynecology clinic, women’s health assessment
- Source Evidence
- •NICE Guideline NG88: Heavy Menstrual Bleeding — Assessment and Management (2018, updated 2021)
- •ACOG Practice Bulletin No. 128 — Diagnosis of Abnormal Uterine Bleeding in Reproductive-Aged Women
- •FIGO PALM-COEIN Classification System (Munro et al., Int J Gynaecol Obstet 2018)
- •ECLIPSE Trial — LNG-IUS vs Usual Medical Treatment for Menorrhagia (Gupta et al., NEJM 2013)
Key Clinical Takeaways
Effective heavy menstrual bleeding treatment starts with classifying the cause, ruling out structural pathology, and matching the agent to the patient’s fertility goals and comorbidities. The shift in modern outpatient heavy menstrual bleeding treatment is that medical therapy — particularly the levonorgestrel intrauterine system — now produces outcomes comparable to surgery in suitable candidates. The points below distill the evidence into actionable decisions for the consultation room.
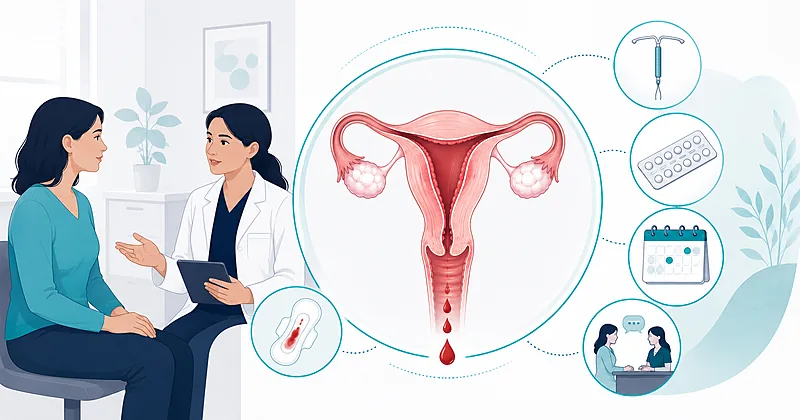
- 1Classify every patient using PALM-COEIN classification before initiating heavy menstrual bleeding treatment — structural vs non-structural causes guide everything that follows
- 2Offer the levonorgestrel intrauterine system (LNG-IUS) as first-line medical therapy when no structural lesion is suspected and contraception is acceptable
- 3Prescribe tranexamic acid as the best non-hormonal option for women actively trying to conceive or declining hormones
- 4Consider combined hormonal contraceptives when cycle regulation, dysmenorrhea, or contraception are also priorities
- 5Perform endometrial sampling in all women aged 45 and over, and in younger women with risk factors for endometrial pathology
- 6Refer for endometrial ablation when medical heavy menstrual bleeding treatment has failed and childbearing is complete
- 7Treat iron deficiency anemia in parallel — do not wait for menstrual control before starting iron replacement
- 8Reassess response at 3 months — if there is no meaningful improvement, switch agents or escalate referral
Initial Assessment Before Heavy Menstrual Bleeding Treatment
Heavy menstrual bleeding is defined by its impact on the woman — quality of life, function, work absence, anemia — not by a millilitre threshold. The first visit should rule out structural pathology, identify modifiable contributors, and quantify anemia before any prescribing decision is made.
Take a structured history covering bleeding pattern, duration, flooding, clots, dysmenorrhea, fertility plans, sexual activity, and impact on daily function. Quality-of-life questions are central to deciding whether heavy menstrual bleeding treatment is needed.
Strong Rec High Evidence NICE NG88 2021Order a full blood count for every woman presenting with heavy menstrual bleeding. Document ferritin if anemia is present or borderline — iron stores often lag the haemoglobin.
Strong Rec High Evidence NICE NG88 2021Perform endometrial biopsy in women aged 45 or over with persistent heavy or irregular bleeding, and in younger women with risk factors for endometrial hyperplasia (obesity, polycystic ovary syndrome, unopposed estrogen, tamoxifen, family history of Lynch syndrome).
Strong Rec Moderate Evidence ACOG NICE NG88 2021Arrange transvaginal ultrasound when the history or examination suggests a structural lesion: bulky or tender uterus, intermenstrual bleeding, dyspareunia, or palpable mass.
Strong Rec Moderate Evidence NICE NG88 2021Screen for an inherited bleeding disorder — particularly von Willebrand disease — in women with heavy bleeding since menarche, a family history of bleeding, or postpartum or surgical bleeding episodes.
Moderate Rec Moderate Evidence ACOGCheck thyroid function only when symptoms suggest thyroid dysfunction. Routine TSH screening in every woman with heavy bleeding is low-yield.
Conditional Rec Low Evidence NICE NG88 2021Red Flag Features Requiring Same-Visit Referral
Postcoital bleeding, persistent intermenstrual bleeding, pelvic mass, suspicious cervix on examination, postmenopausal bleeding, or rapid clinical deterioration with severe anemia.
These features change the workup from outpatient heavy menstrual bleeding treatment to an urgent referral for malignancy exclusion.
LNG-IUS: First-Line Medical Therapy for Heavy Menstrual Bleeding
The 52 mg levonorgestrel intrauterine system reduces menstrual blood loss by approximately 80–90% within six months in women without structural pathology. The ECLIPSE trial demonstrated that LNG-IUS produces sustained improvements in quality of life comparable to standard oral medical therapy at two years, with fewer treatment switches and lower hysterectomy rates.
Offer the 52 mg LNG-IUS as first-line heavy menstrual bleeding treatment in women without confirmed submucosal fibroids or other structural pathology, provided contraception is acceptable. LNG-IUS counseling should cover the expected pattern of irregular spotting for the first 3–6 months.
Strong Rec High Evidence NICE NG88 2021 ECLIPSE 2013Counsel patients to commit to at least 6 months of LNG-IUS use before judging effect. Early removal — commonly at 2–3 months for irregular spotting — is the leading cause of treatment failure that was never a treatment failure.
Strong Rec Moderate Evidence NICE NG88 2021Consider LNG-IUS even when uterine fibroids are present, provided the cavity is normal on ultrasound or saline-infusion sonography — intramural and subserosal fibroids are not a contraindication.
Moderate Rec Moderate Evidence NICE NG88 2021Do not insert LNG-IUS when there is confirmed submucosal fibroid distortion of the cavity, untreated genital infection, or undiagnosed postcoital or postmenopausal bleeding.
Against Moderate Evidence NICE NG88 2021Tranexamic Acid and Non-Hormonal Heavy Menstrual Bleeding Treatment
Non-hormonal options matter for two groups: women actively trying to conceive, and women who decline or cannot tolerate hormonal heavy menstrual bleeding treatment. Tranexamic acid is the most effective non-hormonal agent, with non-steroidal anti-inflammatory drugs offering a useful adjunct when dysmenorrhea is also present.
Prescribe tranexamic acid 1 g three to four times daily for up to four days during menstruation as first-line non-hormonal heavy menstrual bleeding treatment. Reduces flow by approximately 40–50% and can be started by the patient at the onset of each cycle.
Strong Rec High Evidence NICE NG88 2021 ACOGAdd mefenamic acid 500 mg three times daily or naproxen 500 mg twice daily from the start of menstruation for women whose heavy bleeding is accompanied by dysmenorrhea. Reduces flow modestly and treats pain in parallel.
Moderate Rec Moderate Evidence NICE NG88 2021Combine tranexamic acid with an NSAID when single-agent therapy is insufficient and the woman is trying to conceive — the combination is additive and neither agent affects fertility.
Moderate Rec Low Evidence Expert ConsensusAvoid tranexamic acid in women with active thromboembolism, a clear personal history of unprovoked VTE, or known thrombophilia where antifibrinolytic therapy has not been individually risk-assessed.
Against Low Evidence Product LabellingChoosing the Right Hormonal Agent
When the LNG-IUS is declined or contraindicated, the hormonal options separate cleanly by what else the patient needs: cycle regulation, contraception, or short-term control while awaiting surgery. Each option has a distinct profile of side effects and a distinct best-fit patient.
Offer a combined oral contraceptive when the woman wants contraception, cycle regulation, or relief of premenstrual symptoms in addition to lighter periods, and there are no cardiovascular or migraine contraindications.
Moderate Rec Moderate Evidence NICE NG88 2021 ACOGConsider cyclical oral progestogens (norethisterone 5 mg three times daily on days 5–26 of the cycle) as a short-term measure when other options are unsuitable. Effective for flow reduction but commonly poorly tolerated long term.
Conditional Rec Moderate Evidence NICE NG88 2021Consider depot medroxyprogesterone acetate (DMPA) when long-acting contraception is desired and the LNG-IUS is declined — expect amenorrhea in many users by 12 months. Discuss bone density implications for use beyond 2 years.
Conditional Rec Moderate Evidence ACOGReserve GnRH analogues for pre-surgical control in women with anemia awaiting procedural management of fibroids. Limit duration to 6 months unless add-back therapy is used.
Conditional Rec Moderate Evidence NICE NG88 2021Do not use luteal-phase progestogens (days 15–26 only) for heavy menstrual bleeding treatment — this short regimen is ineffective for flow reduction.
Against Moderate Evidence NICE NG88 2021When to Refer for Endometrial Ablation
Endometrial ablation has a clear place: women who have completed childbearing, in whom medical heavy menstrual bleeding treatment has failed or is unacceptable, and whose uterine cavity is suitable. It is uterus-sparing but is not a contraceptive procedure, and is not a route back to fertility.
Refer for endometrial ablation when (a) the woman has completed her family, (b) medical heavy menstrual bleeding treatment has failed or been declined, and (c) the cavity is normal or near-normal on ultrasound. Discuss as one of several hysterectomy alternatives.
Strong Rec High Evidence NICE NG88 2021 ACOGCounsel that ablation reduces but does not eliminate flow — expect amenorrhea in 30–50% and lighter menses in most of the remainder. Re-treatment or hysterectomy is required in roughly one in five at five years.
Strong Rec High Evidence ACOGEnsure reliable contraception continues after ablation. Pregnancy after ablation is rare but high-risk — abnormal placentation, miscarriage, and ectopic pregnancy are all over-represented.
Strong Rec Moderate Evidence ACOGDo not offer ablation as first-line surgical management in women with significant uterine enlargement, severe adenomyosis, large or cavity-distorting fibroids, or where future childbearing is desired.
Against Moderate Evidence NICE NG88 2021Consider hysterectomy when other options have failed, are contraindicated, or where coexisting pathology (large symptomatic fibroids, severe endometriosis) justifies definitive surgery and the woman has been counselled on alternatives.
Moderate Rec High Evidence NICE NG88 2021Clinical Decision Pathway
A practical, question-based approach. Work through the questions in order — each answer narrows the choice of agent without prescribing a single algorithm.
Comparing the Outpatient Treatment Options
A side-by-side view organised by drug or device, not by guideline section. Use this when matching the patient profile to the agent in the consultation room.
Drug and Device Comparison
| Option | Typical Flow Reduction | Best Suited For | Practical Tips | Key Cautions |
|---|---|---|---|---|
| LNG-IUS (52 mg) | 80–90% at 6 months | Family complete or contraception desired; no cavity distortion | Time insertion to days 5–10; pre-counsel on 3-month spotting | Submucosal fibroids, untreated PID, suspected malignancy |
| Tranexamic acid | 40–50% during use | Conceiving women; hormone avoidance; needle-phobic patients | Start with the first heavy flow; 1 g TID-QID for up to 4 days | Active VTE, known thrombophilia (case-by-case) |
| NSAID (mefenamic, naproxen) | 20–30% during use | Concurrent dysmenorrhea; adjunct to tranexamic acid | Start at flow onset; take with food | Peptic ulcer, asthma triggered by NSAIDs, advanced renal disease |
| Combined oral contraceptive | 40–50% over 3–6 cycles | Contraception + cycle regulation desired; younger women | Trial 3 cycles before judging effect | Migraine with aura, smoking ≥ 35y, BMI ≥ 35, VTE history |
| Cyclical oral progestogen | ~50% on long regimen (days 5–26) | Short-term control when other options unsuitable | Bridge use; not for long-term first-line | Mood disturbance, bloating, breast tenderness common |
| Endometrial ablation | Amenorrhea in 30–50%; significant reduction in most | Family complete; medical therapy failed; normal cavity | Continue contraception post-procedure | Future fertility desired, cavity-distorting fibroids, untreated dysplasia |
- Flow reduction estimates summarise published trial data and meta-analyses; individual response varies.
- “Trying to conceive” overrides all other choices — hormonal options are inappropriate.
Monitoring and Follow-Up After Heavy Menstrual Bleeding Treatment
Follow-up is where heavy menstrual bleeding treatment is won or lost. Most failures are not pharmacologic — they are women who stopped too early, were never reviewed, or whose anemia was never addressed in parallel.
| Parameter | When to Check | Action Threshold | What to Do | Common Pitfalls |
|---|---|---|---|---|
| Subjective flow | 3 months from start | No meaningful improvement reported | Switch class (e.g., COC → LNG-IUS) before referral | Judging LNG-IUS at 3 months instead of 6 |
| Quality of life | Each review | Still affecting work, sleep, or activities | Escalate even if flow is “objectively better” | Anchoring on volume rather than impact |
| FBC and ferritin | 3 months after starting iron | Hb still below local reference or ferritin < 30 | Continue oral iron; consider IV iron if persistently low | Stopping iron once Hb normalises — replete stores |
| Iron deficiency anemia | From day 1 of treatment | Any biochemical iron deficiency | Start oral iron in parallel; do not wait for flow control | Deferring iron pending haematinic confirmation |
| Endometrial sampling | When breakthrough bleeding persists past 6 months on LNG-IUS in older women | Persistent unscheduled bleeding | Outpatient biopsy ± saline sonography | Attributing late-onset bleeding to the device without investigation |
Evidence in Context
Where the major guidelines agree, where they diverge, and what the landmark trials actually showed about heavy menstrual bleeding treatment.
Where NICE and ACOG Agree
Both frameworks centre the assessment on patient-reported impact rather than volume thresholds, support empiric treatment when structural pathology is unlikely, position the LNG-IUS as the most effective medical option, and reserve hysterectomy for women in whom less invasive options have failed or are unacceptable. Both also recommend endometrial sampling in older women and those with risk factors for hyperplasia.
Where NICE and ACOG Differ
The thresholds for routine investigation differ. NICE NG88 places greater emphasis on empiric treatment without ultrasound in women under 45 without red flags, whereas ACOG materials place earlier weight on imaging when fibroids or adenomyosis are clinically plausible. NICE is more prescriptive about LNG-IUS as the explicit first-line; ACOG presents a wider menu of equivalent options to be matched to patient preference.
The ECLIPSE Trial: What It Showed and Didn’t Show
The ECLIPSE trial randomised women in primary care with heavy menstrual bleeding to LNG-IUS or standard oral medical therapy chosen by the clinician. At two years, both groups showed substantial improvements in quality of life, but the LNG-IUS group had larger gains, lower rates of treatment switching, and lower hysterectomy referral. ECLIPSE did not compare LNG-IUS head-to-head with ablation, and its primary outcome was patient-reported impact rather than volume measurement.
PALM-COEIN: Why the Classification Matters
The FIGO PALM-COEIN system splits causes of abnormal uterine bleeding into structural (polyp, adenomyosis, leiomyoma, malignancy) and non-structural (coagulopathy, ovulatory dysfunction, endometrial, iatrogenic, not yet classified) categories. In practice, this matters because a patient labelled “AUB-L” (leiomyoma) may need a different first-line approach — particularly if the fibroid distorts the cavity — than a patient with “AUB-O” (ovulatory dysfunction), where hormonal cycle regulation is the obvious starting point.
Ablation vs LNG-IUS: How They Compare
Direct comparisons show similar patient satisfaction at one and two years, with ablation producing higher rates of amenorrhea but with a small population requiring re-treatment or hysterectomy. LNG-IUS preserves a path to reversal and provides contraception; ablation does neither. The choice usually comes down to patient preference, tolerance for ongoing menses, and willingness to retain a device.
References
- 1.National Institute for Health and Care Excellence. Heavy menstrual bleeding: assessment and management. NICE guideline NG88. 2018; updated 2021. nice.org.uk/guidance/ng88
- 2.American College of Obstetricians and Gynecologists. Diagnosis of abnormal uterine bleeding in reproductive-aged women. ACOG Practice Bulletin No. 128. Obstet Gynecol. 2012;120(1):197–206. doi:10.1097/AOG.0b013e318262e320
- 3.Munro MG, Critchley HOD, Fraser IS; FIGO Menstrual Disorders Committee. The two FIGO systems for normal and abnormal uterine bleeding symptoms and classification of causes of abnormal uterine bleeding in the reproductive years: 2018 revisions. Int J Gynaecol Obstet. 2018;143(3):393–408. doi:10.1002/ijgo.12666
- 4.Gupta J, Kai J, Middleton L, Pattison H, Gray R, Daniels J; ECLIPSE Trial Collaborative Group. Levonorgestrel intrauterine system versus medical therapy for menorrhagia. N Engl J Med. 2013;368(2):128–137. doi:10.1056/NEJMoa1204724
How to Read the Evidence Tags
Every recommendation carries two tags — one for recommendation strength, one for evidence quality — plus a source citation. These are Medaptly’s own simplified interpretations and do not reproduce any guideline body’s full classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | Benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |