
Gastric Cancer Surgical Management: 7 Critical Decisions
Clinical Practice Update — Endoscopic Staging, Neoadjuvant Chemotherapy, and Extent of Lymphadenectomy
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Workup, perioperative chemotherapy, and surgical strategy for resectable gastric adenocarcinoma in adults
- Target Audience
- General surgeons, surgical oncologists, gastroenterologists, medical oncologists, surgical residents
- Setting
- Tertiary hospital, multidisciplinary cancer centers, surgical oncology clinic
- Source Evidence
- •NCCN Clinical Practice Guidelines — Gastric Cancer (2024)
- •ESMO Clinical Practice Guidelines — Gastric Cancer (2022)
- •Japanese Gastric Cancer Treatment Guidelines, 6th Edition (JGCA 2021)
- •FLOT4 Trial — Perioperative FLOT vs ECF/ECX (Lancet, 2019)
- •Dutch D1D2 Trial — 15-Year Follow-up (Lancet Oncol, 2010)
Key Clinical Takeaways
Effective gastric cancer surgical management rests on three pillars: accurate pre-treatment staging, multidisciplinary use of perioperative chemotherapy in fit patients with locally advanced disease, and a properly performed D2 lymphadenectomy at a high-volume center. The takeaways below distill the workup-to-surgery pathway into actionable decisions you can use in the operating room and the tumor board.
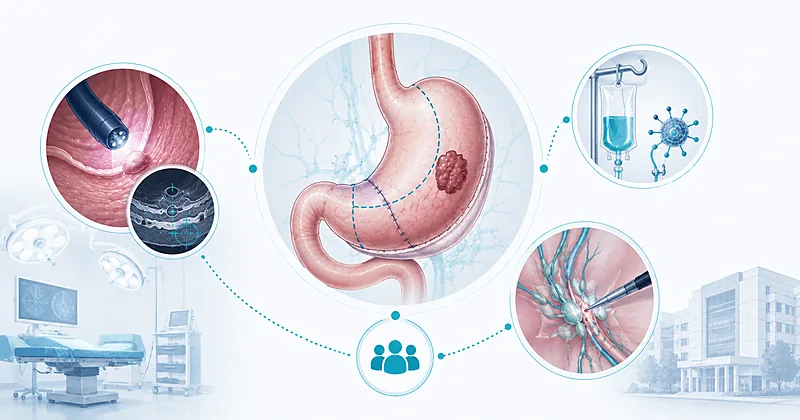
- 1Combine upper endoscopy with biopsy, CT chest/abdomen/pelvis, and EUS staging in every newly diagnosed patient before deciding the surgical plan.
- 2Perform diagnostic laparoscopy with peritoneal washings for any cT3+ or cN+ tumor before committing to open resection — occult peritoneal disease changes the plan.
- 3Offer perioperative FLOT (4 cycles before, 4 cycles after surgery) to fit patients with cT2N0 or any cT3-T4 or node-positive disease.
- 4Reserve endoscopic submucosal dissection (ESD) for highly selected cT1a, well-differentiated, non-ulcerated lesions under 2 cm.
- 5Choose subtotal gastrectomy for distal tumors when a 5 cm proximal margin can be achieved; choose total gastrectomy for proximal, diffuse-type, or linitis plastica disease.
- 6Perform a spleen-preserving D2 lymphadenectomy as the standard of care for all curative-intent resections at experienced centers.
- 7Examine at least 16 lymph nodes pathologically for adequate staging — aim for 30 or more when possible.
- 8Do not routinely add splenectomy or pancreatectomy to D2 dissection unless direct tumor invasion is present.
- 9Refer Siewert type I/II gastroesophageal junction tumors for esophagectomy-style resection; Siewert III is managed as proximal gastric cancer.
- 10Manage every case through a multidisciplinary tumor board — gastric cancer surgical management is too nuanced for a single specialty to decide alone.
Initial Workup and Diagnostic Staging
Before any decision about gastric cancer surgical management can be made, the surgeon needs a complete staging picture. Skipping any step risks under-treatment, over-treatment, or an avoidable non-curative laparotomy.
Perform upper endoscopy with multiple biopsies (typically 6–8 from the edges and base of any suspicious lesion) to obtain histologic confirmation and Lauren classification.
Strong Rec High Evidence NCCN 2024 ESMO 2022Obtain a contrast-enhanced CT of the chest, abdomen, and pelvis in every patient to assess local extent, regional nodes, and distant metastases.
Strong Rec High Evidence NCCN 2024Perform diagnostic laparoscopy with peritoneal washings before laparotomy for any cT3, cT4, or cN+ tumor on cross-sectional imaging. Occult peritoneal disease is found in 20–30% of these cases and shifts the patient to palliative therapy.
Strong Rec Moderate Evidence NCCN 2024 ESMO 2022Consider FDG-PET/CT selectively when the CT is equivocal for distant disease — not for routine local staging, where its accuracy is limited (particularly for diffuse-type and signet-ring histology).
Conditional Rec Low Evidence NCCN 2024Test for HER2 (immunohistochemistry ± FISH), mismatch repair status, and PD-L1 expression on every newly diagnosed advanced or metastatic tumor — the results steer first-line systemic therapy.
Strong Rec High Evidence NCCN 2024 ESMO 2022Endoscopic Staging in Gastric Cancer Surgical Management
Endoscopic ultrasound (EUS) is the most accurate modality available for T staging and a useful adjunct for N staging. In gastric cancer surgical management, the EUS finding most likely to change practice is the distinction between T1a (mucosal) and T1b (submucosal) disease — the cut-off between endoscopic and surgical therapy.
Perform EUS to refine T and N stage in every patient being considered for endoscopic resection, neoadjuvant therapy, or primary surgery. EUS accuracy for T stage is roughly 75–85%; for N stage, 65–70%.
Strong Rec Moderate Evidence NCCN 2024 ESMO 2022Use EUS-guided fine needle aspiration of suspicious lymph nodes when the cytologic result will alter the management plan (for example, confirming N+ status to justify neoadjuvant chemotherapy).
Moderate Rec Moderate Evidence ESMO 2022Refer for endoscopic submucosal dissection only when all expanded criteria are met: cT1a depth on EUS, well or moderately differentiated histology, no ulceration, and size at or below 2 cm. Outside these limits, surgery remains the standard.
Strong Rec High Evidence JGCA 2021 ESMO 2022Counsel patients that EUS routinely under-stages diffuse-type and linitis plastica disease. Lower the threshold for diagnostic laparoscopy and neoadjuvant therapy in these histologies regardless of the EUS T stage.
Moderate Rec Low Evidence NCCN 2024Endoscopic Resection: When ESD Replaces Surgery
| Patient Profile | Recommended Approach | Key Caveat | Practical Tip |
|---|---|---|---|
| cT1a, well-differentiated, ≤2 cm, no ulceration | ESD — en bloc resection | Must confirm depth on en-bloc specimen | Insist on en-bloc, not piecemeal |
| cT1a, well-differentiated, >2 cm or with ulceration | ESD considered — expanded criteria | Risk of lymph node metastasis is non-zero | Discuss surgery as alternative |
| cT1a, undifferentiated or signet-ring | Surgery preferred | Higher rate of skip nodal metastases | ESD only in expert centers |
| cT1b (submucosal invasion) | Gastrectomy with D1+ or D2 lymphadenectomy | ~15–20% nodal positivity rate | Do not stop at ESD even if margins are clear |
| cT2 or deeper | Multidisciplinary workup, consider neoadjuvant | Endoscopic therapy not appropriate | Move to surgical pathway |
Neoadjuvant and Perioperative Chemotherapy
Perioperative chemotherapy is now the standard of care in the West for resectable locally advanced gastric adenocarcinoma. The FLOT4 trial showed that perioperative FLOT delivered a median overall survival of 50 months compared with 35 months on ECF/ECX, reshaping practice. Eastern guidelines diverge: Japan and Korea favour upfront surgery followed by adjuvant S-1 or capecitabine/oxaliplatin, reflecting their stage-shifted disease through screening programmes.
Start the FLOT regimen (5-FU, leucovorin, oxaliplatin, docetaxel) as 4 preoperative cycles plus 4 postoperative cycles for fit patients (ECOG 0–1) with cT2N0 disease or any cT3–T4 or node-positive resectable adenocarcinoma.
Strong Rec High Evidence FLOT4 Trial 2019 ESMO 2022 NCCN 2024Consider preoperative chemoradiation (CROSS regimen: carboplatin + paclitaxel with 41.4 Gy) for Siewert I and II gastroesophageal junction tumors, where the evidence base for trimodality therapy is strongest.
Moderate Rec High Evidence CROSS Trial 2012 NCCN 2024Restage with contrast CT after preoperative chemotherapy (typically 2–4 weeks after the final cycle, before surgery) to confirm no interval progression and to plan the operation. PET response can also be informative but is not routinely required.
Strong Rec Moderate Evidence NCCN 2024Reassess at 4–6 weeks after the final preoperative cycle to allow recovery of neutrophil counts, mucositis, and peripheral neuropathy before proceeding to a major upper-GI resection.
Strong Rec Low Evidence Expert ConsensusAvoid neoadjuvant chemotherapy for clearly cT1 tumors — the absolute benefit is small and the toxicity is not justified when upfront surgery (or ESD when criteria are met) gives excellent results.
Against Moderate Evidence NCCN 2024Resection Principles: Subtotal vs Total Gastrectomy
The extent of resection is dictated by tumor location, histologic subtype (intestinal vs diffuse Lauren classification), and the surgeon’s ability to obtain a negative proximal margin. Quality-of-life data favour subtotal over total gastrectomy when oncologic equivalence can be achieved.
Perform subtotal (distal) gastrectomy for antral or distal-body tumors when a 5 cm proximal margin (intestinal-type) or 8 cm margin (diffuse-type) is achievable.
Strong Rec High Evidence NCCN 2024 JGCA 2021Perform total gastrectomy for proximal, mid-body, diffuse-type, or linitis plastica tumors, or when margin requirements cannot be met by a subtotal resection.
Strong Rec High Evidence NCCN 2024 ESMO 2022Confirm a negative proximal margin with intraoperative frozen section in any case where the margin is borderline (e.g., 3–5 cm by direct inspection in diffuse-type histology).
Strong Rec Moderate Evidence NCCN 2024Consider laparoscopic or robotic distal gastrectomy for clinical stage I–III disease at experienced centers — KLASS-02 and LOGICA demonstrated oncologic non-inferiority with reduced morbidity.
Moderate Rec High Evidence KLASS-02 2019 NCCN 2024Resection Choice by Tumor Location and Histology
| Clinical Scenario | Preferred Resection | Reconstruction | Where Surgeons Disagree |
|---|---|---|---|
| Antrum / distal body, intestinal-type | Subtotal gastrectomy | Roux-en-Y or Billroth II | Margin length in older patients |
| Mid-body, intestinal-type | Total gastrectomy | Roux-en-Y esophagojejunostomy | Pouch vs no pouch |
| Diffuse-type, any location | Total gastrectomy | Roux-en-Y | Need for 8 cm proximal margin |
| Proximal gastric / Siewert III | Total gastrectomy (transhiatal extension) | Roux-en-Y esophagojejunostomy | Proximal gastrectomy in selected cases |
| GEJ Siewert classification I/II | Esophagectomy with proximal gastrectomy | Gastric pull-up or jejunal interposition | Ivor-Lewis vs transhiatal approach |
Extent of Lymphadenectomy in Gastric Cancer Surgical Management
Nothing has shaped modern gastric cancer surgical management more than the global convergence on D2 lymphadenectomy. Once controversial in Western practice, the 15-year follow-up of the Dutch D1D2 trial confirmed a gastric-cancer-specific survival advantage for D2 over D1, provided morbidity is controlled by spleen-preserving technique and a high-volume operator.
Perform a spleen-preserving D2 lymphadenectomy as the standard of care for any curative-intent resection of cT2–T4 or node-positive gastric cancer at a high-volume center.
Strong Rec High Evidence Dutch D1D2 2010 JGCA 2021 ESMO 2022Examine a minimum of 16 lymph nodes on the surgical specimen for accurate AJCC staging. Aim for at least 30 nodes — higher counts correlate with better stage-specific survival.
Strong Rec High Evidence AJCC 8th Edition NCCN 2024Do not routinely add splenectomy or distal pancreatectomy to the D2 dissection. Limit these to cases of direct tumor invasion confirmed intraoperatively.
Against High Evidence JCOG0110 Trial JGCA 2021Avoid routine extended (D2+ or D3) dissections including para-aortic nodes. The JCOG9501 trial showed no survival benefit over D2 but greater morbidity.
Against High Evidence JCOG9501 Trial JGCA 2021Consider modified D1+ dissection for cT1N0 disease where full D2 dissection is not indicated. Stations vary by resection type but include perigastric nodes plus stations 7, 8a, and 9.
Moderate Rec Moderate Evidence JGCA 2021Lymph Node Station Reference for D2 Dissection
| Station Group | Stations Included | Required For | Operative Tip |
|---|---|---|---|
| Perigastric (D1) | 1–6 (cardia, lesser/greater curvature) | All curative resections | Mobilize greater omentum first |
| Left gastric artery | 7 | D1+ and D2 | Ligate at celiac origin |
| Common hepatic artery | 8a (anterior) | D1+ and D2 | Watch for replaced left hepatic |
| Celiac artery | 9 | D1+ and D2 | Skeletonize celiac trunk |
| Splenic hilum / artery | 10 (hilum), 11p/d (artery) | D2 only (total gastrectomy) | Preserve spleen and pancreas |
| Hepatoduodenal ligament | 12a | D2 only | Skeletonize along proper hepatic |
Clinical Decision Pathway
A practical question-based pathway for the surgeon presented with a new gastric adenocarcinoma. Work through the questions in order.
Postoperative Monitoring and Surveillance
Surveillance after curative resection serves two purposes: detecting recurrence early enough to act on it, and managing the nutritional and metabolic sequelae of gastrectomy.
| Parameter | When to Check | What to Look For | Common Pitfall |
|---|---|---|---|
| Clinical review | Every 3 months × 2 yr, then 6 monthly × 3 yr, then annually | Weight loss, dysphagia, pain, performance status | Attributing weight loss to “expected” rather than recurrence |
| CT chest/abdomen/pelvis | Every 6–12 months for 5 years | Peritoneal disease, liver metastases, nodal recurrence | Skipping after 3 years — recurrences happen later in diffuse-type |
| Endoscopy | Annually × 3–5 years (especially post-subtotal) | Anastomotic recurrence, metachronous lesion in gastric remnant | Inadequate biopsy of suspicious areas |
| Vitamin B12, iron, vitamin D | 6 months postop, then annually for life | vitamin B12 deficiency, anemia, osteoporosis | Stopping replacement — B12 is lifelong after total gastrectomy |
| Nutrition assessment | Every visit in year 1 | Dumping syndrome, early satiety, >10% weight loss | Not involving a dietitian early enough |
Evidence in Context
Where the major guidelines agree, where they diverge, and what the practice-changing trials actually showed.
Where NCCN, ESMO, and JGCA Agree
All three frameworks converge on D2 lymphadenectomy as the standard of care for resectable advanced disease, on the importance of accurate preoperative staging including EUS for early lesions, and on R0 resection as the primary surgical objective. They also agree on the role of staging laparoscopy for locally advanced tumors.
Where Western and Eastern Guidelines Diverge
Perioperative vs adjuvant chemotherapy: NCCN and ESMO endorse perioperative FLOT as preferred for locally advanced disease. Japanese and Korean guidelines favour upfront D2 surgery followed by adjuvant S-1 or CapeOx. This is partly explained by stage at presentation (more early disease detected through Asian screening programmes) and partly by historical operative outcomes.
ESD eligibility: JGCA accepts wider “expanded criteria” for ESD than most Western centers, reflecting greater volume and experience.
FLOT4: Why FLOT Replaced ECF/ECX
The FLOT4 trial randomized roughly 700 patients with cT2+ or node-positive gastric or GEJ adenocarcinoma to perioperative ECF/ECX or FLOT. Median overall survival was 50 months on FLOT versus 35 months on ECF/ECX, with higher pathologic complete response rates. Tolerability was broadly comparable. FLOT became the new Western reference regimen on the strength of these data.
Dutch D1D2 Trial: The 15-Year Verdict on D2
The original Dutch D1D2 trial reported higher early morbidity and no overall survival advantage with D2 over D1 at 5 years, dampening Western enthusiasm for the wider dissection. The 15-year follow-up reversed that conclusion: gastric-cancer-specific survival and local-regional recurrence favoured D2. The trial established that morbidity is the price of inadequate technique — modern spleen-preserving D2 in high-volume centers delivers the survival benefit without the early cost.
Minimally Invasive Gastrectomy: KLASS-02 and LOGICA
KLASS-02 (Korea) and LOGICA (Netherlands) showed that laparoscopic distal gastrectomy with D2 is oncologically non-inferior to open surgery in expert hands, with lower wound morbidity and faster recovery. The data for laparoscopic total gastrectomy are more limited; KLASS-06 is awaited. Robotic platforms add cost without yet demonstrating clear oncologic advantage.
References
- 1.Al-Batran SE, Homann N, Pauligk C, et al. Perioperative chemotherapy with fluorouracil plus leucovorin, oxaliplatin, and docetaxel versus fluorouracil or capecitabine plus cisplatin and epirubicin for locally advanced, resectable gastric or gastro-oesophageal junction adenocarcinoma (FLOT4): a randomised, phase 2/3 trial. Lancet. 2019;393(10184):1948–1957. doi:10.1016/S0140-6736(18)32557-1
- 2.Songun I, Putter H, Kranenbarg EM, Sasako M, van de Velde CJ. Surgical treatment of gastric cancer: 15-year follow-up results of the randomised nationwide Dutch D1D2 trial. Lancet Oncol. 2010;11(5):439–449. doi:10.1016/S1470-2045(10)70070-X
- 3.Lordick F, Carneiro F, Cascinu S, et al. Gastric cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-up. Ann Oncol. 2022;33(10):1005–1020. doi:10.1016/j.annonc.2022.07.004
- 4.Japanese Gastric Cancer Association. Japanese gastric cancer treatment guidelines 2021 (6th edition). Gastric Cancer. 2023;26(1):1–25. doi:10.1007/s10120-022-01331-8
- 5.van Hagen P, Hulshof MC, van Lanschot JJ, et al. Preoperative chemoradiotherapy for esophageal or junctional cancer. N Engl J Med. 2012;366(22):2074–2084. doi:10.1056/NEJMoa1112088
- 6.Hyung WJ, Yang HK, Park YK, et al. Long-Term Outcomes of Laparoscopic Distal Gastrectomy for Locally Advanced Gastric Cancer: The KLASS-02-RCT Randomized Clinical Trial. J Clin Oncol. 2020;38(28):3304–3313. doi:10.1200/JCO.20.01210
- 7.National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Gastric Cancer (Version 2.2024). nccn.org/guidelines/category_1
How to Read the Evidence Tags
Every recommendation in this article carries two tags — recommendation strength and evidence quality — using Medaptly’s own simplified system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |