
Hidradenitis Suppurativa: Staging and Stepwise Treatment
Clinical Practice Update — Hurley Staging, Medical Therapy, and Surgical Escalation in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based hidradenitis suppurativa treatment in adults, from staging to escalation
- Target Audience
- Family physicians, dermatologists, surgeons, residents, nurse practitioners
- Setting
- Primary care, dermatology clinics, surgical referral
- Source Evidence
- •North American Clinical Management Guidelines for HS (JAAD, 2019)
- •European S1 Guideline for the Treatment of HS (JEADV, 2015)
- •PIONEER I & II — Adalimumab in Moderate-to-Severe HS (NEJM, 2016)
- •SUNSHINE & SUNRISE — Secukinumab in HS (Lancet, 2023)
Key Clinical Takeaways
Effective hidradenitis suppurativa treatment rests on matching therapy to disease burden. Stage the disease first, treat the inflammatory and structural components together, and escalate on a clear timeline when a patient fails to respond. The points below distill multi-source evidence into actionable rules for clinical practice.
- 1Stage every patient with Hurley staging at the first visit — it anchors all subsequent treatment decisions
- 2Begin every plan with smoking cessation and weight optimization — the two most powerful modifiable levers
- 3Topical clindamycin is the entry point for Hurley I disease confined to limited areas
- 4Combine oral clindamycin with rifampicin for a defined 10–12 week course in moderate disease
- 5Start a biologic when moderate-to-severe disease fails conventional therapy — do not delay escalation
- 6Surgery addresses fixed structural disease that drugs cannot reverse — sinus tracts and scarring
- 7Manage pain proactively at every stage — under-treated pain is the most common care gap
- 8Screen for the comorbidities that travel with HS: depression, metabolic syndrome, and inflammatory bowel disease
Staging Disease Before Hidradenitis Suppurativa Treatment
Staging is the foundation of rational hidradenitis suppurativa treatment because it sorts patients into broad management bands. The Hurley system, used for decades, separates disease by the presence of sinus tracts and scarring rather than by lesion count alone, which makes it fast and practical at the bedside.
The diagnosis remains clinical: recurrent painful nodules and abscesses in flexural sites (axillae, groin, inframammary, perineal), typically two or more flares over six months. The average diagnostic delay still stretches to several years, so a high index of suspicion in these locations matters more than any single test.
Assign a Hurley stage at the first consultation and record it. Stage I describes isolated nodules and abscesses without tracts or scarring; Stage II adds recurrent lesions with limited sinus tracts; Stage III is diffuse involvement with interconnected tracts across an entire region.
Strong Rec Moderate Evidence US HS Guidelines 2019Evaluate the dynamic disease burden alongside the static stage. A patient with frequent painful flares may warrant aggressive therapy even at a lower Hurley stage, so document flare frequency and the number of active sites.
Moderate Rec Low Evidence US HS Guidelines 2019Foundations of Care That Apply at Every Stage
Before any drug is prescribed, two background interventions improve outcomes across the whole severity spectrum. These run in parallel with staged pharmacotherapy, not instead of it.
Counsel every patient on smoking cessation at diagnosis and at every subsequent visit. The majority of patients with hidradenitis suppurativa are current or former smokers, and stopping is associated with reduced flare activity over time.
Strong Rec Moderate Evidence US HS Guidelines 2019Advise weight optimization where the patient carries excess weight, framing it as one lever among several rather than a precondition for treatment. Mechanical friction and metabolic inflammation both contribute to disease activity.
Moderate Rec Low Evidence EU HS Guideline 2015Ensure a pain management plan accompanies every treatment stage. Address acute flare pain and any chronic neuropathic component separately, and escalate analgesia in step with disease severity.
Strong Rec Low Evidence US HS Guidelines 2019Medical Hidradenitis Suppurativa Treatment by Stage
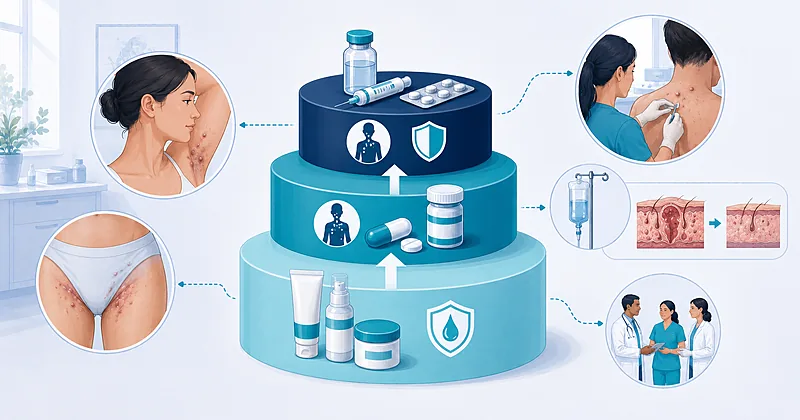
Medical hidradenitis suppurativa treatment follows a tiered logic: topical agents for localized mild disease, systemic antibiotics for moderate disease, hormonal options in selected patients, and biologics when inflammation persists despite these measures.
Tier 1 — Localized and Mild Disease
Prescribe topical clindamycin 1% solution applied twice daily for Hurley I disease limited to a small number of lesions. It is the standard first topical agent and can reduce pustules and inflammatory nodules.
Strong Rec Moderate Evidence EU HS Guideline 2015Consider intralesional corticosteroid injection for an individual inflamed nodule or early abscess to settle a localized flare quickly without systemic exposure.
Conditional Rec Low Evidence US HS Guidelines 2019Tier 2 — Moderate Disease
Prescribe the combination of oral clindamycin 300 mg twice daily with rifampicin 300 mg twice daily as a defined 10–12 week course for moderate, more widespread disease. The pairing targets both bacterial load and the inflammatory cascade.
Moderate Rec Moderate Evidence EU HS Guideline 2015Consider oral tetracycline-class therapy (such as doxycycline 100 mg twice daily) for up to 12 weeks as an alternative systemic option, applying antibiotic stewardship by setting a clear stop or reassessment date.
Conditional Rec Low Evidence US HS Guidelines 2019Evaluate for hormonal therapy in women whose flares track with the menstrual cycle. Combined oral contraceptives or spironolactone may reduce activity in this subgroup as an adjunct to other measures.
Conditional Rec Low Evidence US HS Guidelines 2019Tier 3 — Biologic Therapy for Moderate-to-Severe Disease
Start adalimumab for moderate-to-severe disease that has not responded to conventional systemic therapy. The pivotal randomized program established a weekly maintenance schedule after loading as an effective regimen for reducing abscess and inflammatory nodule counts.
Strong Rec High Evidence PIONEER I & II 2016Consider secukinumab as an alternative biologic, particularly where a TNF inhibitor has failed or is unsuitable. Recent phase III data support an IL-17 pathway option for sustained disease control, with latent tuberculosis screening completed before any biologic begins.
Moderate Rec High Evidence SUNSHINE & SUNRISE 2023Do not abandon a biologic prematurely. Allow an adequate trial of several months before judging response, since improvement in deep inflammatory disease accrues gradually rather than within the first few weeks.
Moderate Rec Moderate Evidence PIONEER I & II 2016Surgical Escalation for Fixed Structural Disease
Drugs calm inflammation, but they cannot reverse the sinus tracts, fibrosis, and scarring that define advanced disease. Surgery removes this fixed architecture, and it works best as a planned complement to medical therapy rather than a last resort.
Perform incision and drainage only for acute relief of a tense, painful abscess, while counselling the patient that recurrence at the same site is near-universal because the underlying tract remains.
Conditional Rec Low Evidence US HS Guidelines 2019Refer for wide local excision of a region with recurrent, fixed Hurley III disease. Removing the entire affected field offers the most durable local control where lesions cluster persistently.
Moderate Rec Moderate Evidence US HS Guidelines 2019Consider deroofing as a tissue-sparing alternative for individual recurrent sinus tracts and nodules. The procedure exposes and converts the tract under local anaesthetic and preserves more surrounding skin than excision.
Conditional Rec Moderate Evidence EU HS Guideline 2015Continue effective medical therapy through the perioperative period where feasible, combining drug control of inflammation with surgical removal of structural disease for the best composite outcome.
Moderate Rec Low Evidence US HS Guidelines 2019Clinical Decision Pathway
A practical, question-based route through staging and escalation. Work through the questions in order at each review.
Mapping Stage to First-Line Therapy
This table pairs each clinical picture with its entry-point therapy and the signal that should prompt escalation, organized by patient presentation rather than by drug class.
| Clinical Picture | Entry-Point Therapy | Escalate When | Practical Tips |
|---|---|---|---|
| Few nodules, one site (Hurley I) | Topical clindamycin 1% BID | No control by 8–12 weeks | Add intralesional steroid for an isolated flare. |
| Recurrent lesions, several sites (Hurley II) | Clindamycin + rifampicin, 10–12 wk | Active disease at course end | Warn about contraception interaction with rifampicin. |
| Cyclical flares in women | Add hormonal therapy as adjunct | Persistent activity off-cycle | Spironolactone is an option where contraceptives are unsuitable. |
| Moderate-to-severe, failed antibiotics | Adalimumab (biologic) | Inadequate response after a full trial | Screen for latent TB before the first dose. |
| Fixed tracts and scarring (Hurley III) | Surgery + ongoing biologic | New active disease outside excised field | Plan wide excision per region; deroof isolated tracts. |
Systemic Options: A Drug-by-Drug Reference
A reference organized by agent, with the practical cautions that shape day-to-day prescribing. Verify all doses against your local formulary before prescribing.
| Agent | Typical Regimen | Best Suited For | Key Caution |
|---|---|---|---|
| Clindamycin (topical) | 1% solution BID | Localized Hurley I | Limited reach in deeper disease. |
| Clindamycin + rifampicin | 300 mg BID each, 10–12 wk | Moderate, multi-site disease | Rifampicin lowers contraceptive efficacy; GI upset common. |
| Doxycycline | 100 mg BID, up to 12 wk | Alternative systemic antibiotic | Photosensitivity; avoid in pregnancy. |
| Spironolactone | Oral, titrated | Cyclical flares in women | Monitor potassium; avoid in pregnancy. |
| Adalimumab | SC, weekly maintenance after loading | Moderate-to-severe, antibiotic failure | Screen for latent TB and hepatitis first. |
| Secukinumab | SC, scheduled maintenance | TNF-inhibitor failure or intolerance | Caution with active inflammatory bowel disease. |
- Doses are illustrative; confirm against current local prescribing guidance and complete drug monitoring as indicated for each agent.
Monitoring and Follow-Up
Structured follow-up keeps the escalation timeline honest and catches the comorbidities that shadow this disease.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| Treatment response | At the end of each tier’s trial window | Fewer flares, fewer active sites, less pain | Judging a biologic too early before deep disease settles |
| Mood and quality of life | At diagnosis and periodically | Depression, anxiety, social withdrawal | Treating skin while missing the psychological toll |
| Metabolic profile | Periodically | Features of metabolic syndrome | Assuming a young patient is metabolically low-risk |
| Bowel symptoms | At review if symptoms arise | Features suggesting inflammatory bowel disease | Overlooking the recognized HS–IBD association |
Evidence in Context
What the evidence supports, where the major frameworks align, and where genuine uncertainty remains.
Where the US and European Frameworks Agree
Both bodies endorse a severity-led, stepwise structure: lifestyle foundations for all, topical and systemic antibiotics for milder disease, and TNF inhibition for moderate-to-severe disease that fails conventional therapy. They share the principle that surgery addresses the structural disease drugs cannot.
Where Emphasis Differs
The frameworks weight the antibiotic and hormonal options somewhat differently, reflecting regional practice and formulary availability. Treat the specific agent sequence as adaptable, while keeping the underlying escalation logic constant.
Biologics: What the Trials Show
The biologic trial evidence established that TNF inhibition produces a meaningful clinical response in a substantial share of patients with moderate-to-severe disease, and more recent IL-17 pathway trials have broadened the options for those who fail first-line biologic therapy.
The Open Questions
Optimal sequencing of biologics, the best integration of timing between medical and surgical therapy, and durable maintenance strategies remain areas of active study. Much of the antibiotic and surgical evidence rests on observational data rather than large randomized trials.
References
- 1.Alikhan A, Sayed C, Alavi A, et al. North American clinical management guidelines for hidradenitis suppurativa: A publication from the United States and Canadian Hidradenitis Suppurativa Foundations. Part I. J Am Acad Dermatol. 2019;81(1):76–90. doi:10.1016/j.jaad.2019.02.067
- 2.Zouboulis CC, Desai N, Emtestam L, et al. European S1 guideline for the treatment of hidradenitis suppurativa/acne inversa. J Eur Acad Dermatol Venereol. 2015;29(4):619–644. doi:10.1111/jdv.12966
- 3.Kimball AB, Okun MM, Williams DA, et al. Two Phase 3 Trials of Adalimumab for Hidradenitis Suppurativa. N Engl J Med. 2016;375(5):422–434. doi:10.1056/NEJMoa1504370
- 4.Kimball AB, Jemec GBE, Alavi A, et al. Secukinumab in moderate-to-severe hidradenitis suppurativa (SUNSHINE and SUNRISE): week 16 and week 52 results of two identical, multicentre, randomised, placebo-controlled, double-blind phase 3 trials. Lancet. 2023;401(10378):747–761. doi:10.1016/S0140-6736(23)00022-3
How to Read the Evidence Tags
Each recommendation carries two tags for recommendation strength and evidence quality — Medaptly’s own simplified interpretations, not any guideline body’s classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |