
CIDP Diagnosis: 8 Essential Steps to Effective Treatment
Clinical Practice Update — Recognising Chronic Inflammatory Demyelinating Polyradiculoneuropathy and Selecting First-Line Immunotherapy
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Accurate CIDP diagnosis and evidence-based first-line immunotherapy in adults
- Target Audience
- Neurologists, general physicians, neurology residents, advanced practice clinicians
- Setting
- Neurology clinics, general medical outpatients, inpatient neurology
- Source Evidence
- •EAN/PNS Guideline on Diagnosis and Treatment of CIDP (2021, Revised)
- •ICE Trial — IVIG in CIDP (Lancet Neurology, 2008)
- •PATH Trial — Subcutaneous Immunoglobulin Maintenance (Lancet Neurology, 2018)
- •Cochrane Reviews on Corticosteroids and Plasma Exchange in CIDP
Key Clinical Takeaways
Accurate CIDP diagnosis rests on a simple principle: a chronic, symmetric, motor-predominant neuropathy that evolves over at least eight weeks and shows demyelination on nerve conduction studies. Getting the diagnosis right matters because confirmed cases respond well to immunotherapy, while mimics do not. The points below translate the evidence into bedside rules.
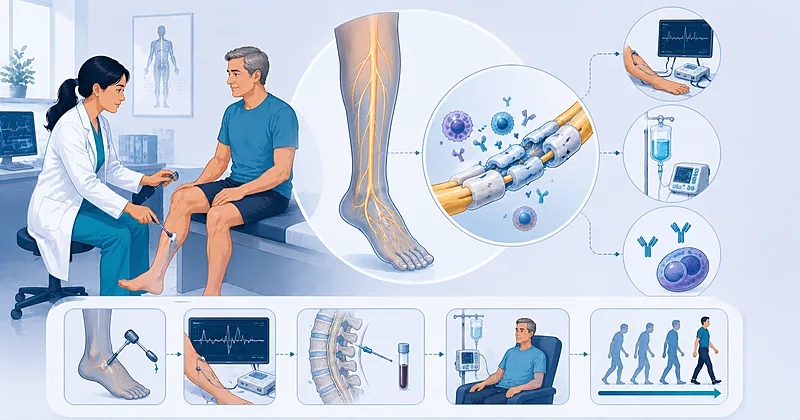
- 1Suspect CIDP in any adult with progressive or relapsing symmetric weakness and sensory loss developing over eight weeks or longer → Recognising the Phenotype
- 2Anchor every CIDP diagnosis in nerve conduction studies — demyelinating features are the cornerstone, not an optional add-on → Electrodiagnosis
- 3Use supportive tests (CSF, imaging, ultrasound) only when electrodiagnosis is borderline — they raise diagnostic confidence but do not replace it → Supportive Testing
- 4Actively screen for mimics before committing — diabetes, paraprotein-associated neuropathy, and hereditary neuropathy are the usual traps → Excluding Mimics
- 5Start treatment with one of three proven first-line options: intravenous immunoglobulin, corticosteroids, or plasma exchange → First-Line Immunotherapy
- 6Match the agent to the patient: immunoglobulin for rapid effect, corticosteroids for cost and durability, plasma exchange when the others fail → Choosing an Agent
- 7Reassess response objectively at the right interval, and taper to the lowest effective maintenance dose once stable → Monitoring Response
- 8Re-examine the CIDP diagnosis in any patient who fails all first-line therapies before escalating to immunosuppressants → When Treatment Fails
CIDP Diagnosis Starts With the Clinical Phenotype
The classic presentation is the gateway to a confident diagnosis. The typical patient develops a roughly symmetric weakness affecting both proximal and distal muscles, accompanied by large-fibre sensory loss, with the timeline being the critical discriminator: progression or relapse over a minimum of eight weeks separates this condition from acute inflammatory neuropathy.
Reflexes are usually reduced or absent throughout, not just at the ankles. Recognising the atypical variants matters just as much, since they account for a substantial minority of cases and are easily missed when clinicians anchor too rigidly on the classic picture.
Evaluate for CIDP when symmetric weakness and sensory loss progress over eight weeks or more, with diffusely reduced or absent reflexes. The eight-week threshold is what distinguishes this from acute inflammatory demyelinating polyneuropathy.
Strong Rec High Evidence EAN/PNS 2021Evaluate for an atypical variant when the picture is purely distal, markedly asymmetric (multifocal), purely motor, or purely sensory. These subtypes are genuine CIDP and respond to the same therapies, but they are frequently overlooked.
Moderate Rec Moderate Evidence EAN/PNS 2021Reassess the diagnosis if prominent pain, autonomic failure, or early respiratory compromise dominate the picture. These features are uncommon in CIDP and should prompt a search for an alternative explanation.
Conditional Rec Low Evidence EAN/PNS 2021Electrodiagnosis: The Core of CIDP Diagnosis
Nerve conduction studies are where a CIDP diagnosis is made or unmade. The goal is to demonstrate demyelination — slowed conduction, prolonged distal latencies, conduction block, temporal dispersion, or delayed late responses — in multiple nerves rather than a single isolated finding.
A thorough study examines several motor nerves bilaterally, because patchy demyelination may be missed if only one or two nerves are tested. Studying proximal segments and including sensory nerves increases the yield, particularly in atypical or early disease.
Perform motor nerve conduction studies in at least four nerves, examining both proximal and distal segments, before confirming the diagnosis. Demonstrating demyelination across multiple nerves is what gives it specificity.
Strong Rec High Evidence EAN/PNS 2021Document conduction block and temporal dispersion when present, as these point strongly toward an acquired demyelinating process rather than a hereditary or axonal one. Their presence helps separate CIDP from look-alike conditions.
Strong Rec Moderate Evidence EAN/PNS 2021Repeat electrodiagnostic testing after several weeks when the first study is equivocal but clinical suspicion remains high. Demyelinating features can become more apparent as the disease evolves.
Moderate Rec Low Evidence EAN/PNS 2021Supportive Testing When Electrodiagnosis Is Borderline
When nerve conduction studies fall short of full criteria, supportive investigations can tip the balance. Cerebrospinal fluid analysis, nerve imaging, and high-resolution ultrasound each add independent information, and they are most valuable precisely when the electrodiagnostic picture is ambiguous.
Consider cerebrospinal fluid analysis to look for raised protein with a normal cell count when electrodiagnosis is borderline. A markedly elevated white cell count argues against CIDP and toward an infective or infiltrative cause.
Moderate Rec Moderate Evidence EAN/PNS 2021Consider nerve root or plexus imaging to detect hypertrophy or gadolinium enhancement in difficult cases. These findings support an inflammatory demyelinating process when the diagnosis is otherwise uncertain.
Conditional Rec Low Evidence EAN/PNS 2021Consider nerve ultrasound to identify enlarged nerve cross-sectional areas at common entrapment-free sites. Diffuse nerve enlargement is increasingly recognised as a useful supportive marker.
Conditional Rec Low Evidence EAN/PNS 2021Do not rely on nerve biopsy as a routine step in CIDP diagnosis. Reserve it for the rare case where vasculitis or infiltration is suspected and less invasive tests have not resolved the question.
Against Moderate Evidence EAN/PNS 2021When electrodiagnosis is suggestive but not definitive, the presence of two or more independent supportive features substantially raises diagnostic confidence: a raised CSF protein with normal cells, nerve enlargement on imaging or ultrasound, and an objective response to a trial of immunotherapy together build a far stronger case than any single finding alone.
Excluding the Mimics Before You Commit
A confident diagnosis is partly a diagnosis of exclusion. Several conditions produce a chronic neuropathy that can look demyelinating, and missing them means committing a patient to prolonged, expensive immunotherapy that will not work. A focused screen for the common mimics belongs in every workup.
Common Mimics and How to Separate Them
| Mimic Condition | What Makes It Look Like CIDP | The Discriminating Test | Practical Tip |
|---|---|---|---|
| Diabetic polyneuropathy | Chronic sensory loss with some conduction slowing | HbA1c; length-dependent axonal pattern | Diabetes and CIDP can coexist — reassess if weakness is disproportionate |
| Paraprotein-associated neuropathy | Demyelinating features on conduction studies | Serum protein electrophoresis with immunofixation | A distal, sensory-predominant course suggests anti-MAG neuropathy |
| Hereditary demyelinating neuropathy | Uniform slowing across all nerves | Family history; foot deformity; genetic testing | Very symmetric, uniform slowing without block points away from CIDP |
| Multifocal motor neuropathy | Asymmetric weakness with conduction block | Pure motor signs; anti-GM1 antibodies | Sensory sparing is the key — it responds to immunoglobulin but not steroids |
| POEMS syndrome | Demyelinating neuropathy with raised CSF protein | VEGF level; lambda paraprotein; systemic features | Look for organomegaly and skin changes that CIDP never causes |
Perform serum protein electrophoresis with immunofixation in every patient before settling on the diagnosis. A paraprotein changes both the diagnosis and the treatment pathway.
Strong Rec Moderate Evidence EAN/PNS 2021Evaluate for hereditary neuropathy when conduction slowing is strikingly uniform across all nerves without block. A family history and skeletal clues such as high arches point toward a genetic cause.
Moderate Rec Low Evidence EAN/PNS 2021First-Line Immunotherapy: Three Proven Options
Once a CIDP diagnosis is secure, three treatments have established efficacy as first-line therapy: intravenous immunoglobulin, corticosteroids, and plasma exchange. All three work; the choice between them turns on speed of effect, side-effect profile, cost, and what your patient values most.
Start intravenous immunoglobulin as a first-line option when a rapid response is needed or steroids are contraindicated. A typical induction is 2 g/kg divided over two to five days, with maintenance infusions guided by response.
Strong Rec High Evidence ICE Trial 2008Prescribe corticosteroids as a first-line option when cost, durability of remission, and oral administration are priorities. Pulsed or daily regimens are both acceptable, with the choice tailored to the patient.
Strong Rec Moderate Evidence Cochrane ReviewPerform plasma exchange as a first-line option when immunoglobulin and steroids are unsuitable or have failed. Its benefit is real but often short-lived, so plan a maintenance strategy from the outset.
Moderate Rec Moderate Evidence Cochrane ReviewConsider subcutaneous immunoglobulin for maintenance in patients who respond to the intravenous form but prefer home administration. It offers comparable control with greater independence.
Moderate Rec High Evidence PATH Trial 2018Do not use first-line immunotherapy indefinitely without attempting a dose reduction once disease is stable. Many patients remain well on less treatment, and some achieve lasting remission off therapy entirely.
Conditional Rec Low Evidence EAN/PNS 2021First-Line Agents Compared by Patient Priority
| Patient Priority | Preferred Agent | Speed of Effect | Main Drawback | Practical Tip |
|---|---|---|---|---|
| Fastest improvement | Intravenous immunoglobulin | Days to a few weeks | High cost; supply constraints | Ensure hydration; screen for IgA deficiency before first dose |
| Lowest cost, oral route | Corticosteroids | Several weeks | Cumulative metabolic and bone toxicity | Add bone and gastric protection; pulsed dosing may limit harm |
| Durable remission | Corticosteroids | Several weeks | Slower onset than immunoglobulin | More patients stay treatment-free after steroid-induced remission |
| Home maintenance | Subcutaneous immunoglobulin | Maintains existing response | Local infusion-site reactions | Best for stable responders who value independence |
| Other options failed | Plasma exchange | Days, but transient | Vascular access; short-lived benefit | Pair with a maintenance agent to hold the gains |
Clinical Decision Pathway
A practical, question-based route from first suspicion to a treatment decision. Work through the questions in order.
Monitoring Response and Follow-Up
Treatment decisions only make sense against an objective baseline. Record a validated measure of strength and disability before starting, then reassess at a sensible interval so improvement — or its absence — can be judged honestly rather than by impression.
| What to Track | When to Reassess | Sign of Genuine Response | Common Pitfall |
|---|---|---|---|
| Disability score | Before treatment, then at each review | Meaningful shift on a validated scale | Relying on the patient’s general sense of being better |
| Grip strength | Each clinic visit | Consistent upward trend across visits | A single reading is noisy — track the trajectory |
| Treatment interval | Once response is established | Stable function on a lengthening interval | Never testing whether less treatment would suffice |
| Steroid safety labs | Periodically while on steroids | Metabolic parameters within range | Forgetting bone and glucose surveillance on long courses |
Document a validated disability and strength measure before the first dose, and repeat it at each review. Without a baseline, neither response nor relapse can be judged reliably.
Strong Rec Moderate Evidence EAN/PNS 2021Reassess and lengthen the treatment interval once the patient is stable, aiming for the lowest effective maintenance. Periodic withdrawal attempts identify those who no longer need ongoing therapy.
Moderate Rec Low Evidence EAN/PNS 2021Evidence in Context
What the trials show, where expert frameworks line up, and where genuine uncertainty remains.
Why Immunoglobulin Became a First-Line Standard
A large randomised trial demonstrated that intravenous immunoglobulin improved disability and reduced relapse over sustained follow-up compared with placebo, establishing it as a durable maintenance option rather than merely a rescue therapy.
Steroids Versus Immunoglobulin: A Real Trade-Off
Head-to-head evidence suggests immunoglobulin acts faster while pulsed corticosteroids may yield more lasting remission once achieved. Neither is universally superior, which is why patient priorities drive the choice.
Subcutaneous Maintenance: The PATH Trial
A randomised study of subcutaneous immunoglobulin for maintenance showed it reduced relapse compared with placebo, validating a home-based route for patients already responsive to the intravenous form.
The Limits of Second-Line Evidence
Evidence for immunosuppressants and newer agents in refractory disease remains thinner than for the three first-line options. This is the strongest argument for re-examining a CIDP diagnosis before escalating beyond first-line therapy.
References
- 1.Van den Bergh PYK, van Doorn PA, Hadden RDM, et al. European Academy of Neurology/Peripheral Nerve Society guideline on diagnosis and treatment of chronic inflammatory demyelinating polyradiculoneuropathy: report of a joint Task Force—Second revision. J Peripher Nerv Syst. 2021;26(3):242–268. doi:10.1111/jns.12455
- 2.Hughes RAC, Donofrio P, Bril V, et al. Intravenous immune globulin (10% caprylate-chromatography purified) for the treatment of chronic inflammatory demyelinating polyradiculoneuropathy (ICE study): a randomised placebo-controlled trial. Lancet Neurol. 2008;7(2):136–144. doi:10.1016/S1474-4422(07)70329-0
- 3.van Schaik IN, Bril V, van Geloven N, et al. Subcutaneous immunoglobulin for maintenance treatment in chronic inflammatory demyelinating polyneuropathy (PATH): a randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Neurol. 2018;17(1):35–46. doi:10.1016/S1474-4422(17)30378-2
- 4.Hughes RAC, Mehndiratta MM, Rajabally YA. Corticosteroids for chronic inflammatory demyelinating polyradiculoneuropathy. Cochrane Database Syst Rev. 2017;11(11):CD002062. doi:10.1002/14651858.CD002062.pub4
- 5.Mehndiratta MM, Hughes RAC, Pritchard J. Plasma exchange for chronic inflammatory demyelinating polyradiculoneuropathy. Cochrane Database Syst Rev. 2015;(8):CD003906. doi:10.1002/14651858.CD003906.pub4
How to Read the Evidence Tags
Every recommendation carries two tags — one for recommendation strength and one for evidence quality. These are Medaptly’s own simplified interpretations, not any guideline body’s classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise the decision. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |