
Normal Pressure Hydrocephalus: 7 Critical Diagnosis Rules
Clinical Practice Update — Recognition, Diagnostic Confirmation, and Shunt Selection in Older Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Recognising, confirming, and selecting surgical candidates in normal pressure hydrocephalus diagnosis
- Target Audience
- Neurologists, geriatricians, neurosurgeons, primary care physicians, residents
- Setting
- Outpatient neurology, memory clinics, neurosurgical referral
- Source Evidence
- •International NPH Guidelines, 3rd Edition (Nakajima et al., 2021)
- •European iNPH Multicentre Study (Klinge et al., 2012)
- •SVASONA Trial — Adjustable vs Fixed Shunt Valves (Lemcke et al., 2013)
- •AESOP Pilot Trial — Endoscopic Third Ventriculostomy in iNPH (2018)
Key Clinical Takeaways
Accurate normal pressure hydrocephalus diagnosis rests on three steps that are easy to state but hard to get right: recognise the clinical pattern, demonstrate that cerebrospinal fluid removal improves it, and select patients whose ventricular enlargement is genuinely driving their symptoms. The points below distil the evidence into rules you can apply when an older adult presents with gait failure and cognitive decline.
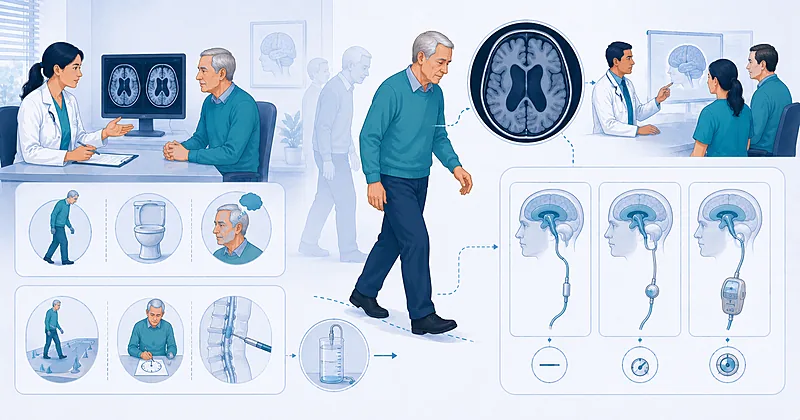
- 1Lead with the gait. A magnetic, broad-based, shuffling gait is the earliest and most shunt-responsive feature — begin every gait assessment here.
- 2Do not require the full triad. Many patients present with gait and cognitive change before urinary symptoms appear.
- 3Confirm ventriculomegaly objectively with an Evans index above 0.3, then look for the disproportionate subarachnoid space pattern on MRI.
- 4Use the CSF tap test to predict shunt response — a clear gait improvement after large-volume drainage is the strongest practical predictor.
- 5A negative tap test does not exclude a shunt-responsive patient — consider extended lumbar drainage when suspicion remains high.
- 6Choose a programmable valve as the default for ventriculoperitoneal shunting so the opening pressure can be adjusted non-invasively.
- 7Counsel realistically: gait recovers most reliably, cognition partially, and benefit is greatest when symptom duration is short.
Recognising the Clinical Pattern in Normal Pressure Hydrocephalus Diagnosis
The classic description pairs gait disturbance, cognitive slowing, and urinary urgency, but treating these as a checklist that must be fully present delays recognition. Gait change almost always comes first, and it is the feature most likely to reverse after treatment. The cognitive component is typically a subcortical, frontal-executive slowing rather than the amnestic profile seen in Alzheimer disease.
Evaluate gait first in any older adult with unexplained walking difficulty and ventriculomegaly. Time a 10-metre walk and count steps on turning — a wide base and turning hesitation point strongly toward this condition.
Strong Rec Moderate Evidence Intl NPH 2021Perform structured cognitive screening focused on processing speed, attention, and executive function rather than memory alone. A frontal-subcortical profile supports the diagnosis and distinguishes it from primary neurodegenerative dementia.
Moderate Rec Moderate Evidence Intl NPH 2021Ask specifically about urinary urgency and frequency, which patients often underreport. Established incontinence usually appears later and signals more advanced disease.
Conditional Rec Low Evidence Intl NPH 2021The Role of Imaging in Normal Pressure Hydrocephalus Diagnosis
Imaging serves two purposes: confirming that the ventricles are genuinely enlarged out of proportion to atrophy, and identifying features that raise or lower the probability of shunt response. Ventricular size alone is not enough, because age-related atrophy also widens the ventricles. The pattern of cerebrospinal fluid distribution carries more weight than the raw measurement.
Measure the Evans index on axial imaging and treat a value above 0.3 as the threshold for ventriculomegaly. Document this objectively rather than relying on a visual impression of “big ventricles”.
Strong Rec High Evidence Intl NPH 2021Obtain MRI to look for the disproportionately enlarged subarachnoid-space pattern — tight high-convexity sulci with widened Sylvian fissures. Its presence substantially raises the probability of a favourable surgical outcome.
Moderate Rec Moderate Evidence Intl NPH 2021Review imaging for vascular burden and medial temporal atrophy. Heavy small-vessel disease or marked hippocampal atrophy suggests a co-existing or alternative cause and tempers the expected benefit.
Conditional Rec Moderate Evidence European iNPH 2012Imaging Features by Diagnostic Weight
| Imaging Feature | What It Suggests | Effect on Shunt Odds | Practical Tip |
|---|---|---|---|
| Evans index > 0.3 | Ventriculomegaly confirmed | Required, not sufficient | Measure at the widest frontal horns on the same slice |
| Tight high convexity | Disproportionate CSF distribution | Raises favourable odds | Look on coronal images at the vertex |
| Widened Sylvian fissures | Part of the DESH pattern | Raises favourable odds | Contrast with the tight sulci above |
| Callosal angle < 90° | Supports the diagnosis | Raises favourable odds | Measure on a coronal slice at the posterior commissure |
| Severe white-matter disease | Competing vascular cause | Lowers favourable odds | Does not exclude benefit; weigh with the tap test |
Confirming the Diagnosis with CSF Dynamics
Because no single clinical or imaging feature is decisive, supplementary tests that remove cerebrospinal fluid and measure the response form the practical core of patient selection. The aim is to predict, before committing to surgery, whether diverting fluid will help. Gait is the cleanest outcome to measure because it can be timed and compared objectively before and after drainage.
Perform a CSF tap test by removing 30–50 mL of fluid and re-timing gait at several hours and again the next day. A clear, measured improvement is the most useful positive predictor of shunt benefit available in routine practice.
Strong Rec High Evidence Intl NPH 2021Evaluate for extended lumbar drainage when the tap test is negative or equivocal but clinical suspicion stays high. Draining fluid over two to three days improves sensitivity and identifies responders the single tap test misses.
Moderate Rec Moderate Evidence European iNPH 2012Do not withhold referral for surgical assessment solely because of advanced age. Selection should rest on response to fluid removal and overall fitness, not on a chronological cut-off.
Against Moderate Evidence Intl NPH 2021The single tap test is quick and specific but misses some responders. Extended drainage is more sensitive but needs admission and carries a small infection risk. Infusion testing of cerebrospinal fluid outflow resistance is available in some centres and adds predictive information where drainage results are borderline.
Clinical Decision Pathway
A practical, question-based route from first presentation to a shunt decision. Work through the questions in order.
Selecting the Right Shunt and Valve
Once a patient is confirmed as shunt-responsive, the choice of hardware shapes both benefit and risk. Ventriculoperitoneal diversion is the standard approach. The valve decision matters most, because the ability to adjust opening pressure after surgery lets the team chase symptom relief while limiting overdrainage.
Prescribe a programmable valve as the default for ventriculoperitoneal shunting. Non-invasive pressure adjustment reduces reoperation for overdrainage and lets the team titrate to the best symptom response.
Strong Rec High Evidence SVASONA 2013Add a gravitational or anti-siphon component to limit posture-related overdrainage. This pairing lowers the rate of subdural collections without sacrificing symptom improvement.
Moderate Rec Moderate Evidence SVASONA 2013Start with a higher opening pressure and step it down gradually over follow-up visits. Cautious lowering captures benefit while keeping overdrainage and subdural haematoma risk in check.
Moderate Rec Low Evidence Intl NPH 2021Consider endoscopic third ventriculostomy only in carefully selected cases with obstructive features, and counsel that evidence for the idiopathic form is far weaker than for shunting.
Conditional Rec Low Evidence AESOP 2018Matching the Procedure to the Patient
| Patient Profile | Preferred Approach | Valve Strategy | Watch For |
|---|---|---|---|
| Typical idiopathic, tap-positive | Ventriculoperitoneal shunt | Programmable plus anti-siphon | Overdrainage on early mobilisation |
| Frail, higher bleeding risk | Ventriculoperitoneal shunt | Higher start pressure, slow titration | Subdural collections; review anticoagulation |
| Obstructive features present | Discuss third ventriculostomy | Not applicable | Weaker evidence in idiopathic disease |
| Prior abdominal surgery | Consider ventriculoatrial route | Programmable where feasible | Line-related and cardiac complications |
Monitoring and Follow-Up
Post-operative care is an active process of titration, not a single review. The same objective measures used during diagnosis should track recovery, and valve settings often need refinement over the first months.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| Timed gait | Pre-op, then each review | Faster walk, fewer steps on turning | Relying on patient recall instead of a measured time |
| Valve setting | Weeks 4–12, then as needed | Room to lower pressure if gait plateaus | Confirm the setting after any MRI exposure |
| Cognition | Pre-op and 3–6 months | Improved attention and processing speed | Expecting amnestic deficits to reverse |
| Imaging | If symptoms change abruptly | Subdural collection or slit ventricles | Attributing all decline to disease progression |
Evidence in Context
What the evidence supports, where the major sources align, and where genuine uncertainty remains.
Where the Major Sources Agree
Across the international and European bodies there is consistent agreement that gait disturbance is the cardinal feature, that a response to fluid removal is central to selection, and that shunting offers meaningful benefit to well-selected patients.
Where Approaches Differ
Selection testing: some centres rely on the single tap test as the gatekeeper, while others move quickly to extended drainage or infusion studies. The thresholds for calling a test positive also vary between groups.
Adjustable Valves: What the SVASONA Trial Shows
Randomised data comparing adjustable and fixed valves found fewer overdrainage complications with adjustable hardware, which underpins the current preference for programmable valves in this population.
The Durability Question
Short-term gait improvement is well established, but how long benefit persists, and how much co-existing neurodegeneration erodes it over years, remains an area of active study and honest uncertainty.
References
- 1.Nakajima M, Yamada S, Miyajima M, et al. Guidelines for Management of Idiopathic Normal Pressure Hydrocephalus (Third Edition). Neurol Med Chir (Tokyo). 2021;61(2):63–97. doi:10.2176/nmc.st.2020-0292
- 2.Klinge P, Hellström P, Tans J, Wikkelsø C. One-year outcome in the European multicentre study on iNPH. Acta Neurol Scand. 2012;126(3):145–153. doi:10.1111/j.1600-0404.2012.01676.x
- 3.Lemcke J, Meier U, Müller C, et al. Safety and efficacy of gravitational shunt valves in patients with iNPH: the SVASONA trial. J Neurol Neurosurg Psychiatry. 2013;84(8):850–857. doi:10.1136/jnnp-2012-303936
- 4.Halperin JJ, Kurlan R, Schwalb JM, et al. Practice guideline: idiopathic normal pressure hydrocephalus. Neurology. 2015;85(23):2063–2071. doi:10.1212/WNL.0000000000002193
How to Read the Evidence Tags
Every recommendation carries two tags for recommendation strength and evidence quality — Medaptly’s own simplified interpretations, not a reproduction of any guideline body’s grading system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |