
Wernicke Encephalopathy Diagnosis and Thiamine Repletion
Clinical Practice Update — Recognition, Empiric Thiamine, and Preventing Irreversible Harm
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Recognition and thiamine repletion in suspected Wernicke encephalopathy
- Target Audience
- Emergency physicians, internists, neurologists, hospitalists, pharmacists
- Setting
- Emergency departments, acute medical units, inpatient wards
- Source Evidence
- •EFNS Guideline on Wernicke Encephalopathy (Eur J Neurol, 2010)
- •RCP London / NICE Guidance on Alcohol-Use Disorders (CG100, 2010)
- •Caine Operational Criteria for Wernicke Encephalopathy (J Neurol Neurosurg Psychiatry, 1997)
- •Cochrane Review — Thiamine for Wernicke-Korsakoff Syndrome (2013)
Key Clinical Takeaways
Effective Wernicke encephalopathy diagnosis rests on a single uncomfortable truth: the classic triad appears in only a minority of patients, so waiting for it costs brains. Treat any at-risk patient with even one suggestive feature as having the condition until proven otherwise, and give parenteral thiamine before laboratory confirmation. The points below distil the evidence into rules you can apply at the bedside.
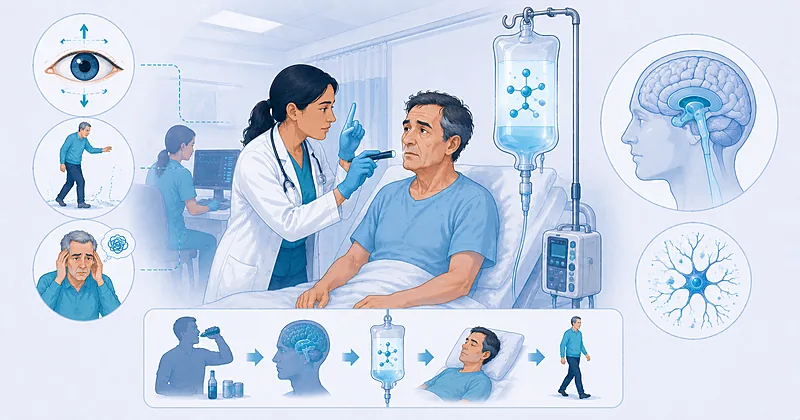
- 1Do not wait for the classic triad of confusion, ophthalmoplegia, and ataxia — all three are present in fewer than one in five patients at presentation.
- 2Use the Caine criteria: any two of dietary deficiency, eye signs, cerebellar signs, or altered mentation should trigger treatment.
- 3Give thiamine intravenously, not orally — oral absorption is unreliable and insufficient in an acute deficiency state.
- 4Always administer thiamine before any glucose load in malnourished patients to avoid precipitating or worsening the encephalopathy.
- 5Look beyond alcohol — bariatric surgery, hyperemesis, malignancy, and prolonged vomiting are major non-alcoholic causes.
- 6Normal blood thiamine and normal MRI do not exclude the diagnosis — treatment is clinical, not laboratory-gated.
- 7Co-administer magnesium — it is a cofactor for thiamine-dependent enzymes, and hypomagnesaemia blunts the response.
- 8Treat for the full course — under-dosing leaves patients at risk of irreversible Korsakoff amnesia.
Who Is at Risk and When to Suspect It
The first barrier to timely Wernicke encephalopathy diagnosis is failure to consider it. Any patient with a state of chronic or acute nutritional depletion who develops new neurological or cognitive changes belongs in the differential, regardless of whether alcohol is part of the history.
Evaluate for thiamine deficiency in every patient with chronic alcohol use who presents with confusion, a fall, or unexplained neurological signs — this remains the single most common context.
Strong Rec Moderate Evidence EFNS 2010Consider Wernicke encephalopathy in non-alcoholic patients after bariatric surgery, with hyperemesis gravidarum, on chemotherapy, with advanced malignancy, or following any prolonged period of poor intake or vomiting.
Moderate Rec Low Evidence EFNS 2010Reassess any malnourished inpatient who deteriorates neurologically after receiving intravenous dextrose or parenteral nutrition without prior thiamine cover.
Strong Rec Moderate Evidence RCP/NICE 2010Clinical Features in Wernicke Encephalopathy Diagnosis
Accurate Wernicke encephalopathy diagnosis depends on recognising that the presentation is usually partial. Most patients show one or two features, not the full picture, and the mental-state change is frequently the only clue.
Document a focused neurological examination covering eye movements, gait, and cognition in every at-risk patient, because the absence of one domain does not exclude the diagnosis.
Strong Rec Moderate Evidence Caine 1997Do not use a normal MRI to rule out the condition. Imaging may show symmetrical signal change around the third ventricle and mammillary bodies, but a normal scan is common and does not change management.
Against Moderate Evidence EFNS 2010Thiamine Repletion After Wernicke Encephalopathy Diagnosis
Once Wernicke encephalopathy diagnosis is suspected, repletion is urgent and parenteral. The optimal regimen is debated because high-quality trial data are scarce, but the principle is consistent: give generously, give early, and give by vein.
Start intravenous thiamine 500 mg three times daily for treatment of established or strongly suspected Wernicke encephalopathy, infused over 30 minutes, continued for 2–3 days.
Strong Rec Low Evidence EFNS 2010Step down to intravenous thiamine 250 mg once daily after the initial high-dose phase, continuing until clinical improvement plateaus or for at least 5 days.
Moderate Rec Low Evidence RCP/NICE 2010Administer thiamine before any intravenous glucose, and watch for refeeding syndrome when nutrition is reintroduced in a severely malnourished patient.
Strong Rec Moderate Evidence RCP/NICE 2010Correct hypomagnesaemia alongside thiamine, since magnesium is an essential cofactor and its deficiency can render repletion ineffective.
Moderate Rec Low Evidence EFNS 2010Transition to oral thiamine only once the acute phase has resolved and gut absorption is reliable, continuing while the underlying risk persists.
Moderate Rec Low Evidence RCP/NICE 2010Thiamine Dosing by Clinical Situation
| Clinical Situation | Route & Dose | Duration | Practical Tips |
|---|---|---|---|
| Established Wernicke encephalopathy | IV 500 mg three times daily | 2–3 days, then reassess | Infuse over 30 min in 100 mL saline; reduces infusion reactions. |
| Step-down after improvement | IV 250 mg once daily | At least 5 days total | Continue while neurological signs are still resolving. |
| At-risk, no overt signs (prophylaxis) | IV/IM 100–200 mg daily | 3–5 days | Use during alcohol withdrawal admissions before any dextrose. |
| Maintenance after acute phase | Oral 100 mg once daily | While risk persists | Pair with dietary counselling and follow-up. |
Doses reflect commonly cited regimens; verify against local formulary and the source guidelines before prescribing. Exact optimal dosing remains uncertain due to limited trial evidence.
Clinical Decision Pathway
A practical, question-based approach to the at-risk patient with possible Wernicke encephalopathy. Work through the questions in order.
Monitoring and Follow-Up
Response to thiamine is itself diagnostic information. Track the neurological domains that change fastest and watch for the transition to a chronic amnestic state.
| What to Track | When | Expected Trajectory | Common Pitfalls |
|---|---|---|---|
| Eye signs | Hours to first day | Often the first to improve | Stopping therapy early because eyes recovered while confusion persists. |
| Mental state | Daily over several days | Slower, may take days to weeks | Mistaking residual confusion for fixed dementia too soon. |
| Gait and ataxia | Daily, then at discharge | Partial recovery common | Discharging before fall risk is reassessed. |
| Memory (for Korsakoff syndrome) | Late, before discharge | May persist if treatment delayed | Failing to arrange cognitive follow-up after discharge. |
Evidence in Context
What the evidence supports, where the guidance is firm, and where genuine uncertainty remains.
Why the Diagnostic Threshold Is Deliberately Low
Autopsy studies have repeatedly shown that the condition is identified far less often during life than at post-mortem, meaning under-diagnosis is the dominant failure mode. Because thiamine is cheap and safe, the risk calculus strongly favours treating on suspicion rather than waiting for certainty.
How Strong Is the Evidence on Dosing?
A Cochrane review found insufficient randomised evidence to define a single optimal dose, frequency, or duration. Current high-dose parenteral regimens rest largely on pharmacological reasoning and expert consensus rather than head-to-head trials, which is why most dosing recommendations carry a low evidence grade.
The Glucose-Before-Thiamine Caution
Carbohydrate load increases the demand for thiamine as a metabolic cofactor, so giving glucose to an already-deficient patient can tip them into overt encephalopathy. In practice, the two are given together when needed; the rule is simply never to give glucose alone first.
Where Alcohol-Focused and Nutritional Guidance Differ
Alcohol-focused guidance frames thiamine largely around withdrawal admissions, while neurological guidance emphasises the wider non-alcoholic population. The practical reconciliation is to decouple thiamine from the alcohol label entirely and treat on nutritional risk plus neurological features.
References
- 1.Galvin R, Bråthen G, Ivashynka A, et al. EFNS guidelines for diagnosis, therapy and prevention of Wernicke encephalopathy. Eur J Neurol. 2010;17(12):1408–1418. doi:10.1111/j.1468-1331.2010.03153.x
- 2.Caine D, Halliday GM, Kril JJ, Harper CG. Operational criteria for the classification of chronic alcoholics: identification of Wernicke’s encephalopathy. J Neurol Neurosurg Psychiatry. 1997;62(1):51–60. doi:10.1136/jnnp.62.1.51
- 3.Day E, Bentham PW, Callaghan R, Kuruvilla T, George S. Thiamine for prevention and treatment of Wernicke-Korsakoff Syndrome in people who abuse alcohol. Cochrane Database Syst Rev. 2013;(7):CD004033. doi:10.1002/14651858.CD004033.pub3
- 4.National Institute for Health and Care Excellence. Alcohol-use disorders: diagnosis and management of physical complications (CG100). 2010. nice.org.uk/guidance/cg100
How to Read the Evidence Tags
Every recommendation carries tags for recommendation strength and evidence quality — Medaptly’s own simplified interpretations, not reproductions of any guideline body’s classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence or compelling safety logic broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise to the patient. |
| Against | Evidence shows no benefit or potential harm from this approach. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus, pharmacological reasoning, or small studies. |