
After Gestational Diabetes: Postpartum Screening and Prevention
Clinical Practice Update — Postpartum Screening, Risk Stratification, and Type 2 Diabetes Prevention
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Postpartum screening and long-term diabetes prevention after gestational diabetes
- Target Audience
- Obstetricians, family physicians, midwives, endocrinologists, primary care nurses
- Setting
- Postnatal clinics, primary care, women’s health services
- Source Evidence
- •ADA Standards of Care in Diabetes (2025)
- •ACOG Practice Bulletin 190 — Gestational Diabetes Mellitus (2018)
- •NICE NG3 — Diabetes in Pregnancy (2015, updated 2020)
- •Diabetes Prevention Program Outcomes Study (DPPOS, 2015)
- •USPSTF Recommendation — Screening for Gestational Diabetes (2021)
Key Clinical Takeaways
Effective gestational diabetes postpartum care turns a pregnancy complication into a lifelong prevention opportunity. A woman who had gestational diabetes carries a markedly elevated lifetime risk of type 2 diabetes, yet the postnatal screening that would catch it early is one of the most frequently missed steps in women’s health. The points below distill the evidence into actions you can deliver from the postnatal visit onward.
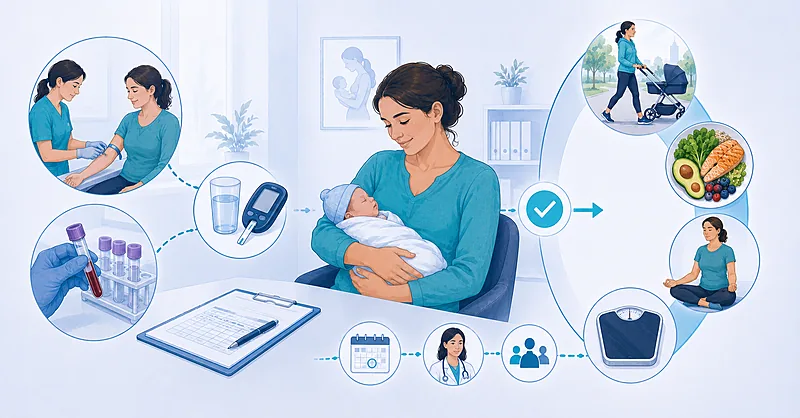
- 1Order a 75 g oral glucose tolerance test at 4 to 12 weeks postpartum for every woman who had gestational diabetes, not a fasting glucose or HbA1c alone → The Screening Window
- 2If the early test is normal, repeat glucose testing every 1 to 3 years for life — the risk never returns to baseline → Lifelong Surveillance
- 3Around one in two women with prior gestational diabetes develops type 2 diabetes within a decade or two of the index pregnancy → Quantifying the Risk
- 4Encourage breastfeeding — it is associated with lower maternal glucose and a reduced rate of progression to diabetes → Lifestyle Prevention
- 5Offer a structured lifestyle programme; intensive diet and activity cut progression to diabetes by more than half in high-risk women → Lifestyle Prevention
- 6Consider metformin for women with persistent prediabetes after delivery, particularly those under 60 with a high BMI → When to Add Medication
- 7Discuss pre-pregnancy glucose testing before any future pregnancy to detect interval diabetes → Future Pregnancy
- 8Build a transfer-of-care handoff so the result and the recall plan reach the woman’s primary care record → Closing the Loop
The Gestational Diabetes Postpartum Screening Window
The single most important action in gestational diabetes postpartum screening is the early oral glucose tolerance test. The placental hormones that drive insulin resistance clear within days of delivery, so glucose tolerance in the first weeks postpartum reflects the woman’s true underlying physiology rather than the pregnancy state.
Major guidelines converge on a 75 g two-hour test performed between 4 and 12 weeks after birth. A fasting plasma glucose or HbA1c alone will miss a meaningful share of women whose abnormality only declares itself on the post-load value.
Perform a 75 g two-hour oral glucose tolerance test at 4 to 12 weeks postpartum for every woman whose pregnancy was complicated by gestational diabetes. This is the reference test for gestational diabetes postpartum screening and outperforms fasting glucose or HbA1c used alone.
Strong Rec High Evidence ADA 2025 ACOG 2018Interpret the result against standard non-pregnant thresholds. A normal test is reassuring for now; an impaired fasting glucose or impaired glucose tolerance result places the woman in the prediabetes range and changes her follow-up intensity.
Strong Rec High Evidence ADA 2025Counsel patients on attending the test before they leave the maternity service. Booking the appointment at discharge, rather than relying on a later letter, is the most effective lever for raising the dismal real-world completion rate.
Moderate Rec Moderate Evidence NICE NG3Quantifying the Long-Term Risk
A history of gestational diabetes is one of the strongest single predictors of future type 2 diabetes that a clinician will encounter in routine practice. Framing this risk concretely, and without alarm, helps a new mother understand why the follow-up matters.
The gap between the magnitude of the risk and the rate at which screening is actually completed is the central problem this update addresses. Identifying the women at highest residual risk lets you concentrate effort where it changes outcomes.
Evaluate for higher residual risk in women who needed insulin during pregnancy, were diagnosed before 24 weeks, had a markedly elevated diagnostic glucose, or carry a high BMI. Early insulin use in particular flags a woman who warrants closer surveillance.
Moderate Rec Moderate Evidence ADA 2025Document the gestational diabetes diagnosis prominently in the woman’s long-term medical record, flagged as an ongoing cardiometabolic risk factor rather than a resolved pregnancy event.
Strong Rec Low Evidence ACOG 2018Gestational Diabetes Postpartum Screening Beyond the First Test
A normal test at 6 weeks is a snapshot, not a discharge. Because risk accrues over years, gestational diabetes postpartum screening is properly understood as a lifelong surveillance commitment that transitions from the maternity service into primary care.
Reassess glucose status at least every 1 to 3 years for life when the early test is normal. An annual HbA1c or fasting glucose in primary care is a practical default, intensifying to yearly testing for women with additional risk factors.
Strong Rec Moderate Evidence ADA 2025Reassess for women who screen in the prediabetes range more often — yearly at minimum. This group has the steepest trajectory toward overt diabetes and the most to gain from early intervention.
Strong Rec Moderate Evidence ADA 2025Ensure the early test result and the long-term recall plan are transferred to the woman’s primary care record before the maternity episode closes. A result that never reaches the GP cannot trigger future testing.
Moderate Rec Low Evidence NICE NG3Lifestyle Prevention and Breastfeeding
Screening identifies risk; prevention is what alters the trajectory. The strongest evidence for delaying or averting type 2 diabetes in this population comes from structured lifestyle intervention, with breastfeeding adding a meaningful and low-cost protective effect.
Refer to or deliver a structured lifestyle programme targeting modest sustained weight loss and regular physical activity. In high-risk adults this approach reduces progression to diabetes by more than half over several years.
Strong Rec High Evidence DPPOS 2015Advise breastfeeding and support its continuation. Lactation is associated with lower maternal glucose, improved insulin sensitivity, and a reduced rate of later diabetes, with longer duration conferring greater benefit.
Moderate Rec Moderate Evidence ADA 2025Counsel patients on a realistic activity target built around the demands of caring for a newborn — short, frequent bouts of movement are more sustainable than an idealised gym schedule in the early postpartum months.
Moderate Rec Low Evidence DPPOS 2015When to Add Pharmacological Prevention
For most women, lifestyle change is the first and sufficient step. A subset with persistent prediabetes after delivery benefit from adding metformin, which delays progression to diabetes and is compatible with breastfeeding.
Consider metformin therapy for women with persistent prediabetes despite lifestyle measures, especially those who are younger, have a higher BMI, or had a more severe glucose abnormality in pregnancy. Benefit is greatest in exactly the profile common after gestational diabetes.
Conditional Rec High Evidence ADA 2025 DPPOS 2015Counsel patients that metformin complements rather than replaces lifestyle change. Across prevention trials, intensive lifestyle modification has outperformed medication, so the drug is an addition to diet and activity, not a substitute.
Moderate Rec High Evidence DPPOS 2015Do not delay a needed diabetes diagnosis on the assumption that postpartum hyperglycaemia is residual pregnancy effect. If the early test meets diabetes thresholds, treat it as type 2 diabetes and manage accordingly.
Strong Rec Moderate Evidence ADA 2025Clinical Decision Pathway
A practical, question-based approach to the postnatal visit after a pregnancy complicated by gestational diabetes. Work through the questions in order.
Practical Reference Tables
Two reference tables to keep at the postnatal visit: a test-selection guide framed by the clinical question you are answering, and a recall schedule organised by the woman’s risk profile.
Choosing the Right Test by Clinical Question
| Clinical Question | Preferred Test | Timing | Why This Choice |
|---|---|---|---|
| Has glucose normalised after delivery? | 75 g two-hour OGTT | 4–12 weeks postpartum | Captures post-load abnormality a fasting test alone would miss |
| Routine long-term surveillance? | HbA1c or fasting glucose | Every 1–3 years for life | Convenient, no fasting needed for HbA1c, suits primary care recall |
| Planning another pregnancy? | Fasting glucose or HbA1c pre-conception | Before conception | Detects interval diabetes that would change early pregnancy care |
| Prediabetes already confirmed? | HbA1c or fasting glucose | Yearly | Steepest progression risk warrants the tightest interval |
Recall Schedule by Risk Profile
| Risk Profile | Early Test Result | Recall Interval | Prevention Priority | Watch For |
|---|---|---|---|---|
| Standard | Normal | Every 1–3 years | Lifestyle, breastfeeding support | Weight regain, new pregnancy |
| Higher residual | Normal but insulin-treated or early diagnosis | Yearly | Structured programme referral | Rising fasting glucose |
| Prediabetes | Impaired fasting glucose or impaired tolerance | Yearly, minimum | Intensive lifestyle ± metformin | Progression to diabetes range |
| Diabetes | Meets diabetes thresholds | Per diabetes care pathway | Full type 2 diabetes management | Complication screening |
Monitoring and Follow-Up
Beyond glucose, a woman with prior gestational diabetes carries a broader cardiometabolic risk profile that rewards periodic attention.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| Glucose status | 4–12 weeks, then every 1–3 years | Shift toward prediabetes or diabetes range | Relying on fasting glucose alone for the early test |
| Weight / BMI | Each clinical contact | Retained pregnancy weight or interval gain | Treating weight as cosmetic rather than metabolic |
| Blood pressure | Periodically | Emerging hypertension | Overlooking it after the obstetric episode ends |
| Lipid profile | As part of cardiometabolic review | Dyslipidaemia adding to overall risk | Checking glucose but ignoring the wider picture |
Evidence in Context
What the evidence shows, where the major frameworks agree, and where their emphasis differs.
Where the Major Frameworks Agree
ADA, ACOG, and NICE align on the essentials: an early postpartum oral glucose tolerance test, indefinite long-term surveillance, and lifestyle modification as the foundation of prevention. The disagreements are about cadence and emphasis, not direction.
Where Emphasis Differs
Long-term test of choice: some frameworks lean on HbA1c for convenience in ongoing surveillance, while others retain a preference for glucose-based testing. For the early postpartum test, the 75 g OGTT remains the shared reference standard because HbA1c can be unreliable in the weeks after delivery.
Lifestyle Prevention: What the Trials Show
Landmark prevention research, including long-term follow-up of the Diabetes Prevention Program, demonstrated that intensive lifestyle intervention substantially lowered progression to diabetes in high-risk adults, and that women with a gestational diabetes history were among those who benefited. Metformin also reduced risk but to a lesser degree than lifestyle change.
The Implementation Gap
The recurring finding across health systems is that recommended postpartum testing is completed by a minority of eligible women. The evidence base for what to do is mature; the unsolved problem is reliably delivering it, which is why the handoff to primary care and booking before discharge carry such weight in practice.
References
- 1.American Diabetes Association Professional Practice Committee. Management of Diabetes in Pregnancy: Standards of Care in Diabetes—2025. Diabetes Care. 2025;48(Suppl 1):S306–S320. doi:10.2337/dc25-S015
- 2.ACOG Practice Bulletin No. 190: Gestational Diabetes Mellitus. Obstet Gynecol. 2018;131(2):e49–e64. doi:10.1097/AOG.0000000000002501
- 3.Diabetes Prevention Program Research Group. Long-term effects of lifestyle intervention or metformin on diabetes development and microvascular complications (DPPOS). Lancet Diabetes Endocrinol. 2015;3(11):866–875. doi:10.1016/S2213-8587(15)00291-0
- 4.US Preventive Services Task Force. Screening for Gestational Diabetes: US Preventive Services Task Force Recommendation Statement. JAMA. 2021;326(6):531–538. doi:10.1001/jama.2021.11922
- 5.National Institute for Health and Care Excellence. Diabetes in pregnancy: management from preconception to the postnatal period (NG3). 2015, updated 2020. nice.org.uk/guidance/ng3
How to Read the Evidence Tags
Each recommendation carries a strength tag and an evidence-quality tag — Medaptly’s own simplified interpretation, not a reproduction of any guideline body’s classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |