
Acute Gastroenteritis in Children: Dehydration Scoring and Rehydration
Clinical Practice Update — Pediatric Dehydration Assessment and Oral Rehydration in Acute Gastroenteritis
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Pediatric dehydration assessment and fluid replacement in acute gastroenteritis
- Target Audience
- Pediatricians, family physicians, emergency physicians, nurses, pharmacists
- Setting
- Primary care, urgent care, emergency departments, pediatric wards
- Source Evidence
- •NICE NG84 — Diarrhoea and Vomiting in Children Under 5 (2009, updated)
- •WHO/UNICEF — Clinical Management of Acute Diarrhoea and Low-Osmolarity ORS
- •ESPGHAN/ESPID — Management of Acute Gastroenteritis in Children (2014)
- •AAP/CDC — Oral Rehydration Therapy and Management of Acute Diarrhea
Key Clinical Takeaways
Effective pediatric dehydration assessment turns three quick judgements into a treatment plan: estimate the fluid deficit clinically, decide whether the child can be rehydrated by mouth, and choose the right volume and route. The points below distill current evidence into rules you can apply at the cot-side.
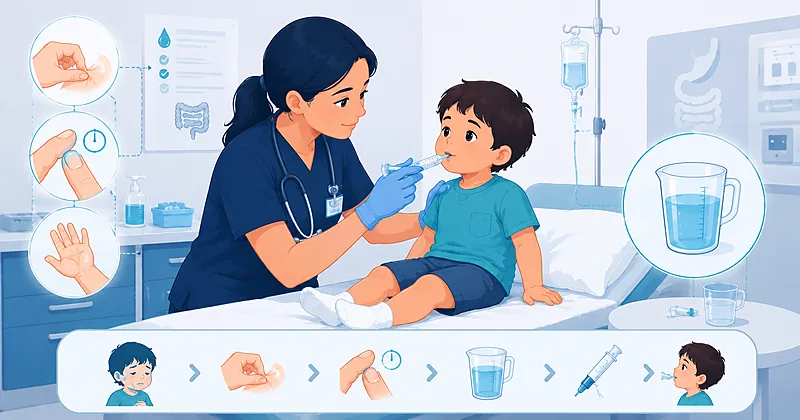
- 1Base every pediatric dehydration assessment on a combination of clinical signs using a clinical dehydration scale, not on any single physical finding → Assessing Severity
- 2Treat low-osmolarity oral rehydration solution as the first-line therapy for mild and moderate fluid loss → Oral Rehydration
- 3Replace an estimated deficit of 50–100 mL/kg by mouth over 3–4 hours in children who are not shocked → Fluid Volumes
- 4Offer ORS in small, frequent amounts — a syringe or teaspoon every few minutes succeeds where a full cup fails → Oral Rehydration
- 5Consider a single dose of oral ondansetron to enable oral rehydration in children with vomiting who are otherwise candidates for ORS → Reducing Vomiting
- 6Use nasogastric ORS before intravenous fluids when oral intake fails but the child is not in shock → When Oral Fails
- 7Reserve rapid intravenous boluses for clinical shock, and reassess after every bolus → IV Therapy
- 8Continue age-appropriate feeding and never withhold breastfeeding during rehydration → Feeding
Pediatric Dehydration Assessment: Grading Fluid Loss
Severity grading is the first and most consequential step in pediatric dehydration assessment, because the estimated deficit drives the volume, the route, and the urgency of replacement. No single sign is reliable on its own, so the most defensible approach combines several findings into a graded estimate.
In any pediatric dehydration assessment, the most informative individual signs are prolonged capillary refill, abnormal skin turgor, and an abnormal respiratory pattern. When several of these cluster together, the probability of a clinically important deficit rises sharply.
Grade severity using a combination of capillary refill time, skin turgor, mucous membranes, eyes, tears, mental state, and urine output rather than relying on body-weight change alone, which is rarely known at presentation.
Strong Rec Moderate Evidence NICE NG84 WHOEvaluate for red-flag features at every pediatric dehydration assessment that signal progression toward shock: sustained tachycardia, prolonged capillary refill beyond two seconds, cool mottled peripheries, reduced consciousness, and absent urine output.
Strong Rec Moderate Evidence NICE NG84Consider serum electrolytes, glucose, and venous gas when pediatric dehydration assessment places a child in the moderate or severe range, when intravenous fluids are needed, or when the picture suggests hypernatraemia such as a doughy skin feel or marked irritability.
Conditional Rec Low Evidence ESPGHAN 2014Reading the Signs: A Severity Reference
The table below is organised by clinical sign so your pediatric dehydration assessment can run head-to-toe and build a severity picture, rather than memorising fixed percentage bands. The estimated deficit is offered as a planning range, not a precise measurement.
| Clinical Sign | Minimal / None | Some Loss | Marked Loss | What to Do |
|---|---|---|---|---|
| General state | Alert, content | Restless or irritable | Lethargic, floppy, or reduced consciousness | Reduced consciousness escalates to shock pathway |
| Eyes | Normal | Slightly sunken | Deeply sunken | Combine with other signs — poor specificity alone |
| Skin turgor | Instant recoil | Recoil under 2 seconds | Tented, recoil over 2 seconds | One of the more reliable individual signs |
| Capillary refill | Under 2 seconds | 2–3 seconds, central | Over 3 seconds, cool peripheries | Test centrally on the sternum, not a cold finger |
| Urine output | Normal nappies | Reduced, darker | Minimal or none for many hours | Ask carers for the time of the last wet nappy |
| Planning deficit | Under 3% of body weight | Roughly 3–8% of body weight | Around 9% or more of body weight | Treat as a range to guide volume, not a fixed figure |
Children with high-sodium fluid loss can preserve their circulating volume until late, so the usual signs underestimate the true deficit and a routine pediatric dehydration assessment can mislead. Suspect it when the child feels doughy to touch, is jittery or hyperirritable, or has a high-pitched cry.
Oral Rehydration After Pediatric Dehydration Assessment
Once pediatric dehydration assessment places a child in the mild-to-moderate range without shock, oral rehydration with a low-osmolarity solution is the treatment of choice. It is as effective as intravenous fluid for most children, carries fewer complications, and can begin immediately without waiting for cannulation.
When pediatric dehydration assessment points to mild or moderate loss, the reduced-osmolarity formulation is preferred worldwide because it shortens the duration of diarrhoea, reduces vomiting, and lowers the need for unscheduled intravenous fluid compared with older higher-osmolarity recipes.
Start low-osmolarity oral rehydration solution as first-line treatment for every child with mild or moderate fluid loss who can drink and is not vomiting uncontrollably.
Strong Rec High Evidence WHO ESPGHAN 2014Give ORS in small, frequent sips — for example 5 mL by syringe or spoon every one to two minutes — and increase the amount as tolerance improves. Frequent tiny volumes are absorbed even when a child refuses a full drink.
Strong Rec Moderate Evidence AAP/CDCDo not use plain water, fruit juice, carbonated drinks, or sports drinks as the rehydration fluid, because their electrolyte and sugar content can worsen diarrhoea and disturb sodium balance.
Against Moderate Evidence NICE NG84Counsel carers on continuing maintenance ORS after each loose stool once the deficit is replaced, so ongoing losses do not undo the rehydration already achieved.
Moderate Rec Moderate Evidence WHOFluid Volumes by Clinical Scenario
This table is organised by the clinical scenario in front of you rather than by a fixed dehydration percentage, so you can move from a completed pediatric dehydration assessment to a plan in one step. Volumes assume a child who is not shocked; shock is handled separately on the intravenous pathway.
| Clinical Scenario | Fluid & Route | Volume Target | Over What Time | Practical Tips |
|---|---|---|---|---|
| No clinical dehydration, ongoing losses | Maintenance ORS, oral | Replace each stool plus normal fluids | Continuous, as losses occur | Send carers home with a clear per-stool amount and safety-net advice |
| Mild to moderate loss, drinking | Low-osmolarity ORS, oral | 50–100 mL/kg deficit plus maintenance | Replace deficit over 3–4 hours | Reassess hydration at the end of the replacement window |
| Vomiting limiting oral intake | ORS plus single-dose ondansetron, oral | As above once vomiting settles | Re-offer ORS 15–30 minutes after the dose | Weight-based dosing; a single dose is usually enough |
| Oral route failing, not shocked | ORS via nasogastric tube | Same deficit target, delivered by tube | Steady infusion over several hours | An effective alternative before resorting to a cannula |
| Shock or failed enteral route | Isotonic crystalloid, IV or IO | Bolus per weight, then deficit plus maintenance | Bolus rapidly, reassess immediately | Reassess after every bolus; escalate if no response |
Volumes are planning guides. Always verify dosing against a current pediatric formulary and local protocol before administration.
Reducing Vomiting to Rescue the Oral Route
Vomiting is the single biggest obstacle to oral rehydration, and once a pediatric dehydration assessment has cleared a child for the enteral route it is often the deciding factor between going home and being admitted. A targeted antiemetic strategy can keep many children on the enteral pathway.
Consider a single weight-based dose of oral ondansetron in children older than six months with vomiting that is blocking oral rehydration, to improve the chance of successful enteral treatment and reduce the need for intravenous fluids.
Moderate Rec High Evidence AAP/CDC ESPGHAN 2014Avoid routine use of metoclopramide and other older antiemetics in young children because of the risk of extrapyramidal side effects, which outweighs the modest benefit in this setting.
Conditional Rec Moderate Evidence ESPGHAN 2014Reassess the child 15–30 minutes after an antiemetic dose and resume small-volume ORS; persistent vomiting despite ondansetron is a signal to step up to nasogastric or intravenous fluids.
Moderate Rec Low Evidence AAP/CDCWhen Oral Rehydration Fails: Nasogastric and Intravenous Routes
Escalation is a stepwise decision, not a jump straight to a drip, and a repeated pediatric dehydration assessment should drive each step. The nasogastric route bridges the gap between a failing oral attempt and intravenous fluids, and it spares many children a cannula.
Use nasogastric ORS for children who cannot drink enough but are not in shock, delivering the same deficit volume steadily by tube before considering intravenous access.
Moderate Rec Moderate Evidence NICE NG84 ESPGHAN 2014Prescribe an isotonic crystalloid for intravenous rehydration when it is needed, and replace the calculated deficit alongside maintenance rather than as a single rapid correction in the non-shocked child.
Strong Rec Moderate Evidence NICE NG84Perform a rapid bolus of isotonic fluid for any child with signs of shock, then reassess heart rate, perfusion, and conscious level immediately, repeating and escalating to senior support if the response is inadequate.
Strong Rec Moderate Evidence NICE NG84 WHOTransition back to oral rehydration as soon as the child can tolerate it, since prolonged intravenous fluids add no benefit once the gut is working and delay discharge.
Moderate Rec Moderate Evidence ESPGHAN 2014Feeding and Adjuncts During Recovery
Nutrition during gastroenteritis has shifted decisively away from gut rest, and feeding decisions follow on directly from the pediatric dehydration assessment. Early, normal feeding shortens illness and supports recovery, and breastfeeding should continue throughout.
Continue breastfeeding throughout rehydration and resume an age-appropriate normal diet as soon as the deficit is replaced, without a period of starvation or diluted feeds.
Strong Rec High Evidence WHO ESPGHAN 2014Consider supplemental zinc in settings where deficiency is prevalent, as it reduces the duration and severity of diarrhoea in young children in those populations.
Conditional Rec High Evidence WHODo not prescribe antidiarrhoeal agents such as loperamide to young children, because they carry a risk of serious adverse effects and do not address fluid loss.
Against Moderate Evidence ESPGHAN 2014 AAP/CDCClinical Decision Pathway
A practical, question-based route through the child with acute gastroenteritis that turns a pediatric dehydration assessment into a plan. Work through the questions in order, starting with the one that overrides everything else.
Monitoring and Follow-Up
Rehydration is a process to be watched, not a one-off prescription, and a repeat pediatric dehydration assessment is the backbone of follow-up. The table below organises monitoring by what you are tracking and the pitfalls that catch clinicians out.
| What to Track | When to Check | What Good Looks Like | Common Pitfalls |
|---|---|---|---|
| Hydration signs | At the end of the deficit-replacement window | Signs resolving, child more alert and active | Discharging before a formal reassessment |
| Fluid balance | Hourly during active rehydration | Intake exceeding ongoing losses | Forgetting to add ongoing stool losses to the target |
| Urine output | Throughout, via nappies or toileting | Return of regular wet nappies | Mistaking watery stool in the nappy for urine |
| Electrolytes | During intravenous therapy or if hypernatraemia suspected | Sodium correcting gradually, not abruptly | Correcting sodium too quickly in hypernatraemia |
| Weight | At presentation and after rehydration where feasible | Weight trending back toward the well baseline | Relying on an unverified historical weight |
Evidence in Context
Where the major frameworks agree, where they diverge, and what the trial evidence adds for pediatric dehydration assessment and rehydration.
Where the Major Frameworks Agree
NICE, WHO, ESPGHAN, and the AAP converge on the essentials: assess dehydration clinically using a cluster of signs, treat mild-to-moderate loss with low-osmolarity ORS as first-line, continue feeding, and reserve intravenous fluids for shock or enteral failure. The shared message is that most children never need a cannula.
Where They Differ
Deficit timing and IV rate: some frameworks favour replacing the deficit gradually over several hours, while others describe more rapid intravenous rehydration protocols in selected children. Antiemetic emphasis also varies, with North American guidance more explicitly endorsing ondansetron to support oral therapy.
Ondansetron: What the Trials Show
Randomised evidence shows that a single oral dose of ondansetron reduces vomiting, improves the success of oral rehydration, and lowers both intravenous fluid use and immediate admission in children with gastroenteritis. A modest increase in loose stools is the main trade-off.
Prevention and the Bigger Picture
Rotavirus immunisation has substantially cut severe gastroenteritis and dehydration-related admissions where it is in routine use. Prevention sits alongside good rehydration practice as the two highest-impact levers on the burden of childhood diarrhoeal disease.
References
- 1.National Institute for Health and Care Excellence. Diarrhoea and vomiting caused by gastroenteritis in under 5s: diagnosis and management. NICE Guideline NG84. nice.org.uk/guidance/ng84
- 2.Guarino A, Ashkenazi S, Gendrel D, et al. European Society for Paediatric Gastroenterology, Hepatology, and Nutrition/European Society for Paediatric Infectious Diseases Evidence-Based Guidelines for the Management of Acute Gastroenteritis in Children in Europe: Update 2014. J Pediatr Gastroenterol Nutr. 2014;59(1):132–152. doi:10.1097/MPG.0000000000000375
- 3.Freedman SB, Adler M, Seshadri R, Powell EC. Oral Ondansetron for Gastroenteritis in a Pediatric Emergency Department. N Engl J Med. 2006;354(16):1698–1705. doi:10.1056/NEJMoa055119
- 4.King CK, Glass R, Bresee JS, Duggan C. Managing Acute Gastroenteritis Among Children: Oral Rehydration, Maintenance, and Nutritional Therapy. MMWR Recomm Rep. 2003;52(RR-16):1–16. cdc.gov/mmwr/preview/mmwrhtml/rr5216a1.htm
- 5.Gorelick MH, Shaw KN, Murphy KO. Validity and Reliability of Clinical Signs in the Diagnosis of Dehydration in Children. Pediatrics. 1997;99(5):e6. doi:10.1542/peds.99.5.e6
How to Read the Evidence Tags
Every recommendation in this pediatric dehydration assessment article carries two tags — one for recommendation strength and one for evidence quality. These are Medaptly’s own simplified interpretations, designed for quick clinical reading rather than reproducing any guideline body’s grading system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise to the child. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |