
Acute Mesenteric Ischemia: A Surgical Diagnosis-to-Revascularization Guide
Clinical Practice Update — Early Recognition, CT Angiography, and Time-Critical Revascularization in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Rapid acute mesenteric ischemia diagnosis and time-critical revascularization in adults
- Target Audience
- General and vascular surgeons, emergency physicians, intensivists, surgical residents
- Setting
- Emergency department, surgical assessment unit, operating theatre, ICU
- Source Evidence
- •WSES Guidelines on Acute Mesenteric Ischaemia (2017)
- •ESVS Clinical Practice Guidelines on Mesenteric Vascular Disease (2017)
- •AGA Clinical Practice Update on Acute Mesenteric Ischemia (2017)
- •Bala et al., Acute Mesenteric Ischemia Review (World J Emerg Surg, 2022)
Key Clinical Takeaways
Effective acute mesenteric ischemia diagnosis rests on a single principle: suspect it early and image it fast. The condition kills because the diagnosis is delayed, not because it cannot be treated. The points below distill the evidence into actionable rules for the bedside, the scanner, and the operating theatre.
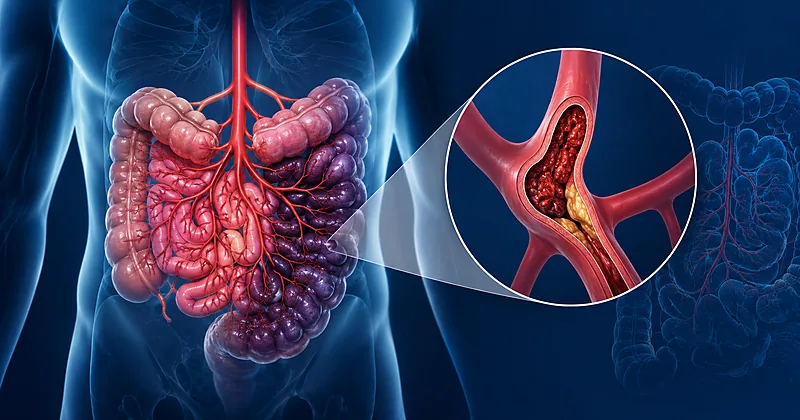
- 1Pain out of proportion to abdominal findings in an older patient with a cardiovascular history is acute mesenteric ischemia until proven otherwise → Recognising the Patient
- 2Triphasic CT angiography is the diagnostic test of choice — never delay it to obtain renal function or trial conservative management → Imaging
- 3A normal lactate does not exclude the diagnosis — lactate rises late, once transmural necrosis is established → Biomarkers
- 4Identify the mechanism on imaging — embolic, thrombotic, non-occlusive, or venous — because it dictates the revascularization strategy → Classifying the Cause
- 5Start systemic anticoagulation and broad-spectrum antibiotics the moment the diagnosis is confirmed, before definitive treatment → Initial Resuscitation
- 6Peritonitis or radiological bowel necrosis mandates immediate laparotomy — endovascular-first is for patients without peritoneal signs → Choosing Revascularization
- 7Revascularize before resecting — restoring flow first lets marginal bowel declare its true viability → Operative Sequence
- 8Plan a second-look laparotomy at 24 to 48 hours whenever bowel viability was uncertain at the index operation → Second-Look Surgery
Who Should Raise Suspicion: The First Step in Acute Mesenteric Ischemia Diagnosis
The earliest and most decisive step in acute mesenteric ischemia diagnosis happens before any test is ordered: recognising the at-risk patient. The classic triad of severe pain, gut emptying, and a cardiac source of embolus appears in a minority, so clinical suspicion must outrun the textbook.
Evaluate for acute mesenteric ischemia in any patient over 60 with sudden severe abdominal pain that is disproportionate to examination findings, particularly with atrial fibrillation, recent myocardial infarction, or known atherosclerotic disease.
Strong Rec Moderate Evidence WSES 2017 ESVS 2017Consider non-occlusive mesenteric ischemia in critically ill patients on vasopressors or with low cardiac output who develop unexplained abdominal distension, rising lactate, or feeding intolerance, even without dramatic pain.
Conditional Rec Low Evidence WSES 2017Ask specifically about postprandial pain, food fear, and unintentional weight loss, which point toward acute-on-chronic mesenteric ischemia from progressive atherosclerotic stenosis.
Moderate Rec Moderate Evidence ESVS 2017Imaging and Biomarkers: Confirming Acute Mesenteric Ischemia Diagnosis
Once suspicion is raised, confirming the acute mesenteric ischemia diagnosis is a race against bowel necrosis. CT angiography is the linchpin; laboratory tests support but never replace it.
Perform triphasic (non-contrast, arterial, and portal-venous) CT angiography of the abdomen as the first-line investigation in any patient with suspected acute mesenteric ischemia.
Strong Rec High Evidence WSES 2017 ESVS 2017Do not withhold or delay contrast-enhanced CT to await creatinine results or out of concern for contrast-induced nephropathy; the risk of missed bowel infarction far exceeds the renal risk.
Strong Rec Moderate Evidence WSES 2017Do not rely on plain abdominal radiographs or non-contrast CT to exclude the diagnosis; their findings appear late and a normal study is falsely reassuring.
Against Moderate Evidence ESVS 2017Interpret a raised lactate, leucocytosis, and metabolic acidosis as markers of established or advanced ischemia rather than early diagnostic tools; normal values do not rule the condition out.
Moderate Rec Moderate Evidence AGA 2017CT Angiography Findings by Phase
| CT Phase | What It Shows | Key Positive Finding | Practical Tip |
|---|---|---|---|
| Non-contrast | Baseline bowel wall density, calcified plaque | Hyperdense thrombus in a vessel; mural gas | Skipping this phase hides spontaneous hyperdensity of acute clot. |
| Arterial | SMA and coeliac patency, embolus vs thrombus | Filling defect, abrupt cut-off, ostial occlusion | Embolus typically lodges a few cm distal to the SMA origin. |
| Portal-venous | Bowel wall enhancement, venous patency | Reduced or absent wall enhancement; SMV thrombus | Poor enhancement plus dilatation suggests non-viable bowel. |
| Any phase | Late or ominous signs | Pneumatosis, portal venous gas, free air | These signal necrosis — the patient needs theatre, not more imaging. |
Classifying the Mechanism to Direct Treatment
Diagnosis is incomplete until the mechanism is named. The four causes behave differently, present differently, and demand different revascularization approaches. The table below maps each to its imaging signature and preferred intervention.
| Mechanism | Typical Patient | Imaging Signature | Preferred Revascularization |
|---|---|---|---|
| SMA embolism | AF, recent MI, sudden onset | Filling defect a few cm distal to SMA origin, spared proximal branches | Open embolectomy or aspiration thrombectomy |
| SMA thrombosis | Known atherosclerosis, prior food fear | Ostial occlusion, heavy calcification, collaterals | Stenting or bypass; hybrid approach if laparotomy needed |
| Non-occlusive (NOMI) | ICU, vasopressors, low output | Patent main vessels, diffuse vasospasm, segmental hypoperfusion | Correct the cause; intra-arterial vasodilator, no clot to remove |
| Venous (MVT) | Younger, thrombophilia, portal hypertension | SMV filling defect, bowel wall oedema, mesenteric stranding | Systemic anticoagulation first-line; surgery only for necrosis |
Initial Resuscitation Before Definitive Treatment
The moment the diagnosis is confirmed, resuscitation and revascularization preparation run in parallel. These steps buy time and reduce reperfusion injury while the definitive plan is mobilised.
Start a therapeutic unfractionated heparin infusion as soon as the diagnosis is confirmed, unless active haemorrhage contraindicates it, to limit clot propagation.
Strong Rec Moderate Evidence WSES 2017Initiate broad-spectrum intravenous antibiotics covering gut flora, since mucosal barrier breakdown promotes bacterial translocation even before perforation.
Moderate Rec Low Evidence WSES 2017Resuscitate with balanced crystalloid, correct electrolyte and acid-base derangement, and place a nasogastric tube and urinary catheter to guide volume status.
Strong Rec Low Evidence ESVS 2017Avoid vasoconstrictor agents where possible, and where vasopressors are unavoidable favour those with less splanchnic vasoconstriction to protect marginal bowel.
Conditional Rec Low Evidence AGA 2017Choosing the Revascularization Strategy
The single most important branch point is whether the abdomen shows peritonitis. Peritoneal signs or radiological necrosis send the patient straight to laparotomy; their absence opens the door to an endovascular-first approach in suitable anatomy.
Perform immediate exploratory laparotomy in any patient with peritonitis, free air, or CT evidence of bowel necrosis, regardless of the underlying mechanism.
Strong Rec High Evidence WSES 2017 ESVS 2017Consider an endovascular-first strategy (aspiration thrombectomy, thrombolysis, or stenting) in haemodynamically stable patients without peritoneal signs and with suitable arterial anatomy.
Moderate Rec Moderate Evidence ESVS 2017Restore mesenteric blood flow before resecting any bowel; reperfusion allows ischaemic-but-viable segments to recover and minimises the length ultimately removed.
Strong Rec Moderate Evidence WSES 2017Adopt a damage control surgery approach with a temporary abdominal closure when the patient is physiologically unstable or bowel viability is uncertain, deferring definitive anastomosis.
Moderate Rec Moderate Evidence WSES 2017Treat mesenteric venous thrombosis without peritonitis with systemic anticoagulation alone, reserving operative intervention for signs of transmural necrosis.
Strong Rec Moderate Evidence AGA 2017Clinical Decision Pathway
A practical, question-based route from suspicion to revascularization. Work through the questions in order.
Second-Look Surgery, Monitoring, and Follow-Up
Postoperative care centres on reassessing marginal bowel, watching for reperfusion injury, and arranging the secondary prevention that prevents recurrence.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| Second-look laparotomy | 24–48h after index surgery | Demarcation of viable vs necrotic bowel | Skipping it because the patient “looks better” — viability is decided at operation, not at the bedside |
| Serum lactate and pH | Serially in the first 24–48h | A failure to clear suggests ongoing ischemia | Attributing a rising lactate solely to reperfusion and missing a new infarct |
| Graft or stent patency | Before discharge and at follow-up | Duplex or CT confirming sustained flow | Discharging without a surveillance plan after stenting |
| Nutritional status | Throughout recovery | Adequacy of absorption after extensive resection | Underestimating short bowel syndrome after major small-bowel loss |
Continue therapeutic anticoagulation after revascularization and arrange a thrombophilia and cardiac source evaluation to define the cause and prevent recurrence.
Moderate Rec Moderate Evidence ESVS 2017Counsel patients with atherosclerotic disease on antiplatelet therapy, statin treatment, and smoking cessation to reduce the risk of recurrent mesenteric and cardiovascular events.
Strong Rec High Evidence ESVS 2017Evidence in Context
Where the major sources agree, where they differ, and what the data say about evolving practice.
Where WSES, ESVS, and AGA Agree
All three sources converge on early CT angiography as the diagnostic standard, the futility of waiting for biomarkers, the principle of revascularizing before resecting, and the central role of timely intervention in determining survival.
Open vs Endovascular Revascularization
Observational data suggest endovascular revascularization may reduce the length of bowel resected and shorten recovery in selected stable patients, while open surgery retains the advantage of direct bowel inspection. The absence of peritonitis is the practical gatekeeper for an endovascular-first attempt.
Why Mortality Remains High
Despite advances in technique, reported mortality remains substantial, driven overwhelmingly by delayed diagnosis rather than by the limits of revascularization. Roughly half of patients die when the diagnosis is made late, which is why the emphasis falls so heavily on early suspicion.
The Role of Intra-Arterial Vasodilators in NOMI
For non-occlusive disease there is no clot to extract, so management hinges on correcting the precipitating low-flow state. Intra-arterial vasodilator infusion is described as an adjunct, though the supporting evidence is limited to small series and consensus.
References
- 1.Bala M, Kashuk J, Moore EE, et al. Acute mesenteric ischemia: guidelines of the World Society of Emergency Surgery. World J Emerg Surg. 2017;12:38. doi:10.1186/s13017-017-0150-5
- 2.Björck M, Koelemay M, Acosta S, et al. Editor’s Choice – Management of the Diseases of Mesenteric Arteries and Veins: Clinical Practice Guidelines of the ESVS. Eur J Vasc Endovasc Surg. 2017;53(4):460–510. doi:10.1016/j.ejvs.2017.01.010
- 3.Clair DG, Beach JM. Mesenteric Ischemia. N Engl J Med. 2016;374(10):959–968. doi:10.1056/NEJMra1503884
- 4.Bala M, Catena F, Kashuk J, et al. Acute mesenteric ischemia: updated guidelines of the World Society of Emergency Surgery. World J Emerg Surg. 2022;17:54. doi:10.1186/s13017-022-00443-x
How to Read the Evidence Tags
Every recommendation carries a strength tag and an evidence-quality tag — Medaptly’s own simplified interpretations, not a reproduction of any guideline body’s grading system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed studies or high-quality meta-analyses. |
| Moderate Evidence | Single trial or large observational studies. |
| Low Evidence | Expert consensus or small studies. |