
Acute Compartment Syndrome: A Diagnosis-to-Fasciotomy Guide
Clinical Practice Update — Recognition, Pressure Measurement, and Surgical Decompression in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Diagnosis and surgical decompression of acute compartment syndrome of the limb
- Target Audience
- Orthopaedic surgeons, trauma surgeons, emergency physicians, residents
- Setting
- Emergency department, trauma bay, operating theatre, surgical ward
- Source Evidence
- •BOAST — Diagnosis and Management of Compartment Syndrome of the Limbs (2016)
- •AAOS Clinical Practice Guidance on Acute Compartment Syndrome
- •McQueen & Court-Brown — Compartment Pressure Thresholds (JBJS)
- •von Keudell et al. — Diagnosis and Treatment of Acute Compartment Syndrome (Lancet, 2015)
Key Clinical Takeaways
Acute compartment syndrome is a surgical emergency where rising pressure inside a closed fascial space chokes off perfusion and threatens the limb. The window between recognition and decompression is narrow, so the clinician’s job is to suspect it early, confirm it confidently, and move to fasciotomy without delay. The points below distil the evidence into rules you can apply at the bedside.
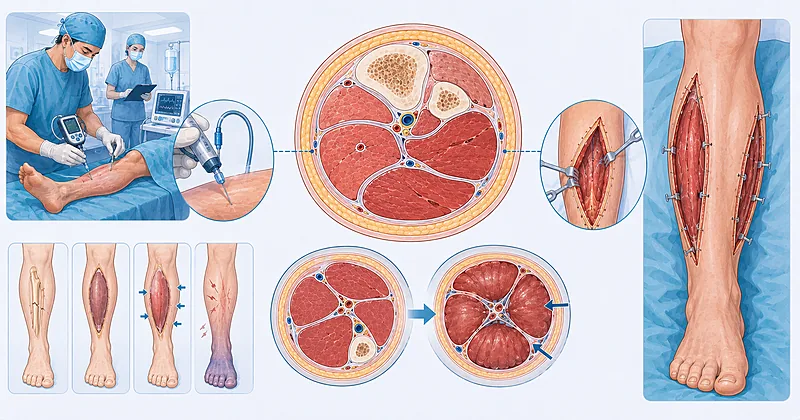
- 1Treat pain out of proportion to the injury, worsened by passive stretch, as acute compartment syndrome until proven otherwise → Recognising It
- 2Do not wait for pulselessness, pallor, or paralysis — these are late and ominous, not diagnostic → Recognising It
- 3Measure compartment pressure when the picture is unclear or the patient cannot report symptoms → Confirming It
- 4Use the perfusion pressure (diastolic minus compartment pressure) rather than an absolute number as your threshold → Confirming It
- 5Remove all circumferential casts and dressings and elevate the limb to heart level while you decide → First Response
- 6Perform fasciotomy urgently once the diagnosis is made — aim for decompression within hours, not the next list → Fasciotomy
- 7Release every compartment of the affected segment fully — a partial or short fasciotomy is a failed fasciotomy → Fasciotomy
- 8Leave wounds open, plan a relook at 48 hours, and watch for rhabdomyolysis after release → After Surgery
Recognising Acute Compartment Syndrome Early
The diagnosis of acute compartment syndrome is primarily clinical, and the earliest reliable signal is pain that outstrips what the underlying injury should produce. Tibial diaphyseal fractures account for the largest share of cases, but the syndrome also follows crush injuries, vascular insults, tight casts, prolonged limb compression, and even relatively minor trauma in anticoagulated patients.
Evaluate for acute compartment syndrome in any patient with escalating limb pain, a tense swollen compartment, and pain on passive stretch of the muscles within it. Treat increasing analgesic demand as a warning sign rather than a comfort target.
Strong Rec Moderate Evidence BOAST 2016Maintain heightened suspicion in high-risk settings: tibial shaft fracture, forearm and supracondylar fractures, crush and reperfusion injuries, and obtunded or regionally anaesthetised patients who cannot report pain.
Strong Rec Moderate Evidence BOAST 2016 Lancet 2015Do not rely on the classic “five Ps” (pain, pallor, paraesthesia, pulselessness, paralysis) to make the diagnosis. Pulse loss and paralysis reflect established ischaemia, and waiting for them risks irreversible muscle and nerve injury.
Against Moderate Evidence AAOSConfirming Acute Compartment Syndrome with Pressure Measurement
When the clinical picture is convincing in an alert patient, you can proceed to surgery on clinical grounds alone. Pressure measurement earns its place when symptoms are equivocal, when the patient is sedated, intubated, or has a regional block, or when continuous monitoring would help track a borderline limb over time.
Measure intracompartmental pressure with a calibrated needle device when the diagnosis of acute compartment syndrome is uncertain or the patient cannot be assessed clinically. Take the reading within 5 cm of the fracture, where pressure peaks.
Strong Rec Moderate Evidence BOAST 2016Base the surgical decision on perfusion pressure (diastolic blood pressure minus measured compartment pressure) rather than an absolute compartment reading. A sustained perfusion pressure at or below 30 mmHg supports fasciotomy, and this gradient-based threshold reduces unnecessary surgery compared with a fixed cutoff.
Moderate Rec Moderate Evidence McQueen JBJSConsider continuous compartment monitoring in obtunded or anaesthetised high-risk patients, where serial clinical examination is impossible. A single normal reading does not exclude evolving acute compartment syndrome — repeat or monitor when suspicion persists.
Conditional Rec Low Evidence BOAST 2016Interpreting the Numbers at the Bedside
| Clinical Situation | What the Reading Suggests | Your Move | Easy Mistake to Avoid |
|---|---|---|---|
| Alert patient, classic clinical signs | Diagnosis already made clinically | Go to theatre — measurement is optional | Delaying surgery to “confirm” with a needle |
| Perfusion pressure above 30 mmHg, improving | Decompression not yet indicated | Reassess closely; repeat if symptoms change | Treating one reading as the whole story |
| Perfusion pressure 30 mmHg or less, sustained | Supports acute compartment syndrome | Proceed to urgent fasciotomy | Measuring far from the fracture and under-reading |
| Sedated or blocked patient, rising trend | High concern despite no symptoms | Monitor continuously; low threshold to operate | Assuming a block masks a benign course |
First Response Before the Operating Theatre
The minutes between suspicion and definitive surgery are not idle. A few immediate manoeuvres can buy perfusion and prevent the gradient from worsening while theatre and anaesthesia are mobilised.
Remove all circumferential casts, splints, and tight dressings immediately, splitting the cast and underlying padding down to skin. Constrictive material can raise compartment pressure substantially on its own.
Strong Rec Moderate Evidence BOAST 2016Position the limb at heart level rather than elevating it above the heart. Raising the limb lowers arterial inflow and narrows the perfusion gradient, worsening ischaemia in a tight compartment.
Strong Rec Low Evidence Lancet 2015Restore normal blood pressure and give supplemental oxygen, correcting hypovolaemia and hypotension promptly. Adequate systemic perfusion widens the gradient and protects marginal muscle while you prepare to operate.
Strong Rec Low Evidence AAOSAvoid regional anaesthesia and dense nerve blocks in a limb at risk, since analgesia can mask the cardinal symptom of escalating pain and delay recognition. Document neurovascular status before any block is placed.
Conditional Rec Low Evidence BOAST 2016Fasciotomy: Timing and Technique
Fasciotomy is the only definitive treatment, and its success is governed by two things: how quickly it is done and how completely it is done. Decompression within roughly six hours of onset gives the best chance of full muscle recovery, while delay beyond that window increases the risk of necrosis, contracture, and amputation.
Perform emergency fasciotomy as soon as the diagnosis is confirmed, treating it as a limb-threatening emergency with the same urgency as a vascular catastrophe. Escalate to the on-call surgeon and theatre team without waiting for the next scheduled list.
Strong Rec Moderate Evidence BOAST 2016Decompress every compartment of the affected segment through full-length skin incisions. For the leg, a four-compartment release via two incisions is standard; short skin incisions that do not fully open the fascia leave residual pressure and fail.
Strong Rec Moderate Evidence AAOS Lancet 2015Assess muscle viability at decompression using colour, consistency, contractility, and capacity to bleed. Preserve all muscle that is potentially viable and defer firm decisions on borderline tissue to the planned relook.
Moderate Rec Low Evidence AAOSLeave fasciotomy wounds open and apply a temporary dressing or negative-pressure system rather than closing under tension. Primary closure of a freshly decompressed compartment recreates the very pressure you released.
Strong Rec Moderate Evidence BOAST 2016Weigh the risks carefully before late fasciotomy in a limb presenting well beyond 24–36 hours with established muscle death. Opening necrotic muscle invites infection and systemic insult, and selected very late cases may be better managed expectantly.
Conditional Rec Low Evidence Lancet 2015Decompression by Limb Segment
| Limb Segment | Compartments to Release | Usual Approach | Watch Out For |
|---|---|---|---|
| Leg | Anterior, lateral, superficial and deep posterior (4) | Two-incision medial and lateral release | Missing the deep posterior compartment; protect the saphenous vein and nerve medially |
| Forearm | Volar, dorsal, mobile wad (3) | Volar curved incision, extend across carpal tunnel | Releasing the carpal tunnel; covering exposed nerves and tendons |
| Thigh | Anterior, posterior, medial (3) | Single lateral incision, add medial if needed | Large blood loss; often follows major crush or vascular injury |
| Foot | Multiple, including interosseous and calcaneal | Dorsal incisions over the metatarsals | Indication is debated; weigh function against wound morbidity |
Clinical Decision Pathway
A practical, question-based route from first suspicion to decompression. Work through the questions in order.
Monitoring and Follow-Up After Release
The job is not finished when the fascia is open. Reperfused muscle releases myoglobin and potassium, wounds need staged management, and the limb requires structured rehabilitation to recover function.
| What to Watch | When | Action Trigger | Common Pitfall |
|---|---|---|---|
| Creatine kinase and renal function | From release, then serially | Rising CK or falling urine output → aggressive fluids | Forgetting rhabdomyolysis can appear hours after decompression |
| Potassium and acid-base | Early post-reperfusion | Hyperkalaemia → treat and monitor ECG | Underestimating the reperfusion potassium surge |
| Wound and muscle at relook | 48 hours, then as needed | Non-viable muscle → debride at relook | Closing too early and trapping marginal tissue |
| Function and contracture | From early recovery onward | Stiffness or weakness → physiotherapy referral | Neglecting rehabilitation once the wound heals |
Monitor creatine kinase, potassium, and renal function after decompression, and start early fluid resuscitation to protect the kidneys from myoglobin load. Reperfusion of ischaemic muscle can precipitate clinically significant rhabdomyolysis.
Strong Rec Moderate Evidence AAOSReturn the patient to theatre for a planned relook at around 48 hours to reassess viability, debride necrotic muscle, and progress wound closure. Stage closure with delayed primary suture, skin grafting, or negative-pressure therapy as the limb allows.
Strong Rec Low Evidence BOAST 2016Refer early for physiotherapy and rehabilitation, and counsel patients that recovery of strength and range of motion can take months. Document a clear neurovascular and functional baseline to track progress and detect late contracture.
Moderate Rec Low Evidence Lancet 2015Evidence in Context
What the evidence supports, where guidance is consistent, and where genuine uncertainty remains.
Where the Guidance Agrees
There is broad consensus that the diagnosis is primarily clinical, that escalating pain and pain on passive stretch are the key early signs, that the late “P” signs should not be awaited, and that complete and timely fasciotomy is the only definitive treatment. Sources also agree that constricting dressings should be removed and the limb kept at heart level while preparing for surgery.
The Threshold Debate: Absolute vs Differential Pressure
Earlier practice leaned on absolute compartment pressures, but work by McQueen and colleagues showed that a differential (perfusion) pressure threshold reduces unnecessary fasciotomy by accounting for the patient’s blood pressure. A perfusion pressure at or below 30 mmHg is now widely used, though the ideal single number and the role of continuous monitoring remain debated.
How Tight Is the Time Window?
The commonly cited six-hour figure reflects experimental and clinical observations that muscle tolerates only a few hours of profound ischaemia, but real cases vary with the degree of ischaemia and collateral flow. The practical message is consistent: decompress as early as possible and do not use an arbitrary cutoff to justify delay.
The Very Late Presentation
In limbs presenting after prolonged ischaemia with established necrosis, opening the compartments can convert a sterile field into an infected one and trigger a systemic insult. Some authors advise caution with fasciotomy in this narrow group, individualising the decision rather than reflexively decompressing.
References
- 1.von Keudell AG, Weaver MJ, Appleton PT, et al. Diagnosis and treatment of acute extremity compartment syndrome. Lancet. 2015;386(10000):1299–1310. doi:10.1016/S0140-6736(15)00277-9
- 2.McQueen MM, Court-Brown CM. Compartment monitoring in tibial fractures. The pressure threshold for decompression. J Bone Joint Surg Br. 1996;78(1):99–104. pubmed.ncbi.nlm.nih.gov/8898137
- 3.McQueen MM, Gaston P, Court-Brown CM. Acute compartment syndrome. Who is at risk? J Bone Joint Surg Br. 2000;82(2):200–203. pubmed.ncbi.nlm.nih.gov/10755426
- 4.Via AG, Oliva F, Spoliti M, Maffulli N. Acute compartment syndrome. Muscles Ligaments Tendons J. 2015;5(1):18–22. pubmed.ncbi.nlm.nih.gov/25878982
How to Read the Evidence Tags
Every recommendation carries two tags for recommendation strength and evidence quality — Medaptly’s own simplified interpretations, not any guideline body’s classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed studies or high-quality syntheses. |
| Moderate Evidence | Single study or large observational data. |
| Low Evidence | Expert consensus or small studies. |