
Duchenne Gene Therapy: 5 Critical Practice Considerations
Restoring the missing protein is now achievable — but whether a surrogate biomarker predicts real clinical benefit remains the central unanswered question.
One-Minute Takeaway
- Duchenne gene therapy and exon-skipping drugs reliably raise dystrophin in muscle, but randomized-controlled-trial evidence that this surrogate protein marker predicts meaningful clinical benefit is still lacking.
- The pivotal randomized trial of delandistrogene moxeparvovec (EMBARK, n=125) did not meet its primary functional endpoint at 52 weeks; several secondary measures numerically favored treatment.
- A confirmatory exon-53 trial (RACER53) also missed its primary motor endpoint, echoing the same protein-versus-outcome gap.
- In November 2025 the FDA added a boxed warning to delandistrogene moxeparvovec for fatal acute liver failure and limited use to ambulatory patients aged 4 and older.
- Decisions should weigh reliable biomarker change against unconfirmed clinical efficacy, real safety risks, and cost; corticosteroids remain the evidence-based foundation.
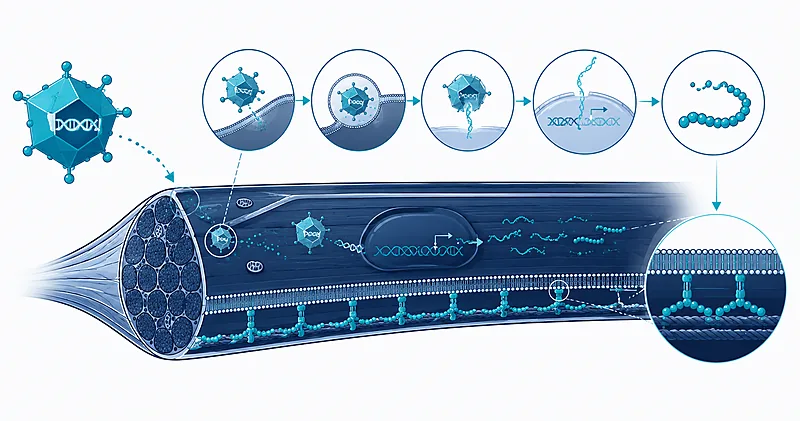
Why Duchenne Gene Therapy Matters
Duchenne muscular dystrophy is an X-linked disorder caused by mutations in the DMD gene, the largest gene in the human genome, that abolish functional dystrophin. Without this membrane-stabilizing protein, muscle fibers degenerate progressively from early childhood.
Boys typically lose independent walking in the early teenage years, followed by respiratory and cardiac decline. Corticosteroids and multidisciplinary care remain the backbone of management. Against this trajectory, a treatment that targets the underlying genetic defect carries obvious appeal.
Duchenne gene therapy delivers an engineered micro-dystrophin gene by adeno-associated virus, aiming to supply a shortened version of what the mutation removes. Exon-skipping drugs pursue the same goal differently, coaxing cells to make a truncated dystrophin. Both classes were cleared largely on how much protein they produce, rather than on demonstrated functional gains.
That distinction defines the whole field. Protein in a muscle biopsy is a biomarker; walking, breathing, and survival are the outcomes families care about. Whether the first reliably predicts the second is unresolved, and it shapes how every result below should be read.
Current State of Knowledge
Four exon-skipping drugs and one gene therapy have reached the US market for Duchenne muscular dystrophy, each cleared through the accelerated-approval pathway on the strength of dystrophin or micro-dystrophin expression. The table below summarizes the pivotal evidence, with every sample size, effect estimate, and citation checked against a primary source.
The four exon-skipping drugs — eteplirsen, golodirsen, viltolarsen, and casimersen — were approved between 2016 and 2021, each for a specific amenable mutation and each on dystrophin production. Delandistrogene moxeparvovec, the first gene therapy, followed in 2023, with its indication later broadened and then narrowed. All arrived through accelerated approval, a pathway that permits clearance on a surrogate endpoint reasonably likely to predict benefit, on the condition that confirmatory trials follow.
| Study / therapy | Design | N | Population | Intervention | Key result |
|---|---|---|---|---|---|
| EMBARK Delandistrogene moxeparvovec (gene therapy) | Phase 3, randomized, double-blind, placebo-controlled | 125 (63 vs 62) | Ambulatory boys, 4 to <8 y | Single IV dose, 1.33 × 10¹⁴ vg/kg | Micro-dystrophin expression maintained; primary NSAA change not significant (2.6 vs 1.9). Time to rise favored treatment: −0.64 s (95% CI −1.06 to −0.23) |
| Viltolarsen phase 2 Exon 53 skipping | Randomized, placebo-controlled 4-wk period, then open-label | 16 | Ambulatory boys, 4 to 9 y, exon 53 | 40 or 80 mg/kg IV weekly | 88% reached dystrophin >3% of normal; 6-minute walk +28.9 m vs −65.3 m in matched natural-history controls at week 25 |
| Golodirsen (SKIP-NMD) Exon 53 skipping | Phase 1/2: randomized Part 1 (n=8 vs 4), 168-wk open-label Part 2 | 25 treated (23 completed) | Ambulatory boys, exon 53 | 30 mg/kg IV weekly | Dystrophin +16.0-fold (P<0.001); 3-yr 6-minute walk change −99.0 m vs −181.4 m in external controls (P=0.067, not significant) |
| Eteplirsen (study 201/202) Exon 51 skipping | Randomized 24-wk study plus open-label extension | 12 | Ambulatory boys, exon 51 | 30 or 50 mg/kg IV weekly | Confirmed exon-51 skipping; de novo dystrophin ~0.9% of normal (basis for 2016 accelerated approval) |
| Exon-skipping meta-analysis Pooled RCT evidence | Systematic review and meta-analysis of 5 double-blind RCTs | 322 | DMD, various mutations | Eteplirsen / drisapersen vs placebo | No clear pooled benefit on 6-minute walk or North Star assessment; evidence judged insufficient to support clinical use |
Across these studies a pattern emerges. Protein restoration is consistent and statistically robust. Functional benefit is far less certain: the one placebo-controlled gene-therapy trial missed its primary motor endpoint, and the pooled randomized evidence for exon skipping showed no clear effect on walking.
What We Know
Dystrophin restoration is the most reproducible finding in the field. Golodirsen raised dystrophin roughly 16-fold over baseline; viltolarsen pushed most treated boys above 3% of normal; delandistrogene moxeparvovec produced micro-dystrophin with correct membrane localization that persisted for at least two years.
Signals of possible functional benefit exist, but they come mainly from comparisons with external natural-history cohorts rather than randomized controls. In EMBARK, several timed tests numerically favored the gene therapy, and a prespecified composite analysis across six functional measures reached significance (P=0.0044).
Individual secondary measures in EMBARK moved in the same direction. The 10-meter walk-or-run and the time to ascend four steps both favored treatment, though neither reached statistical significance on its own. A post-hoc analysis found fewer treated boys crossing a five-second rise time, a threshold linked to imminent loss of walking.
A two-year analysis added another layer. Compared with an external control group, treated boys showed statistically better scores on the North Star assessment, time to rise, and the 10-meter walk. Because that comparison is not the randomized contrast, it strengthens the signal without settling the question of true efficacy.
Read the design, not just the direction. Golodirsen’s three-year data showed less walking decline than mutation-matched controls, but the difference was not statistically significant (6-minute walk change −99.0 vs −181.4 m, P=0.067). Loss of ambulation was numerically lower (9% vs 26%, P=0.21). These are associations from an external-control comparison, not proof of a treatment effect.
Safety of the underlying mechanisms is now reasonably well characterized. Weekly antisense infusions have been generally well tolerated across programs. The single-dose AAV gene therapy, by contrast, carries the more serious risk profile detailed below, which has reshaped how it is used.
In EMBARK itself, treatment-related serious adverse events occurred in a minority of boys, with no deaths during the trial, and most events resolved. The gravest signals emerged later, in wider clinical use: two non-ambulatory boys died of acute liver failure, and a further serious case involved clotting in the mesenteric vein with bowel injury. These events drove the regulatory changes described below.
What Remains Uncertain
The open questions are not peripheral. They concern whether the entire regulatory rationale for these therapies holds, and they fall into four groups.
Does the biomarker predict benefit?
This is the crux. Disease severity in dystrophinopathy depends on both the quantity and the quality of dystrophin, and protein size alone does not determine phenotype. Patients with under 5% of normal dystrophin usually have severe disease, while 5–10% is associated with an intermediate course, yet the exact level of drug-induced protein that yields clinical benefit is unknown.
The engineered micro-dystrophin delivered by gene therapy is a truncated construct whose function differs from the full-length protein. A rise on a Western blot therefore does not automatically translate into proportional muscle protection.
Historical experience underlines the caution. The exon-skipping drugs restore only a small fraction of normal dystrophin, often around or below one percent, yet were approved on that biochemical change alone. Whether such modest, truncated protein meaningfully alters a relentless degenerative process is precisely what a validated surrogate would need to show, and what the current evidence has not.
Clinical pearl. A statistically significant rise in dystrophin answers the question “is the drug doing something biologically?” It does not answer “will this child walk, breathe, or live longer?” Keep those two questions separate when interpreting any Duchenne gene therapy result.
Are the control groups sound?
Most trials are small, reflecting a rare disease, and several lean on external or historical controls. In the golodirsen program the untreated arm included milder genotypes and was not, by protocol, a valid efficacy comparator. EMBARK’s more favorable two-year readout also rests on an external-control comparison rather than its randomized design, which limits how firmly benefit can be inferred.
The confirmatory record compounds the concern. When viltolarsen’s approval was tested in the randomized RACER53 trial, it showed no significant difference from placebo on its primary motor endpoint at 48 weeks. Eteplirsen’s larger phase 3 study, PROMOVI, enrolled an untreated comparison group whose different genotypes and high dropout made it unusable as a control, leaving the drug’s functional effect unresolved years after approval.
How durable are the effects, and do they reach hard outcomes?
Whether a single AAV dose sustains micro-dystrophin for years or decades is not established, and pre-existing immunity to AAV generally precludes re-dosing. Effects on the outcomes that matter most, including time to loss of ambulation, respiratory and cardiac function, and survival, remain unproven in randomized trials.
The economics sharpen the stakes. Gene therapy is among the most expensive treatments ever marketed, and it can generally be given only once. A decision made under today’s uncertainty cannot easily be revisited if the durability or benefit later turns out to be smaller than hoped.
What does the regulatory record show?
The uncertainty is not merely academic. During review of delandistrogene moxeparvovec, the FDA’s own clinical, pharmacology, and statistics teams concluded that micro-dystrophin expression was insufficient as a surrogate reasonably likely to predict clinical benefit and recommended against approval. That assessment was overridden at the center-director level, and confirmatory data were required. That confirmatory step is exactly where the field now sits: the biology is accepted, the clinical payoff is still being tested, and the two must not be conflated.
Research Priorities for Duchenne Gene Therapy
The evidence gaps point to a clear agenda for the studies most likely to change practice:
- Surrogate validation. Formally test whether micro-dystrophin and dystrophin levels correlate with, and predict, functional and survival outcomes, rather than assuming the link.
- Adequately powered randomized trials. Use placebo or delayed-treatment controls with prespecified functional primary endpoints, sized to detect clinically meaningful differences.
- Standardized quantification. Adopt reproducible dystrophin measurement, such as mass spectrometry, and agree on a clinical-benefit threshold for interpreting protein change.
- Long-term registries. Track durability, hepatic and immune safety, and ambulation, respiratory, and cardiac endpoints across years, not weeks.
- Responder and risk stratification. Identify biomarkers that predict who benefits and who is at highest risk of serious harm, including hepatotoxicity.
Quality and Consistency of the Evidence
Certainty differs sharply by outcome. Rated by strength and consistency of the underlying data:
- Protein restoration — strong and consistent. Dystrophin and micro-dystrophin expression rise reproducibly across randomized and open-label studies with statistically robust effect sizes.
- Motor stabilization versus external controls — moderate and mixed. The direction of effect is repeatedly favorable, but comparisons are confounded by genotype and natural-history variability.
- Benefit on randomized functional endpoints — low. The pivotal gene-therapy trial and a confirmatory exon-53 trial both missed their primary motor endpoints, and pooled RCT data were null.
- Long-term ambulation, respiratory, cardiac, and survival outcomes — insufficient. No randomized evidence yet confirms effects on these endpoints.
- Safety — characterized but serious for gene therapy. Antisense agents are generally well tolerated; the AAV gene therapy now carries a boxed warning for fatal acute liver failure.
What the Evidence Does Not Show
Precision about the limits of the evidence protects both clinicians and families from over-reading encouraging headlines. Several claims, common in promotional and lay coverage, go beyond what the current data can support:
- That raising dystrophin or micro-dystrophin has been proven to deliver clinical benefit — the protein remains a surrogate, not a validated outcome.
- That delandistrogene moxeparvovec improves North Star scores compared with placebo — the EMBARK primary endpoint was not met.
- That any one agent is superior to another — no head-to-head randomized comparisons exist.
- That these therapies extend survival or preserve respiratory or cardiac function — such outcomes are unproven in randomized trials.
- That favorable external-control comparisons establish efficacy — genotype mismatch and cohort variability leave them hypothesis-generating.
Practical Implications
None of this uncertainty argues for therapeutic nihilism; families facing a fatal disease reasonably want to act. It argues instead for honesty about what is known. Framed as what the evidence supports rather than as directives, five considerations follow for clinicians and families:
- Treat protein change as a biomarker, not an outcome. A rise in dystrophin confirms the mechanism is engaging; it does not, on its own, demonstrate that a child will walk longer.
- Distinguish randomized from external-control results when counseling. The most favorable numbers usually come from historical comparisons, while the placebo-controlled data are more modest and, for the primary endpoint, negative.
- Screen and monitor for hepatotoxicity. The November 2025 boxed warning and narrowed indication (ambulatory patients aged 4 and older) followed reports of fatal acute liver failure; the reported cases showed markedly raised transaminases with hospitalization within two months of infusion.
- Keep corticosteroids and multidisciplinary care central. These remain the evidence-based foundation and are not replaced by molecular therapies.
- Ground the decision in transparent, individualized discussion. Weigh reliable biomarker change against unconfirmed efficacy, serious potential harms, and cost, and document informed consent accordingly.
Safety note. Delandistrogene moxeparvovec carries a boxed warning for serious liver injury and acute liver failure, including fatal outcomes. Its indication no longer includes non-ambulatory patients. Verify current prescribing information and eligibility before any treatment discussion.
Evidence Grade and Bottom Line
Evidence grade: High for the biomarker effect (reliable protein restoration); low to moderate for clinical benefit, which randomized trials have not yet confirmed.
- Duchenne gene therapy reliably restores micro-dystrophin, but has not yet been shown to change the clinical course in a randomized trial.
- The surrogate-endpoint question — whether protein restoration predicts meaningful benefit — is the unresolved core of the field.
- Serious safety risks, including fatal acute liver failure, now carry a boxed warning, and use is restricted to ambulatory patients aged 4 and older.
- Shared decision-making, hepatic monitoring, and continued corticosteroid and supportive care are warranted while confirmatory evidence matures.
Article Information and References
- Shimizu-Motohashi Y, Murakami T, Kimura E, et al. Exon skipping for Duchenne muscular dystrophy: a systematic review and meta-analysis. Orphanet J Rare Dis. 2018;13:93. DOI: https://doi.org/10.1186/s13023-018-0834-2
- Verhaart IEC, Aartsma-Rus A. Therapeutic developments for Duchenne muscular dystrophy. Nat Rev Neurol. 2019;15(7):373-386. DOI: https://doi.org/10.1038/s41582-019-0203-3
- Mendell JR, Muntoni F, McDonald CM, et al. AAV gene therapy for Duchenne muscular dystrophy: the EMBARK phase 3 randomized trial. Nat Med. 2025;31(1):332-341. DOI: https://doi.org/10.1038/s41591-024-03304-z
- Clemens PR, Rao VK, Connolly AM, et al. Safety, tolerability, and efficacy of viltolarsen in boys with Duchenne muscular dystrophy amenable to exon 53 skipping: a phase 2 randomized clinical trial. JAMA Neurol. 2020;77(8):982-991. DOI: https://doi.org/10.1001/jamaneurol.2020.1264
- Servais L, Mercuri E, Straub V, et al. Long-term safety and efficacy data of golodirsen in ambulatory patients with Duchenne muscular dystrophy amenable to exon 53 skipping: a first-in-human, multicenter, two-part, open-label, phase 1/2 trial. Nucleic Acid Ther. 2022;32(1):29-39. DOI: https://doi.org/10.1089/nat.2021.0043
- Frank DE, Schnell FJ, Akana C, et al. Increased dystrophin production with golodirsen in patients with Duchenne muscular dystrophy. Neurology. 2020;94(21):e2270-e2282. DOI: https://doi.org/10.1212/WNL.0000000000009233
- Charleston JS, Schnell FJ, Dworzak J, et al. Eteplirsen treatment for Duchenne muscular dystrophy: exon skipping and dystrophin production. Neurology. 2018;90(24):e2146-e2154. DOI: https://doi.org/10.1212/WNL.0000000000005680
- McDonald CM, Elkins JS, Dharmarajan S, et al. Caregiver global impression observations from EMBARK: a phase 3 study evaluating delandistrogene moxeparvovec in ambulatory patients with Duchenne muscular dystrophy. Neurol Ther. 2025;14(1):211-225. DOI: https://doi.org/10.1007/s40120-024-00685-8