
Ectopic Pregnancy Management: 3 Core Approaches Compared
Matching stable and unstable patients to expectant care, single- or multi-dose methotrexate, or laparoscopic surgery — and reading the hCG signals that decide.
One-Minute Takeaway
- Ectopic pregnancy management follows three evidence-based routes — expectant, medical, and surgical — chosen mainly by hemodynamic stability, serum hCG, and ultrasound findings; randomized trials and meta-analyses, the strongest evidence here, guide the choice.
- Methotrexate fits stable, unruptured cases without contraindications; failure climbs once initial hCG passes 5,000 mIU/mL (OR 5.45, 95% CI 3.04–9.78).
- Pooled medical success is roughly 89%; single-dose is more convenient but has shown higher failure than multi-dose in older pooled data (adjusted OR 4.74, 95% CI 1.77–12.62).
- Against laparoscopic salpingostomy, methotrexate carries a higher failure rate (OR 1.58, 95% CI 1.06–2.36), driven by the single-dose subgroup.
- Salpingotomy does not improve fertility over salpingectomy when the other tube is healthy, and raises persistent-trophoblast risk (RR 15.0, 95% CI 2.0–113.4).
Why Ectopic Pregnancy Management Matters
Ectopic pregnancy occurs in roughly 1–2% of pregnancies, and the fallopian tube is the site in about 95% of cases. Despite earlier diagnosis, it remains the leading cause of first-trimester maternal death.
That combination — common enough to see regularly, lethal when missed — is what raises the stakes on the management decision. The same patient can be a candidate for watchful monitoring or for emergency surgery depending on a handful of findings measured over hours.
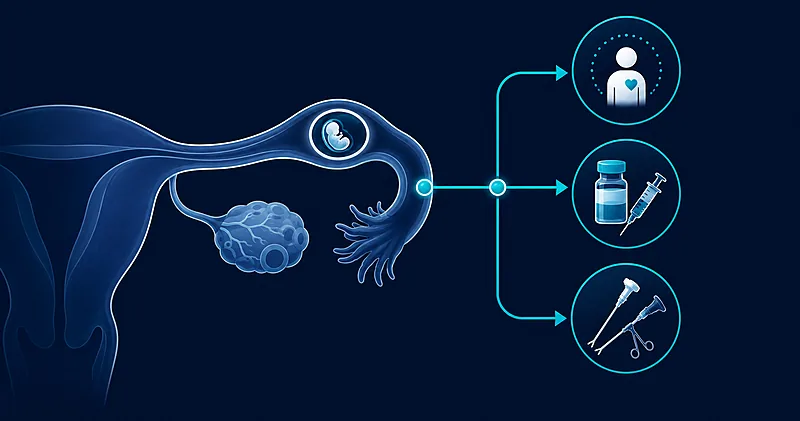
Modern practice offers three routes: expectant, medical, and surgical. Choosing well protects the tube and future fertility when possible, while never trading safety for conservatism in an unstable patient.
The Clinical Problem in Ectopic Pregnancy Management
The first branch point is hemodynamic stability. An unstable patient, or one with signs of rupture or intraperitoneal bleeding, needs surgery — no laboratory value changes that.
For the stable patient, three inputs shape the choice: the serum hCG level and its trend, the transvaginal ultrasound appearance, and the presence of any contraindication to methotrexate. Each narrows the safe options.
Serum hCG also anchors diagnosis. The American College of Obstetricians and Gynecologists recommends a conservative discriminatory level of 3,500 mIU/mL — the value above which a normal intrauterine pregnancy is expected to be visible on transvaginal ultrasound. The threshold was deliberately set high to reduce the risk of interrupting a viable intrauterine pregnancy that is simply early.
Clinical pearl. A single hCG value cannot distinguish a viable early intrauterine pregnancy from an ectopic. The discriminatory level guides when to expect ultrasound findings; the trend over 48 hours, alongside imaging, drives the management decision.
Available Approaches
The three routes differ in who they suit, how they are monitored, and what they cost in follow-up and side effects. The evidence table below summarizes the comparative studies that inform each, drawn from randomized trials and meta-analyses.
Read across the routes rather than in isolation: the same low-hCG, asymptomatic patient may be eligible for expectant management, methotrexate, or surgery, and the trials suggest the differences between them can be narrower than intuition implies.
| Study / Source | Design | N | Population / comparison | Key result (95% CI) | Tier |
|---|---|---|---|---|---|
| Menon 2007 | Systematic review (5 cohort studies) | 503 | Single-dose methotrexate, stratified by initial hCG | Failure sharply higher at hCG >5,000 vs <5,000 mIU/mL: OR 5.45 (3.04–9.78) | V |
| Barnhart 2003 | Meta-analysis (26 studies) | 1,327 | Single-dose vs multi-dose methotrexate | Overall success ~89%; single-dose higher failure, adjusted OR 4.74 (1.77–12.62); fewer side effects OR 0.44 (0.31–0.63) | V |
| Solangon 2023 | Individual-participant meta-analysis (2 RCTs) | 153 | Single-dose methotrexate vs expectant, hCG <2,000 | Success 79.3% vs 68.6%: RR 1.16 (0.95–1.40), not significant; fewer surgeries with methotrexate (9.8% vs 18.6%) | V |
| Liao 2025 | Conventional + network meta-analysis (8 trials) | 677 | Methotrexate vs laparoscopic salpingostomy | Methotrexate higher failure OR 1.58 (1.06–2.36); single-dose vs salpingostomy OR 2.04 (1.20–3.47); ≥2 doses OR 1.13 (0.62–2.07), not significant | V |
| ESEP (Mol 2014) | Multicentre RCT | 446 | Salpingotomy vs salpingectomy, healthy contralateral tube | Ongoing pregnancy not significantly different; persistent trophoblast 7% vs <1%, RR 15.0 (2.0–113.4) | V |
| Hajenius 2007 (Cochrane) | Systematic review of RCTs | Pooled | Methotrexate vs laparoscopic salpingostomy | Single-dose methotrexate significantly less effective than salpingostomy; multi-dose comparable in outcomes but poorer quality of life and higher cost | V |
Expectant Management
Expectant management means close monitoring without intervention, letting an early, self-limiting ectopic resolve on its own. It applies to a narrow group: clinically stable, asymptomatic patients with a low and falling or plateauing hCG.
Randomized data support it as a genuine alternative to methotrexate in low-hCG disease. In an individual-participant meta-analysis of two trials, uneventful resolution reached 68.6% with expectant care versus 79.3% with single-dose methotrexate — a difference that was not statistically significant (RR 1.16, 95% CI 0.95–1.40). Rates of eventual surgery did not differ significantly either.
The trade-off is uncertainty and vigilance. Expectant management avoids drug toxicity but demands reliable follow-up and clear rupture precautions, because the risk persists until hCG is undetectable.
Methotrexate Therapy
Methotrexate, a folate antagonist that halts trophoblast proliferation, is the medical option. It suits hemodynamically stable patients with an unruptured ectopic and no contraindication to the drug.
Who qualifies — and who does not
The ACOG contraindication framework separates absolute from relative bars. Absolute contraindications include a ruptured ectopic, hemodynamic instability, inability to attend follow-up, breastfeeding, immunodeficiency, moderate-to-severe anemia, leukopenia or thrombocytopenia, active pulmonary or peptic ulcer disease, clinically significant hepatic or renal dysfunction, and methotrexate sensitivity.
Relative contraindications flag lower expected success: embryonic cardiac activity, an ectopic mass larger than 4 cm on ultrasound, and a high initial hCG. A level above 5,000 mIU/mL is the commonly cited relative threshold.
hCG thresholds and success
Initial hCG is the strongest single predictor of medical success. A systematic review of five cohorts found failure rose sharply above 5,000 mIU/mL, with the odds of failure more than five times higher than below that level (OR 5.45, 95% CI 3.04–9.78).
Success is not defined at treatment but confirmed on follow-up. In the single-dose protocol, hCG is measured on days 4 and 7; a fall of at least 15% between those days signals response, and a smaller fall prompts a repeat dose.
Single-dose, two-dose, and multi-dose protocols
Three regimens exist. Single-dose gives 50 mg/m² intramuscularly with the day 4 and 7 check. Multi-dose alternates methotrexate 1 mg/kg with leucovorin rescue for up to four doses. The two-dose protocol splits the difference, giving doses on days 0 and 4.
Pooled data put overall medical success near 89%. Older pooled evidence associated single-dose with higher failure than multi-dose (adjusted OR 4.74, 95% CI 1.77–12.62), though single-dose caused fewer side effects (OR 0.44, 95% CI 0.31–0.63). A later meta-analysis found the two-dose protocol superior to single-dose for success, and head-to-head trials suggest two-dose resolves hCG faster while remaining well tolerated.
Clinical pearl. The choice among protocols is a trade between convenience and potency. Single-dose minimizes injections and monitoring; the two-dose and multi-dose regimens push success higher, an advantage that matters most when the initial hCG or adnexal mass sits at the upper end of eligibility.
Surgical Management
Surgery is definitive and, for some patients, mandatory. A hemodynamically unstable patient, a ruptured ectopic, or signs of significant intraperitoneal bleeding call for prompt operative management regardless of hCG.
Surgery is also the route when methotrexate is contraindicated or has failed, and it is a reasonable first choice for stable patients who prefer a single definitive procedure. Laparoscopy is preferred over laparotomy in the stable patient.
Salpingectomy versus salpingotomy
The operative choice is between removing the affected tube (salpingectomy) and opening it to evacuate the pregnancy while preserving it (salpingotomy, or salpingostomy). Tube preservation was long assumed to protect fertility.
The ESEP randomized trial tested that assumption in 446 women with a healthy contralateral tube. Salpingotomy did not significantly improve the rate of ongoing pregnancy by natural conception compared with salpingectomy. It did raise the risk of persistent trophoblast markedly (7% vs under 1%; RR 15.0, 95% CI 2.0–113.4), and one in five salpingotomy procedures was converted to salpingectomy during surgery for persistent bleeding.
The reading is pragmatic. With a normal opposite tube, salpingectomy is a reasonable default; salpingotomy is reserved chiefly for women whose contralateral tube is absent or damaged and who wish to preserve fertility.
Comparative Analysis
Across the routes, the trials sketch a consistent picture. In low-hCG disease, expectant management and methotrexate are close enough that neither dominates the other on success or eventual surgery.
Compared with laparoscopic salpingostomy, methotrexate carries a higher overall failure rate (OR 1.58, 95% CI 1.06–2.36). Subgroup analysis locates that difference in the single-dose regimen (OR 2.04, 95% CI 1.20–3.47); two or more doses were not significantly different from surgery (OR 1.13, 95% CI 0.62–2.07). The Cochrane review reached the same conclusion: single-dose methotrexate underperforms salpingostomy, while multi-dose approaches it at the cost of poorer quality of life and higher spending.
The surgical decision then turns on tube preservation, where ESEP shows equivalent fertility but higher persistent-trophoblast risk with salpingotomy. Network data also suggest that adding methotrexate after salpingostomy lowers the failure rate versus salpingostomy alone (OR 0.11, 95% CI 0.03–0.48), though at the price of multimodal side effects.
Quality and Consistency of the Evidence
The evidence base spans several designs, and its strength varies by question. The rating below reflects study design, consistency across trials, and the width of the confidence intervals.
- Surgical technique and fertility (high). The ESEP randomized trial directly answers salpingotomy versus salpingectomy; its fertility finding is consistent and well powered, though the persistent-trophoblast estimate has a wide interval.
- hCG as a predictor of medical success (high). Multiple cohorts and a systematic review agree that failure rises with initial hCG, with a consistent inflection above 5,000 mIU/mL.
- Methotrexate versus surgery (moderate). Meta-analyses of randomized and observational studies converge, but individual trials are modest in size and the single-dose signal drives the pooled effect.
- Methotrexate versus expectant management (moderate). Randomized trials are consistent but small; the meta-analysis pooled only 153 participants and confidence intervals cross no effect.
- Optimal methotrexate protocol (low to moderate). Older pooled data favor multi-dose, newer analyses favor two-dose, and head-to-head trials disagree on statistical significance — a genuine unresolved question.
What the Evidence Does Not Show
Open questions. The comparative trials leave several gaps that current evidence does not close.
- The single best methotrexate protocol is unsettled. Whether two-dose should replace single-dose as default, and for which hCG range, has not been resolved by concordant randomized data.
- Subgroup tailoring is underpowered. The methotrexate-versus-expectant trials were too small to identify which patients gain most from either route within the low-hCG band.
- Upper-hCG medical management is thin. Evidence guiding methotrexate above roughly 5,000 mIU/mL rests largely on observational data, where failure and later surgery are common.
- Long-term fertility beyond the index pregnancy is limited. Most trials report the next conception; durable reproductive outcomes across further pregnancies are less well characterized.
Practical Implications
The evidence supports a stepwise reading rather than a single algorithm. Stability comes first: instability, rupture, or significant bleeding points to surgery, and no hCG value overrides that.
For the stable patient, the hCG level and trend, ultrasound appearance, and methotrexate contraindications define the safe set. Low, falling hCG opens the door to expectant or medical management with comparable expected success; a level above 5,000 mIU/mL, embryonic cardiac activity, or a mass over 4 cm shifts the balance toward surgery.
Cost and quality of life inform the remaining choice. Laparoscopic salpingostomy is generally the most cost-effective route; single-dose methotrexate is cost-effective mainly below about 1,500 mIU/mL and multi-dose below about 3,000 mIU/mL, with methotrexate becoming more expensive as hCG rises. When surgery is chosen and the opposite tube is healthy, salpingectomy is a reasonable default.
Evidence Grade and Bottom Line
Overall evidence grade: moderate to high. The surgical technique question and the role of hCG rest on strong data; protocol selection and fine subgroup tailoring remain less certain.
- Triage on hemodynamic stability first; an unstable or ruptured ectopic is a surgical emergency.
- Reserve methotrexate for stable, unruptured patients without contraindications, and expect success to fall as initial hCG rises past 5,000 mIU/mL.
- Single-dose is convenient; two-dose or multi-dose regimens raise success and may suit higher-hCG candidates.
- In low-hCG disease, expectant management is a reasonable alternative to methotrexate with comparable outcomes.
- With a healthy contralateral tube, salpingectomy preserves fertility as well as salpingotomy while avoiding persistent-trophoblast risk.
Article Information and References
- Solangon SA, Van Wely M, Van Mello N, Mol BW, Ross JA, Jurkovic D. Methotrexate vs expectant management for treatment of tubal ectopic pregnancy: an individual participant data meta-analysis. Acta Obstet Gynecol Scand. 2023;102(9):1159–1175. DOI: https://doi.org/10.1111/aogs.14617
- Liao J, Lin Y, Long Y. Comparison of laparoscopic tubal-preserving surgical management versus methotrexate therapy for tubal pregnancy: a conventional and network meta-analysis. PLoS One. 2025;20(9):e0332169. DOI: https://doi.org/10.1371/journal.pone.0332169
- Barnhart KT, Gosman G, Ashby R, Sammel M. The medical management of ectopic pregnancy: a meta-analysis comparing “single dose” and “multidose” regimens. Obstet Gynecol. 2003;101(4):778–784. DOI: https://doi.org/10.1016/s0029-7844(02)03158-7
- Menon S, Colins J, Barnhart KT. Establishing a human chorionic gonadotropin cutoff to guide methotrexate treatment of ectopic pregnancy: a systematic review. Fertil Steril. 2007;87(3):481–484. DOI: https://doi.org/10.1016/j.fertnstert.2006.10.007
- Hajenius PJ, Mol F, Mol BW, Bossuyt PM, Ankum WM, van der Veen F. Interventions for tubal ectopic pregnancy. Cochrane Database Syst Rev. 2007;(1):CD000324. DOI: https://doi.org/10.1002/14651858.CD000324.pub2
- Alur-Gupta S, Cooney LG, Senapati S, Sammel MD, Barnhart KT. Two-dose versus single-dose methotrexate for treatment of ectopic pregnancy: a meta-analysis. Am J Obstet Gynecol. 2019;221(2):95–108.e2. DOI: https://doi.org/10.1016/j.ajog.2019.01.002
- Mol F, van Mello NM, Strandell A, et al. Salpingotomy versus salpingectomy in women with tubal pregnancy (ESEP study): an open-label, multicentre, randomised controlled trial. Lancet. 2014;383(9927):1483–1489. DOI: https://doi.org/10.1016/S0140-6736(14)60123-9
- van Mello NM, Mol F, Verhoeve HR, et al. Methotrexate or expectant management in women with an ectopic pregnancy or pregnancy of unknown location and low serum hCG concentrations? A randomized comparison. Hum Reprod. 2013;28(1):60–67. DOI: https://doi.org/10.1093/humrep/des373
- Jurkovic D, Memtsa M, Sawyer E, et al. Single-dose systemic methotrexate vs expectant management for treatment of tubal ectopic pregnancy: a placebo-controlled randomized trial. Ultrasound Obstet Gynecol. 2017;49(2):171–176. DOI: https://doi.org/10.1002/uog.17329
- Sowter MC, Farquhar CM, Petrie KJ, Gudex G. A randomised trial comparing single dose systemic methotrexate and laparoscopic surgery for the treatment of unruptured tubal pregnancy. BJOG. 2001;108(2):192–203. DOI: https://doi.org/10.1111/j.1471-0528.2001.00038.x
- Lipscomb GH, McCord ML, Stovall TG, Huff G, Portera SG, Ling FW. Predictors of success of methotrexate treatment in women with tubal ectopic pregnancies. N Engl J Med. 1999;341(26):1974–1978. DOI: https://doi.org/10.1056/NEJM199912233412604
- Committee on Practice Bulletins—Gynecology. ACOG Practice Bulletin No. 193: Tubal Ectopic Pregnancy. Obstet Gynecol. 2018;131(3):e91–e103. DOI: https://doi.org/10.1097/AOG.0000000000002560