
GERD Primary Care Management: Stepwise Therapy and PPI Stewardship
Clinical Practice Update — Diagnosis, Stepwise Acid Suppression, Red Flags, and Safe Deprescribing in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Stepwise GERD primary care management, red flag triage, and proton pump inhibitor stewardship
- Target Audience
- Family physicians, general practitioners, primary care nurses, community pharmacists, residents
- Setting
- Primary care, family medicine clinics, community pharmacy
- Source Evidence
- •ACG Clinical Guideline on GERD Diagnosis and Management (2022)
- •NICE Guideline NG184 — Dyspepsia and GORD in Adults
- •AGA Clinical Practice Update on PPI Deprescribing (2022)
- •AGA Clinical Practice Update on Refractory Reflux (2020)
Key Clinical Takeaways
Confident GERD primary care management rests on three moves: recognise who can be treated empirically, escalate acid suppression in deliberate steps, and step back down once symptoms settle. The points below turn that approach into rules you can apply in a single consultation.
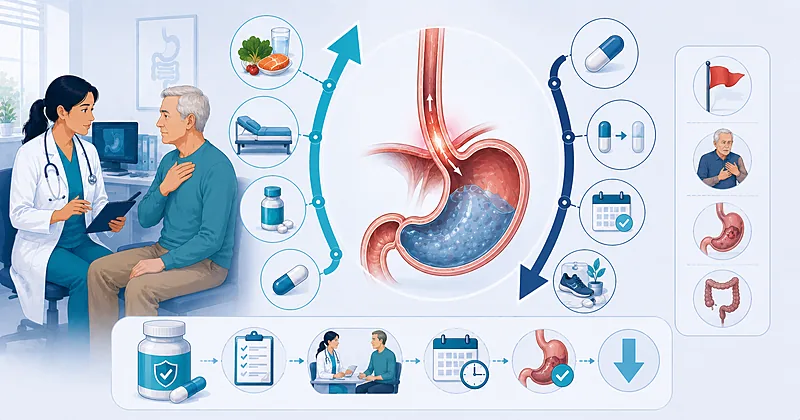
- 1Treat typical heartburn and regurgitation in adults under 60 with empiric PPI therapy rather than upfront endoscopy → Starting Treatment
- 2Refer urgently for endoscopy when alarm symptoms are present — dysphagia, weight loss, bleeding, or anaemia → Recognising Red Flags
- 3Begin with a standard-dose PPI once daily for 8 weeks; this is the cornerstone of stepwise therapy → Stepwise Escalation
- 4Take the PPI 30 to 60 minutes before the first meal — timing failure is the commonest cause of apparent non-response → Stepwise Escalation
- 5Once symptoms are controlled, step down to the lowest effective dose or on-demand use rather than continuing indefinitely → Stewardship and Step-Down
- 6Warn patients about rebound acid hypersecretion when stopping a long-term PPI, and taper rather than stop abruptly → Stewardship and Step-Down
- 7Reserve twice-daily dosing for confirmed erosive disease or genuine partial response after timing is optimised → Stepwise Escalation
- 8Continue long-term acid suppression where it is genuinely indicated — do not deprescribe in confirmed Barrett esophagus or severe esophagitis → Stewardship and Step-Down
- 9Reassess every patient on a repeat PPI prescription at least annually to confirm the indication still holds → Monitoring
Who to Treat Empirically in GERD Primary Care Management
The first decision in GERD primary care management is whether a patient can be treated on the strength of their symptoms alone. For most adults with classic heartburn and acid regurgitation and no concerning features, the answer is yes, and an empiric trial of acid suppression is both diagnostic and therapeutic.
Initiate an 8-week empiric trial of a once-daily proton pump inhibitor for adults under 60 with typical heartburn and regurgitation and no alarm features. A clear response supports the diagnosis without further testing.
Strong Rec High Evidence ACG 2022 NICE NG184Advise weight loss for patients above a healthy weight and head-of-bed elevation for those with night-time symptoms. These lifestyle modification measures carry the strongest evidence of the behavioural options and complement drug therapy.
Moderate Rec Moderate Evidence ACG 2022Avoid routine use of blanket dietary elimination. Counsel patients to cut only the specific triggers they can identify for themselves rather than imposing broad restrictions that rarely change outcomes.
Conditional Rec Low Evidence ACG 2022Recognising Red Flags Before Empiric Therapy
Red flags are the safety net of GERD primary care management. They identify the minority of patients in whom reflux symptoms may signal malignancy, stricture, or significant bleeding, and they override the empiric pathway entirely.
Refer urgently for upper endoscopy any adult with new dysphagia, unintentional weight loss, gastrointestinal bleeding, iron-deficiency anaemia, or persistent vomiting, regardless of age.
Strong Rec High Evidence ACG 2022 NICE NG184Evaluate for endoscopy in patients over 60 presenting with new reflux symptoms, and in anyone with a strong family history of upper gastrointestinal cancer, before committing to long-term empiric treatment.
Moderate Rec Moderate Evidence NICE NG184Red Flags at a Glance
| Warning Feature | Why It Matters | Action in Primary Care | Common Pitfall |
|---|---|---|---|
| Dysphagia | May indicate stricture or esophageal cancer | Urgent endoscopy referral | Dismissing it as “food sticking” without acting |
| Weight loss | Concern for malignancy | Urgent endoscopy referral | Attributing it to reduced appetite from reflux |
| GI bleeding | Erosive disease, ulcer, or tumour | Urgent referral; assess haemodynamics | Overlooking melaena reported only on direct questioning |
| Anaemia | Suggests chronic occult blood loss | Endoscopy and iron studies | Treating iron deficiency without finding the source |
| Age over 60 with new symptoms | Higher baseline cancer risk | Consider endoscopy before long-term therapy | Defaulting straight to an open-ended PPI |
Stepwise Escalation of Acid Suppression
Stepwise therapy means starting at the dose most likely to work, confirming the patient is using it correctly, and only then climbing higher. Most apparent treatment failures resolve when dose timing and adherence are addressed before the dose itself is increased.
Counsel every patient to take their PPI 30 to 60 minutes before the first meal of the day. Acid suppression depends on the drug being present when meal-stimulated proton pumps are active.
Strong Rec Moderate Evidence ACG 2022Increase to twice-daily dosing only after confirming correct timing and full adherence, and only when symptoms are genuinely partially controlled rather than absent. Split the dose before breakfast and the evening meal.
Moderate Rec Moderate Evidence AGA 2020Refer to gastroenterology when typical symptoms persist despite optimised twice-daily therapy over 8 weeks. Refractory symptoms warrant endoscopy and, where available, reflux monitoring rather than further empiric dose increases.
Strong Rec Moderate Evidence AGA 2020Stepwise Therapy Ladder
| Step | What to Do | Check Before Climbing | Typical Duration |
|---|---|---|---|
| Step 1 | Lifestyle measures plus standard-dose PPI once daily before breakfast | Confirm the diagnosis fits and no red flags exist | 8 weeks |
| Step 2 | Reinforce timing and adherence; review the actual product taken | Is the dose truly taken before food, every day? | 2 weeks |
| Step 3 | Increase to twice-daily dosing for genuine partial response | Has timing already been optimised at Step 2? | 4 to 8 weeks |
| Step 4 | Refer for endoscopy and specialist assessment | Persisting symptoms after optimised twice-daily therapy | As scheduled |
Who Needs Investigation
Not every patient needs a scope, but a defined group benefits from looking before committing to indefinite treatment. Investigation also has a role where the diagnosis is in doubt or where infection may be driving symptoms.
Perform Helicobacter pylori testing in patients with reflux symptoms overlapping with dyspepsia, and treat where positive. Use a test that is not confounded by recent acid suppression, and pause PPIs beforehand where the test requires it.
Moderate Rec Moderate Evidence NICE NG184Reassess the working diagnosis when chest pain is the dominant symptom. Exclude cardiac causes first; reflux is a diagnosis of safety only once the heart has been cleared.
Strong Rec High Evidence ACG 2022Investigation is most useful in three situations: any patient with a red flag, an older patient with new symptoms, and a patient who has already failed optimised therapy. In each, the scope changes management rather than simply confirming what is already known.
PPI Stewardship and Step-Down
Stewardship is the half of GERD primary care management that is most often neglected. Many patients remain on a PPI for years after the original indication has passed, and the discipline of stepping down is as important as the discipline of starting.
Attempt proton pump inhibitor deprescribing in patients whose symptoms have been controlled and who have no ongoing indication for continued full-dose therapy. Step down to the lowest effective dose, then to on-demand use.
Strong Rec Moderate Evidence AGA 2022Counsel patients that stopping a long-term PPI can cause a temporary surge of acid symptoms over one to two weeks. Frame this as expected and self-limiting so a rebound flare is not misread as the original disease returning.
Moderate Rec Moderate Evidence AGA 2022Do not deprescribe in patients with confirmed Barrett esophagus, severe erosive esophagitis, or a documented bleeding ulcer history. In these groups continued acid suppression is the indication, not an overprescription.
Against High Evidence AGA 2022Document the specific indication and a planned review date whenever a PPI is started or renewed. A prescription without a recorded reason is the root of most inappropriate long-term use.
Strong Rec Low Evidence AGA 2022Continue or Deprescribe: A Decision Aid
| Patient Profile | Continue or Step Down | Practical Approach | Watch For |
|---|---|---|---|
| Symptoms resolved, no erosive disease | Step down then trial off | Halve dose for 2 weeks, then on-demand | Transient rebound symptoms |
| Confirmed Barrett esophagus | Continue indefinitely | Maintain effective dose, surveillance per plan | Lapses in surveillance scheduling |
| Severe erosive esophagitis | Continue maintenance | Lowest dose that keeps healing | Premature dose reduction |
| On PPI for unclear reason | Review and likely step down | Clarify history, attempt taper | Assuming the original reason was valid |
Clinical Decision Pathway
A practical, question-based approach to the patient presenting with reflux symptoms. Work through the questions in order.
Monitoring and Follow-Up
Follow-up keeps treatment proportionate over time. The single most valuable habit is a scheduled annual review of every long-term prescription to confirm the indication still holds.
| What to Review | When | What to Confirm | Common Pitfall |
|---|---|---|---|
| Initial response | After the 8-week trial | Symptoms controlled and ready to step down | Repeating the prescription without reviewing |
| Ongoing indication | At least annually | A clear, documented reason still applies | Auto-renewing repeat scripts indefinitely |
| Barrett esophagus surveillance | Per specialist schedule | Surveillance endoscopy booked and attended | Assuming the hospital is tracking it |
| Recurrent symptoms after stopping | 2 to 4 weeks after a trial off | True relapse versus transient rebound | Restarting full dose at the first twinge |
Evidence in Context
What the evidence supports, where the major frameworks align, and where their emphasis differs.
Where ACG and NICE Agree
Both frameworks endorse empiric acid suppression as the entry point for uncomplicated typical reflux, both treat alarm features as a mandate for endoscopy, and both push toward using the lowest dose that maintains symptom control rather than fixed indefinite therapy.
Where Their Emphasis Differs
Trial length and H. pylori: NICE foregrounds a structured initial course and active H. pylori testing within the dyspepsia pathway, while ACG places relatively more weight on confirming the diagnosis when response is incomplete. The practical destination is the same; the route emphasised differs.
The Case for Deprescribing
Dedicated practice updates on deprescribing make the case that many patients can reduce or stop therapy without losing control, provided those with a genuine maintenance indication are excluded and rebound is anticipated rather than misattributed.
Refractory Symptoms: Looking Beyond Dose
When symptoms persist on optimised therapy, the evidence favours objective assessment over reflexive dose escalation, since a meaningful share of these patients have an alternative driver rather than inadequately suppressed acid.
References
- 1.Katz PO, Dunbar KB, Schnoll-Sussman FH, et al. ACG Clinical Guideline for the Diagnosis and Management of Gastroesophageal Reflux Disease. Am J Gastroenterol. 2022;117(1):27–56. doi:10.14309/ajg.0000000000001538
- 2.National Institute for Health and Care Excellence. Gastro-oesophageal reflux disease and dyspepsia in adults: investigation and management. NICE Guideline NG184. 2019. nice.org.uk/guidance/ng184
- 3.Targownik LE, Fisher DA, Saini SD. AGA Clinical Practice Update on De-Prescribing of Proton Pump Inhibitors: Expert Review. Gastroenterology. 2022;162(4):1334–1342. doi:10.1053/j.gastro.2021.12.247
- 4.Gyawali CP, Fass R. Management of Gastroesophageal Reflux Disease. Gastroenterology. 2018;154(2):302–318. doi:10.1053/j.gastro.2017.07.049
How to Read the Evidence Tags
Every recommendation carries two tags for recommendation strength and evidence quality — Medaptly’s own simplified interpretations, with the source noted alongside.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |