
Acute Upper GI Bleeding: Risk Stratification and Management
Clinical Practice Update — Risk Scoring, Resuscitation, and Endoscopic Management in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Risk stratification and endoscopic management of acute upper GI bleeding in adults
- Target Audience
- Emergency physicians, hospitalists, gastroenterologists, internal medicine residents
- Setting
- Emergency department, hospital inpatient, intensive care
- Source Evidence
- •ACG Clinical Guideline: Upper GI and Ulcer Bleeding (2021)
- •ESGE Guideline: Diagnosis and Management of Nonvariceal UGIB (2021)
- •Baveno VII Consensus — Portal Hypertension and Variceal Bleeding (2022)
- •TRICC / Villanueva Restrictive Transfusion Trial (NEJM, 2013)
Key Clinical Takeaways
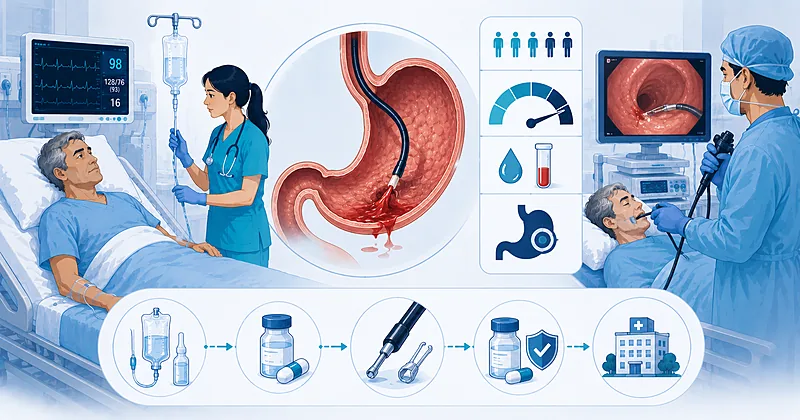
Effective acute upper GI bleeding management turns on three rapid judgments at the front door: resuscitate to a safe physiologic baseline, stratify risk with a validated score, and time endoscopy correctly. The points below distill current evidence into bedside rules you can apply from triage through definitive therapy.
- 1Calculate a Glasgow-Blatchford score on every patient at presentation — a score of 0 to 1 identifies those who can be safely managed as outpatients.
- 2Adopt a restrictive transfusion threshold, targeting hemoglobin near 7 g/dL in hemodynamically stable patients without active cardiac ischemia.
- 3Perform endoscopy within 24 hours of presentation for most hospitalized patients once resuscitation is underway.
- 4Do not delay endoscopy to the very early window (under 12 hours) for the sole purpose of improving outcomes in stable patients.
- 5When variceal bleeding is suspected, start a vasoactive drug and antibiotics before the scope reaches the patient.
- 6Treat only high-risk ulcer stigmata endoscopically; clean-based ulcers need neither hemostasis nor intensive monitoring.
- 7Give high-dose proton pump inhibitor therapy after endoscopic hemostasis of a high-risk ulcer to lower the rebleeding rate.
- 8For ulcer rebleeding after initial control, repeat endoscopy first; reserve angiographic embolization or surgery for endoscopic failure.
Risk Stratification in Acute Upper GI Bleeding
Risk stratification is the first decision that shapes everything downstream in acute upper GI bleeding: who goes home, who is admitted to a ward, and who needs critical care and urgent endoscopy. A validated score applied at the bedside outperforms unstructured clinical gestalt for identifying very-low-risk patients.
Two pre-endoscopic risk scores dominate practice. The Glasgow-Blatchford score uses only clinical and laboratory variables available at triage, making it ideal for the disposition decision. The Rockall score incorporates endoscopic findings and is better suited to estimating mortality after the procedure.
Calculate the Glasgow-Blatchford score at first contact for every adult with suspected acute upper GI bleeding. The score requires no endoscopic data and can be completed in the emergency department within minutes.
Strong Rec High Evidence ACG 2021 ESGE 2021Discharge for outpatient management patients with a Glasgow-Blatchford score of 0 to 1, provided there are no other reasons for admission and reliable follow-up exists. This group has a very low risk of needing intervention.
Strong Rec High Evidence ACG 2021Consider patients with a Glasgow-Blatchford score of 7 or higher as elevated risk for intervention, and prioritize them for inpatient admission and timely endoscopy.
Moderate Rec Moderate Evidence ESGE 2021Resuscitation and Transfusion Strategy
Resuscitation runs in parallel with risk stratification, not after it. The goal is to restore perfusion without over-transfusing, since a liberal strategy has been linked to worse outcomes in this setting.
Transfuse red cells using a restrictive transfusion threshold, aiming for a hemoglobin around 7 g/dL in stable patients. Allow a higher target near 8 g/dL when there is known cardiovascular disease or active ischemia.
Strong Rec High Evidence ACG 2021 Villanueva 2013Evaluate for coagulopathy and correct a markedly elevated INR, but do not let resuscitation of coagulation delay endoscopy in an actively bleeding patient. Aggressive correction to a normal INR is not required before the procedure.
Conditional Rec Moderate Evidence ESGE 2021Do not transfuse platelets routinely in a non-bleeding patient with a count above 50,000 solely because of antiplatelet use. Reserve platelet support for active bleeding with significant thrombocytopenia.
Against Low Evidence ESGE 2021Pre-Endoscopic Pharmacotherapy
The drugs given before the scope differ sharply depending on whether the source is presumed nonvariceal or variceal. Getting this right in the first hour matters most in suspected variceal hemorrhage, where early vasoactive and antibiotic therapy improve survival.
A pre-endoscopic proton pump inhibitor infusion may be considered to downgrade stigmata and reduce the need for endoscopic therapy, but it should never delay the procedure. It is an adjunct, not a substitute, for timely endoscopy.
Conditional Rec Moderate Evidence ACG 2021Start a vasoactive agent such as terlipressin or octreotide immediately in suspected variceal bleeding, and continue it for up to five days after confirmation. Early administration controls bleeding before endoscopy is even performed.
Strong Rec High Evidence Baveno VII 2022Administer prophylactic antibiotics, typically ceftriaxone, to any cirrhotic patient presenting with upper GI bleeding. This reduces infection, rebleeding, and mortality regardless of the eventual bleeding source.
Strong Rec High Evidence Baveno VII 2022Consider intravenous erythromycin roughly 30 to 90 minutes before endoscopy to clear the stomach of blood and clot, improving visualization and reducing the need for a second look.
Moderate Rec Moderate Evidence ESGE 2021Endoscopic Management of Acute Upper GI Bleeding
Endoscopy is both the diagnostic and the definitive therapeutic step in acute upper GI bleeding. Timing, lesion assessment, and choice of hemostatic technique each independently affect rebleeding and survival.
Timing of Endoscopy
Perform endoscopy within 24 hours of presentation for most patients admitted with acute upper GI bleeding, after adequate resuscitation. This window balances diagnostic yield against the risks of scoping an under-resuscitated patient.
Strong Rec High Evidence ACG 2021 ESGE 2021Do not pursue very early endoscopy within 12 hours for the routine purpose of improving outcomes in hemodynamically stable patients. Trial evidence shows no mortality benefit and potential harm from scoping before resuscitation is complete.
Against High Evidence Lau 2020Refer unstable patients with ongoing hemorrhage despite resuscitation for emergent endoscopy as soon as feasible. Persistent instability changes the calculus toward an earlier procedure with resuscitation continuing in the suite.
Moderate Rec Moderate Evidence ESGE 2021Hemostatic Technique for Ulcers
Apply endoscopic hemostasis to ulcers with high-risk stigmata, meaning active spurting or oozing and a non-bleeding visible vessel. These lesions carry the greatest rebleeding risk without treatment.
Strong Rec High Evidence ACG 2021 ESGE 2021Do not use dilute epinephrine injection as monotherapy. Combine it with a second method such as a thermal device or hemostatic clip, since combination therapy is superior for durable control.
Against High Evidence ACG 2021Do not treat clean-based ulcers or those with a flat pigmented spot endoscopically. These low-risk lesions can move directly to oral proton pump inhibitor therapy and early feeding.
Against High Evidence ACG 2021Consider an over-the-scope clip or hemostatic powder as a rescue option for ulcer bleeding that fails standard techniques. These tools expand the endoscopist’s armamentarium before escalation to radiology or surgery.
Conditional Rec Moderate Evidence ESGE 2021Hemostatic Technique for Varices
Perform endoscopic band ligation as the first-line treatment for bleeding esophageal varices. Banding is preferred over sclerotherapy for both initial control and lower complication rates.
Strong Rec High Evidence Baveno VII 2022Consider early placement of a transjugular intrahepatic portosystemic shunt within 72 hours in selected high-risk patients with variceal bleeding, such as those with advanced liver disease. Pre-emptive shunting reduces rebleeding and improves survival in this group.
Moderate Rec Moderate Evidence Baveno VII 2022Post-Endoscopic Care and Rebleeding
The work is not finished when the scope comes out. Acid suppression, management of antithrombotic drugs, and a clear plan for rebleeding determine whether the initial success holds.
Give high-dose proton pump inhibitor therapy after successful hemostasis of a high-risk ulcer, either as a continuous infusion or intermittent high-dose dosing for 72 hours. Both regimens lower rebleeding compared with standard dosing.
Strong Rec High Evidence ACG 2021Repeat endoscopy as the first response to ulcer rebleeding after initially successful therapy. A second endoscopic attempt controls many recurrences and avoids the morbidity of surgery.
Strong Rec Moderate Evidence ACG 2021Refer for transcatheter arterial embolization when a second endoscopic attempt fails to control ulcer bleeding. Angiographic intervention is now generally preferred over surgery as the next escalation step.
Moderate Rec Moderate Evidence ESGE 2021Resume low-dose aspirin for secondary cardiovascular prevention soon after hemostasis once the bleeding is controlled, rather than withholding it indefinitely. Continued antiplatelet protection usually outweighs the modest rebleeding risk.
Strong Rec Moderate Evidence ACG 2021Test for Helicobacter pylori in all patients with bleeding peptic ulcers and treat when positive, confirming eradication afterward. A negative test during acute bleeding should be repeated, as the acute setting lowers sensitivity.
Strong Rec High Evidence ACG 2021Clinical Decision Pathway
A practical, question-based approach to acute upper GI bleeding from the moment the patient arrives. Work through the questions in order.
Practical Reference Tables
Disposition by Clinical Scenario
| Clinical Scenario | Suggested Disposition | Endoscopy Timing | Practical Watch-Points |
|---|---|---|---|
| GBS 0–1, well | Outpatient with follow-up | Elective / ambulatory | Confirm reliable transport and safety-netting before discharge. |
| GBS 2–6, stable | Ward admission | Within 24 hours | Serial hemoglobin; nil by mouth until scoped. |
| GBS 7+ or unstable | Monitored bed or ICU | Within 24 hours, earlier if unstable | Two large-bore lines; type and crossmatch early. |
| Suspected variceal | Monitored bed or ICU | Within 12 hours preferred | Vasoactive drug plus antibiotics before the scope. |
Ulcer Stigmata and What to Do
| Endoscopic Appearance | Rebleed Risk if Untreated | Endoscopic Therapy | Acid Suppression | Disposition Note |
|---|---|---|---|---|
| Active spurting | Very high | Combination therapy | High-dose IV PPI 72h | Monitored bed; delay feeding. |
| Non-bleeding visible vessel | High | Combination therapy | High-dose IV PPI 72h | Inpatient observation. |
| Adherent clot | Intermediate | Consider after clot removal | High-dose IV PPI | Individualize; endoscopist judgment. |
| Flat pigmented spot | Low | Not indicated | Oral PPI | Early feeding; consider discharge. |
| Clean base | Minimal | Not indicated | Oral PPI | Discharge if otherwise well. |
Monitoring and Follow-Up
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| Hemoglobin | Every 6–12h while active, then daily | Stable or rising trend, not a single value | Over-transfusing toward a normal level instead of the restrictive target. |
| Vital signs | Continuously if high risk | Recurrent tachycardia or hypotension signalling rebleed | Attributing tachycardia to pain and missing early recurrence. |
| Urea-to-creatinine ratio | On admission | Disproportionate rise supports an upper source | Forgetting that renal impairment confounds the ratio. |
| H. pylori status | Before discharge and after treatment | Documented eradication for ulcer disease | Trusting a single negative test taken during the acute bleed. |
Evidence in Context
What the evidence shows, where the major frameworks agree, and where they diverge in acute upper GI bleeding.
Where ACG and ESGE Agree
Both societies endorse a restrictive transfusion strategy, endoscopy within 24 hours for most admitted patients, combination hemostasis for high-risk ulcers, and high-dose acid suppression after successful treatment. The convergence on these points reflects a robust shared evidence base.
Where the Frameworks Differ
Emphasis differs on pre-endoscopic PPI infusion and on the precise hemoglobin trigger in cardiac patients. Variceal management draws more heavily on the Baveno consensus, which addresses pre-emptive shunting in a way the nonvariceal guidelines do not.
Timing of Endoscopy: What the Trials Show
A landmark randomized trial found that urgent endoscopy within six hours did not lower mortality compared with scoping within 24 hours in high-risk patients. This reshaped guidance away from a rush to the suite and toward optimizing resuscitation first.
Restrictive Transfusion: The Evidence Base
A pivotal restrictive transfusion trial demonstrated better survival and less rebleeding when red cells were withheld until hemoglobin fell below 7 g/dL, compared with a more liberal threshold. The effect was most pronounced in patients with cirrhosis.
References
- 1.Laine L, Barkun AN, Saltzman JR, et al. ACG Clinical Guideline: Upper Gastrointestinal and Ulcer Bleeding. Am J Gastroenterol. 2021;116(5):899–917. doi:10.14309/ajg.0000000000001245
- 2.Gralnek IM, Stanley AJ, Morris AJ, et al. Endoscopic diagnosis and management of nonvariceal upper gastrointestinal hemorrhage (NVUGIH): ESGE Guideline — Update 2021. Endoscopy. 2021;53(3):300–332. doi:10.1055/a-1369-5274
- 3.de Franchis R, Bosch J, Garcia-Tsao G, et al. Baveno VII — Renewing consensus in portal hypertension. J Hepatol. 2022;76(4):959–974. doi:10.1016/j.jhep.2021.12.022
- 4.Villanueva C, Colomo A, Bosch A, et al. Transfusion strategies for acute upper gastrointestinal bleeding. N Engl J Med. 2013;368(1):11–21. doi:10.1056/NEJMoa1211801
- 5.Lau JYW, Yu Y, Tang RSY, et al. Timing of Endoscopy for Acute Upper Gastrointestinal Bleeding. N Engl J Med. 2020;382(14):1299–1308. doi:10.1056/NEJMoa1912484
How to Read the Evidence Tags
Every recommendation carries two tags for recommendation strength and evidence quality — Medaptly’s own simplified interpretations, not a reproduction of any society’s grading system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |