
Atrial Flutter Management: 8 Essential Clinical Decisions
Clinical Practice Update — Anticoagulation Thresholds, Rate Control, and Catheter Ablation Referral in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based atrial flutter management in adults, with emphasis on anticoagulation, rate control, and ablation referral
- Target Audience
- Primary care physicians, internists, emergency physicians, hospitalists, residents
- Setting
- Primary care, emergency department, inpatient internal medicine
- Source Evidence
- •2023 ACC/AHA/ACCP/HRS Guideline for the Diagnosis and Management of Atrial Fibrillation
- •2024 ESC Guidelines for the Management of Atrial Fibrillation
- •2019 AHA/ACC/HRS Focused Update on AF Management
- •CABANA Trial — Catheter Ablation versus Antiarrhythmic Drug Therapy (JAMA, 2019)
Key Clinical Takeaways
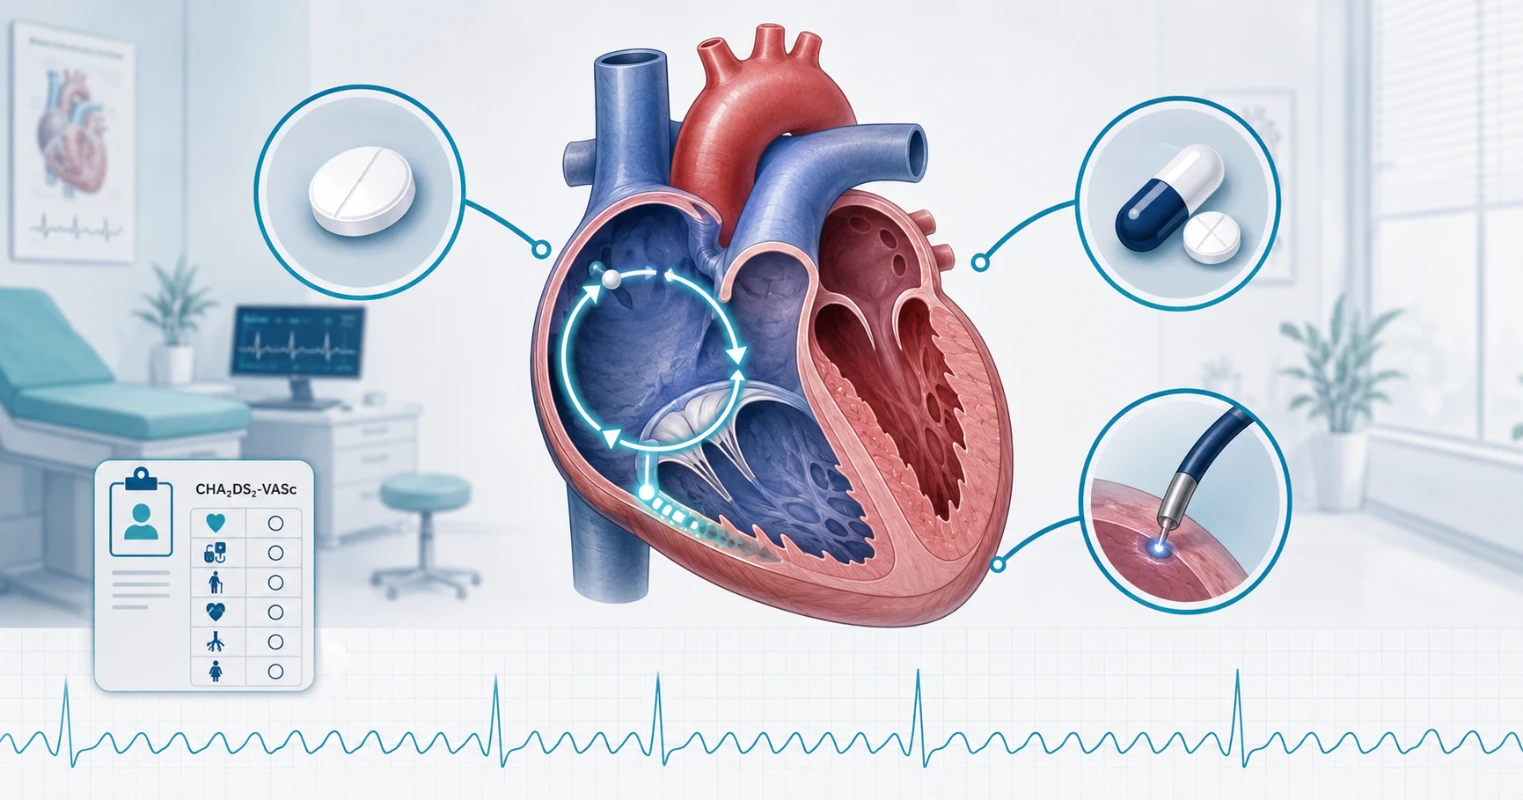
Effective atrial flutter management in adults turns on three sequential decisions: anticoagulate based on stroke risk, control either rate or rhythm based on symptoms and stability, and refer typical flutter for catheter ablation earlier than most clinicians instinctively do. The takeaways below distill the evidence into rules you can apply at the bedside.
- 1Treat the thromboembolic risk of atrial flutter the same as atrial fibrillation — the stroke risk profile is essentially equivalent
- 2Start a direct oral anticoagulant when CHA2DS2-VASc reaches 2 or higher in men, or 3 or higher in women
- 3Identify typical cavotricuspid isthmus-dependent flutter from sawtooth waves in the inferior leads on a 12-lead ECG
- 4Use a beta-blocker first for rate control; reserve diltiazem or verapamil for patients without reduced ejection fraction
- 5Pursue synchronized DC cardioversion at lower energies than for atrial fibrillation — 50–100 J biphasic is usually sufficient
- 6Refer symptomatic patients with typical flutter for cavotricuspid isthmus ablation early — acute success exceeds 95% with low complication rates
- 7Anticoagulate at least three weeks before and four weeks after elective cardioversion unless the arrhythmia has been present under 48 hours
- 8Continue surveillance for atrial fibrillation after successful flutter ablation — new-onset AF appears in roughly one in three patients within a few years
Confirming the Diagnosis Before Atrial Flutter Management
Atrial flutter is a macro-reentrant atrial tachycardia, most commonly circulating around the tricuspid annulus in a counterclockwise direction. The classic ECG signature is regular sawtooth flutter waves at roughly 300 bpm, most visible in leads II, III, and aVF, with a ventricular rate that depends on AV node conduction (often 150 bpm at 2:1 block). Distinguishing typical from atypical flutter at the outset shapes every downstream decision.
Because flutter and fibrillation frequently coexist in the same patient and share the same thromboembolic risk profile, the principles outlined here intersect heavily with atrial fibrillation management.
Obtain a 12-lead ECG in every patient presenting with a regular narrow-complex tachycardia near 150 bpm, since 2:1 atrial flutter is the most commonly missed diagnosis at that rate.
Strong Rec High Evidence ACC/AHA 2023Perform a transient vagal manoeuvre or administer adenosine if the rhythm is unclear — unmasking the flutter waves through transient AV block confirms the diagnosis without committing to cardioversion.
Moderate Rec Moderate Evidence ACC/AHA 2023Order a transthoracic echocardiogram in every newly diagnosed patient to assess left ventricular function, atrial size, and valvular disease — findings that shape both anticoagulation and rate-control choices.
Strong Rec Moderate Evidence ACC/AHA 2023 ESC 2024Search for and treat reversible triggers at presentation: thyrotoxicosis, sepsis, pulmonary embolism, alcohol binge, and uncontrolled hypertension are the most common.
Strong Rec Low Evidence Clinical ConsensusAnticoagulation Thresholds in Atrial Flutter Management
Atrial flutter carries an annual stroke risk comparable to atrial fibrillation, and the major guideline bodies apply the same anticoagulation rules to both rhythms. The single most important decision is whether to start anticoagulation — this is driven by stroke risk, not by symptoms, rhythm strategy, or whether the flutter has been “successfully” cardioverted.
Calculate a CHA2DS2-VASc score in every adult diagnosed with atrial flutter, then start oral anticoagulation when the score reaches 2 or more in men or 3 or more in women.
Strong Rec High Evidence ACC/AHA 2023 ESC 2024Consider anticoagulation in men with a score of 1 and in women with a score of 2, weighing bleeding risk and individual preference rather than applying the threshold rigidly.
Conditional Rec Moderate Evidence ESC 2024Choose a direct oral anticoagulant as the first-line agent for most patients. DOAC selection should account for renal function, body weight, age, and interacting medications.
Strong Rec High Evidence ACC/AHA 2023 ESC 2024Prescribe warfarin instead of a DOAC when the patient has a mechanical heart valve or moderate-to-severe rheumatic mitral stenosis — DOACs are not appropriate in these settings.
Against High Evidence ACC/AHA 2023Document a HAS-BLED score at baseline and address modifiable bleeding risks (uncontrolled blood pressure, concurrent NSAIDs, alcohol excess) — do not use the score to withhold anticoagulation.
Strong Rec Moderate Evidence ESC 2024Reassess CHA2DS2-VASc annually or whenever clinical status changes — the score is dynamic, and patients can cross the threshold for anticoagulation as they age.
Strong Rec Moderate Evidence ESC 2024Continue anticoagulation after successful catheter ablation when the CHA2DS2-VASc score remains at or above the treatment threshold — restored sinus rhythm does not eliminate stroke risk.
Strong Rec Moderate Evidence ACC/AHA 2023Anticoagulation Decisions by Risk Profile
| CHA2DS2-VASc | Risk Picture | Recommendation | Preferred Agent | Practical Pitfalls |
|---|---|---|---|---|
| 0 (M) or 1 (F) | Truly low annual stroke risk | No anticoagulation | — | Reassess yearly; risk drifts upward with age |
| 1 (M) or 2 (F) | Borderline — benefit varies by which risk factor | Shared decision; many will benefit | DOAC if started | Age 65–74 alone is a strong signal to treat |
| ≥2 (M) or ≥3 (F) | Clear net benefit from anticoagulation | Anticoagulate | DOAC (apixaban, rivaroxaban, edoxaban, dabigatran) | Dose-reduce based on age, weight, renal function |
| Any (with prior stroke/TIA) | High recurrent stroke risk irrespective of score | Anticoagulate (no upper age cutoff) | DOAC unless contraindicated | Delay 1–14 days post-stroke depending on size |
| Any (with mechanical valve or mod-severe MS) | DOACs lack evidence and may harm | Anticoagulate with VKA | Warfarin (INR target by valve type) | Avoid DOACs entirely in this group |
Rate Control Choices in Atrial Flutter Management
Rate control is harder in atrial flutter than in atrial fibrillation, because the regular 300 bpm atrial activity tends to conduct at fixed ratios (2:1, 3:1, 4:1), giving abrupt changes in ventricular rate. The drug choice depends on left ventricular function, the acute or chronic setting, and the desired heart rate target.
The presence of heart failure with reduced ejection fraction reshapes nearly every rate-control choice — non-dihydropyridine calcium channel blockers move from first-line to contraindicated.
Start a beta-blocker (metoprolol succinate 50–200 mg daily, bisoprolol 2.5–10 mg daily, or carvedilol 6.25–25 mg twice daily) as first-line rate control in most adults.
Strong Rec High Evidence ACC/AHA 2023Prescribe diltiazem (120–360 mg daily) or verapamil (240–480 mg daily) when a beta-blocker is poorly tolerated, provided ejection fraction is preserved.
Strong Rec High Evidence ACC/AHA 2023Do not use diltiazem or verapamil when the left ventricular ejection fraction is below 40% — their negative inotropic effect can precipitate decompensation.
Against High Evidence ACC/AHA 2023 ESC 2024Add digoxin (0.125–0.25 mg daily) as a second agent when a beta-blocker alone fails to reach the rate target, especially in sedentary or older adults.
Moderate Rec Moderate Evidence ACC/AHA 2023Target a resting heart rate under 110 bpm in asymptomatic patients; tighten the goal under 80 bpm only when symptoms persist or tachycardia-induced cardiomyopathy is suspected.
Moderate Rec Moderate Evidence ACC/AHA 2023Initiate IV diltiazem or IV metoprolol for acute rate control in hemodynamically stable patients with rapid ventricular response, then transition to oral therapy as the rhythm stabilises.
Strong Rec Moderate Evidence ACC/AHA 2023Rate Control Drugs by Clinical Scenario
| Clinical Scenario | First-Line Drug | Starting Dose | Watch Out For | Cost Tier |
|---|---|---|---|---|
| Preserved EF, no contraindication | Metoprolol succinate | 25–50 mg daily | Fatigue, bradycardia at rest | Low |
| HFrEF (EF <40%) | Carvedilol or bisoprolol | 3.125 mg BID (carvedilol) | Start low, uptitrate every 2 weeks | Low |
| Reactive airway disease, beta-blocker intolerant | Diltiazem (extended release) | 120 mg daily | Avoid if EF <40%; constipation | Low |
| Sedentary, persistent tachycardia on beta-blocker | Add digoxin | 0.125 mg daily | Toxicity in renal impairment; narrow window | Low |
| Acute rapid response, stable patient | IV diltiazem or IV metoprolol | 0.25 mg/kg IV (diltiazem) | Continuous monitoring; hypotension | Low |
Rhythm Control and Cardioversion Strategies
Atrial flutter responds especially well to electrical cardioversion — usually at lower energies than atrial fibrillation. The decision tree turns on hemodynamic stability, duration of the arrhythmia, and adequacy of prior anticoagulation.
Perform immediate synchronized DC cardioversion when atrial flutter causes hemodynamic instability (hypotension, pulmonary oedema, active ischaemia) regardless of anticoagulation status.
Strong Rec High Evidence ACC/AHA 2023Use 50–100 J biphasic synchronized energy as the initial cardioversion shock for atrial flutter; escalate to 200 J only if the first attempt fails.
Strong Rec Moderate Evidence ACC/AHA 2023Confirm therapeutic anticoagulation for at least three uninterrupted weeks before elective cardioversion, or perform transesophageal echocardiography to rule out left atrial thrombus when earlier conversion is needed.
Strong Rec High Evidence ACC/AHA 2023 ESC 2024Continue anticoagulation for at least four weeks after every cardioversion attempt — atrial stunning means thromboembolic risk persists even after sinus rhythm returns.
Strong Rec High Evidence ACC/AHA 2023 ESC 2024Consider IV ibutilide or oral dofetilide for pharmacologic cardioversion in monitored settings when electrical cardioversion is impractical — both require continuous telemetry and QT monitoring.
Conditional Rec Moderate Evidence ACC/AHA 2023Do not start flecainide or propafenone without first ensuring AV nodal blockade is in place — class Ic drugs can slow the atrial rate enough to allow 1:1 conduction with catastrophic ventricular rates.
Against Moderate Evidence ESC 2024When to Refer for Catheter Ablation
Cavotricuspid isthmus ablation is one of the most successful procedures in electrophysiology, with single-procedure acute success above 95% and complication rates under 1% at experienced centres. The threshold for referral should be low in symptomatic typical flutter.
Refer adults with symptomatic typical (cavotricuspid isthmus-dependent) atrial flutter for catheter ablation as first-line therapy, ahead of long-term antiarrhythmic drugs.
Strong Rec High Evidence ACC/AHA 2023 ESC 2024Refer for ablation early when atrial flutter has caused tachycardia-mediated cardiomyopathy — ablation can reverse the cardiomyopathy in most patients within months.
Strong Rec Moderate Evidence ACC/AHA 2023Consider ablation in patients with asymptomatic typical flutter who would otherwise require lifelong AV nodal blockade for rate control — ablation often eliminates the need for those drugs.
Moderate Rec Moderate Evidence ACC/AHA 2023Refer atypical (non-isthmus-dependent) flutter to a high-volume electrophysiology centre — these circuits often require 3D mapping and have lower success rates than typical flutter.
Moderate Rec Moderate Evidence ESC 2024Counsel patients that catheter ablation cures the flutter circuit but does not eliminate the risk of developing atrial fibrillation — new AF emerges in roughly 30% of patients over five years.
Strong Rec Moderate Evidence ACC/AHA 2023Ensure therapeutic anticoagulation throughout the periprocedural window and for at least four weeks after ablation, regardless of CHA2DS2-VASc score.
Strong Rec High Evidence ESC 2024Who Benefits Most from Early Ablation Referral
| Patient Profile | Ablation Priority | Expected Outcome | Pre-Procedure Setup |
|---|---|---|---|
| Symptomatic typical flutter, otherwise well | High — first-line | >95% acute success; ~10% flutter recurrence | Anticoagulate 3 weeks pre, TTE, baseline labs |
| Tachycardia-mediated cardiomyopathy | High — urgent | LV function often recovers within 3–6 months | Anticoagulate, optimise heart failure therapy |
| Atypical flutter or post-surgical scar circuit | Moderate — specialist centre | ~75–85% acute success; longer procedure | Anticoagulate, 3D mapping, often TEE |
| Drug-induced flutter on flecainide for AF | High — CTI ablation allows drug continuation | Excellent for the flutter; AF often persists | Continue flecainide; co-prescribe AV blocker |
| Frail older adult, asymptomatic, well-rate-controlled | Low — manage medically | Rate control with continued anticoagulation | — |
Clinical Decision Pathway
A practical, question-based approach to adult atrial flutter management. Work through the questions in order — each answer reshapes the next decision.
Monitoring After Atrial Flutter Management
The work is not finished once the patient is anticoagulated and rate-controlled. Atrial flutter has a strong tendency to recur as atrial fibrillation, and ongoing surveillance shapes long-term outcomes.
Monitor for symptoms of recurrent flutter or new-onset atrial fibrillation at every follow-up — up to 30% of post-ablation patients develop AF within five years.
Strong Rec Moderate Evidence ACC/AHA 2023Reassess CHA2DS2-VASc and HAS-BLED annually, and adjust anticoagulation when modifiable bleeding risks improve or stroke risk factors accumulate.
Strong Rec Moderate Evidence ESC 2024Consider intermittent rhythm monitoring (1- to 2-week ambulatory ECG patch annually) after CTI ablation in patients whose anticoagulation decision depends on rhythm status.
Conditional Rec Low Evidence Expert ConsensusCounsel patients on modifiable lifestyle factors: weight reduction, alcohol moderation, obstructive sleep apnoea screening, and blood pressure control all reduce arrhythmia burden.
Strong Rec Moderate Evidence ACC/AHA 2023 ESC 2024Follow-Up Schedule After Initial Atrial Flutter Management
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| 12-lead ECG | 4 weeks after cardioversion or ablation, then yearly | Sinus rhythm, recurrent flutter, new AF | Asymptomatic recurrences are common — do not rely on symptoms alone |
| Renal function | Baseline, then every 6–12 months on a DOAC | CrCl drift may require DOAC dose reduction | Acute illness can drop CrCl suddenly; recheck |
| CHA2DS2-VASc | Annually or with any change in clinical status | Crossing the threshold may trigger initiation | Age 65 and age 75 are key tipping points |
| Echocardiogram | If new symptoms or worsening rate control | New cardiomyopathy, valvular progression | Routine annual TTE not generally needed if stable |
Evidence in Context
A summary of where the major guidelines converge, where they part ways, and what the most influential trials add to the picture.
Where ACC/AHA 2023 and ESC 2024 Agree
Both frameworks treat atrial flutter and atrial fibrillation as equivalent for the purposes of stroke prevention. Both endorse CHA2DS2-VASc as the primary decision tool and DOACs as the preferred anticoagulant class. Both place catheter ablation as a first-line option for symptomatic typical flutter, and both emphasise that restored sinus rhythm does not eliminate the need for ongoing anticoagulation when stroke risk remains elevated.
Where the Two Frameworks Diverge
Anticoagulation thresholds in low scores: ESC 2024 places greater emphasis on individual risk factors at the borderline (score of 1 in men, 2 in women), leaning toward shared-decision treatment more often than ACC/AHA 2023.
Rhythm control framing: ESC 2024 places early rhythm control more centrally in the management algorithm, drawing on data showing improved cardiovascular outcomes with earlier rhythm restoration.
Ablation pathway: Both place CTI ablation as Class I for symptomatic typical flutter, but ESC describes catheter ablation as appropriate even before a trial of antiarrhythmic drugs — a stronger upfront stance than the ACC/AHA framing.
CTI Ablation: Why It Outperforms Drugs
Randomised data over the past two decades have consistently shown cavotricuspid isthmus ablation to be more effective than antiarrhythmic drug therapy for typical flutter, with single-procedure success rates above 95% and major complication rates under 1% at experienced centres. Most patients can stop their rhythm-control drugs after a successful ablation, though many remain on anticoagulation if their stroke risk profile requires it.
Anticoagulation After Successful Ablation
A recurring question in clinic is whether to stop anticoagulation in a patient who appears to have remained in sinus rhythm after CTI ablation. The current guideline position from both ACC/AHA and ESC is that stroke risk — not rhythm status — drives the decision. New-onset atrial fibrillation occurs in roughly one third of patients after typical flutter ablation, and these episodes are often asymptomatic. Continued anticoagulation in patients with elevated CHA2DS2-VASc remains the safer default.
References
- 1.Joglar JA, Chung MK, Armbruster AL, et al. 2023 ACC/AHA/ACCP/HRS Guideline for the Diagnosis and Management of Atrial Fibrillation. Circulation. 2024;149(1):e1–e156. doi:10.1161/CIR.0000000000001193
- 2.Van Gelder IC, Rienstra M, Bunting KV, et al. 2024 ESC Guidelines for the Management of Atrial Fibrillation. European Heart Journal. 2024;45(36):3314–3414. doi:10.1093/eurheartj/ehae176
- 3.January CT, Wann LS, Calkins H, et al. 2019 AHA/ACC/HRS Focused Update of the 2014 AHA/ACC/HRS Guideline for the Management of Patients With Atrial Fibrillation. Circulation. 2019;140(2):e125–e151. doi:10.1161/CIR.0000000000000665
- 4.Packer DL, Mark DB, Robb RA, et al. Effect of Catheter Ablation vs Antiarrhythmic Drug Therapy on Mortality, Stroke, Bleeding, and Cardiac Arrest Among Patients With Atrial Fibrillation: The CABANA Randomized Clinical Trial. JAMA. 2019;321(13):1261–1274. doi:10.1001/jama.2019.0693
How to Read the Evidence Tags
Every recommendation in this article carries three tags — recommendation strength, evidence quality, and source guideline. The tags are Medaptly’s own simplified interpretations of the underlying evidence framework, designed for rapid clinical reading.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | Benefit is less certain — individualise to the patient. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |