
Myasthenia Gravis Treatment: Diagnosis and Therapy Guide
Clinical Practice Update — Classification, Pharmacotherapy, Thymectomy, and Crisis Management in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based myasthenia gravis treatment: diagnostic workup, symptomatic therapy, immunosuppression, advanced biologics, thymectomy decisions, and crisis care in immunocompetent adults
- Target Audience
- Neurologists, internists, emergency physicians, critical care clinicians, residents
- Setting
- Neurology outpatient clinics, emergency departments, intensive care units, neurohospitalist services
- Source Evidence
- •International Consensus Guidance for Management of Myasthenia Gravis (Sanders et al., 2016)
- •International Consensus Guidance Update (Narayanaswami et al., 2020)
- •MGTX Trial — Thymectomy in Non-Thymomatous Myasthenia Gravis (NEJM, 2016)
- •REGAIN Trial — Eculizumab in Refractory Generalized MG (Lancet Neurology, 2017)
- •ADAPT Trial — Efgartigimod in Generalized MG (Lancet Neurology, 2021)
Key Clinical Takeaways
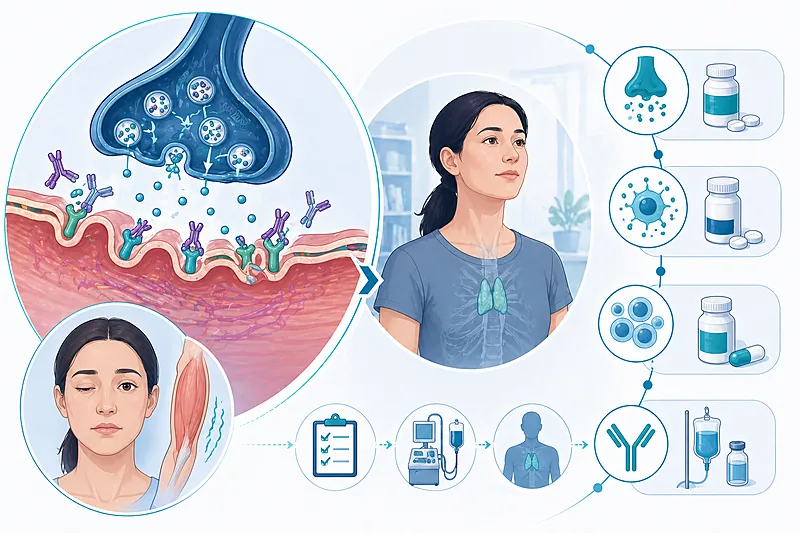
Effective myasthenia gravis treatment is stepwise and individualised. The modern therapeutic framework pairs symptomatic relief (pyridostigmine) with targeted immunomodulation (corticosteroids, steroid-sparing agents, complement inhibitors, and FcRn antagonists), layered on top of structural decisions such as thymectomy. With contemporary therapy, most patients achieve minimal manifestation status and a near-normal lifespan.
- 1Confirm the diagnosis with acetylcholine receptor (AChR) antibodies first; if negative, test anti-MuSK and LRP4 before labelling the patient seronegative → Diagnosis
- 2Classify disease severity with MGFA classification at baseline — it anchors treatment decisions and outcome monitoring → Diagnosis
- 3Start pyridostigmine 30–60 mg three or four times daily as first-line symptomatic therapy and titrate to effect → First-Line Therapy
- 4Obtain chest CT (or MRI) to exclude thymoma in every patient with a new myasthenia gravis diagnosis → Diagnosis
- 5Add prednisone (start low, titrate up) when symptoms persist on pyridostigmine; combine with a steroid-sparing agent early → Immunosuppression
- 6Offer thymectomy in AChR-positive, non-thymomatous generalised myasthenia gravis for adults aged under about 65 — MGTX trial evidence supports benefit → Thymectomy
- 7Consider complement inhibitors (eculizumab, ravulizumab) or FcRn antagonists (efgartigimod, rozanolixizumab) in refractory AChR-positive disease → Advanced Therapies
- 8Treat myasthenic crisis in an intensive care setting with IVIG or plasmapheresis; anticipate respiratory failure early → Crisis
- 9Always check the medication list — many common drugs worsen myasthenia gravis and can trigger crisis → Monitoring
Diagnosis and MGFA Classification
Myasthenia gravis is an autoimmune disorder of the neuromuscular junction, most commonly caused by antibodies against the postsynaptic acetylcholine receptor. The hallmark is fluctuating, fatigable weakness — worse with sustained activity, better after rest — involving ocular, bulbar, limb, or respiratory muscles.
A confident diagnosis requires a compatible clinical picture plus supportive serological, electrophysiological, or pharmacological evidence. Classify severity using the MGFA classification (Classes I through V) at baseline and use it as the reference point for subsequent treatment decisions.
Test for AChR-binding antibodies first in any patient with suspected myasthenia gravis. If negative, obtain anti-MuSK antibodies, and consider LRP4 and agrin antibodies before accepting a seronegative label.
Strong Rec High Evidence ICG MG 2016 ICG MG Update 2020Obtain thoracic imaging (CT or MRI) in every newly diagnosed patient to identify or exclude thymoma. Roughly 10–15% of patients harbour a thymoma, and its presence makes thymectomy mandatory regardless of age.
Strong Rec High Evidence ICG MG 2016Consider repetitive nerve stimulation or single-fibre EMG when serology is negative but the clinical picture is suggestive. Single-fibre EMG is the most sensitive test but requires experienced operators.
Moderate Rec Moderate Evidence ICG MG 2016Document baseline MGFA class, MG-ADL score, and MG-QOL15 score at the first visit. Objective tools anchor follow-up comparisons and identify patients drifting toward treatment failure.
Strong Rec Moderate Evidence ICG MG Update 2020MGFA Classification at a Glance
| Class | Clinical Pattern | Typical Implications for Therapy | Practical Tips |
|---|---|---|---|
| Class I | Ocular weakness only (ptosis, diplopia) | Pyridostigmine first; low-dose prednisone if symptoms persist | Treat to reduce risk of generalisation; many patients generalise within 2 years |
| Class II | Mild generalised weakness | Pyridostigmine plus steroid-sparing agent typically needed | Consider thymectomy in AChR-positive, age under ~65 |
| Class III | Moderate generalised weakness | Full immunosuppression; early steroid-sparing agent | Monitor bulbar and respiratory function closely |
| Class IV | Severe generalised weakness | Consider IVIG or plasmapheresis to bridge; add advanced therapy if refractory | High threshold for elective procedures; pre-treat before surgery |
| Class V | Intubation (with or without ventilation) — myasthenic crisis | Intensive care; IVIG or plasmapheresis; withhold pyridostigmine while intubated | Look hard for a precipitant (infection, drug, missed dose) |
First-Line Myasthenia Gravis Treatment
The foundation of myasthenia gravis treatment is symptomatic therapy with an acetylcholinesterase inhibitor, most commonly pyridostigmine. It buys time while immunomodulation takes effect and remains useful across all stages of disease. Not every patient needs a full immunosuppressive regimen, but every patient should be offered symptomatic therapy unless contraindicated.
Prescribe pyridostigmine 30–60 mg orally every 4–6 hours as initial symptomatic therapy. Titrate the dose and interval to symptom response rather than a fixed target.
Strong Rec Moderate Evidence ICG MG 2016Counsel patients that pyridostigmine does not modify the underlying disease — it treats symptoms only. Do not exceed roughly 480 mg daily; higher doses rarely help and can paradoxically worsen weakness (cholinergic crisis).
Strong Rec Low Evidence ICG MG 2016Review the medication list at every visit for drug interactions and agents known to worsen myasthenia gravis — aminoglycosides, fluoroquinolones, macrolides, telithromycin, beta-blockers, magnesium, and iodinated contrast are among the common offenders.
Strong Rec Moderate Evidence ICG MG 2016Note that pyridostigmine is less effective in anti-MuSK disease and can occasionally worsen symptoms. Start at a low dose and advance only if there is clear benefit; otherwise move directly to immunosuppression.
Moderate Rec Moderate Evidence ICG MG Update 2020Immunosuppression in Myasthenia Gravis Treatment
Long-term control of generalised disease almost always requires immunosuppression. Corticosteroids remain the most rapidly effective option, but their long-term toxicity drives a parallel strategy: add a steroid-sparing agent early so the steroid dose can be reduced to the minimum effective level.
Start prednisone at a low dose (10–20 mg daily) and titrate upward by 5–10 mg every few days to a typical target of 0.75–1 mg/kg/day. Low, stepwise initiation avoids the well-documented early worsening that can occur with high starting doses.
Strong Rec Moderate Evidence ICG MG 2016Add a steroid-sparing agent (azathioprine or mycophenolate mofetil) early in patients likely to need ongoing immunosuppression. The steroid-sparing effect takes 6–12 months to manifest, so start sooner than the clinical picture seems to demand.
Strong Rec Moderate Evidence ICG MG Update 2020Consider rituximab in anti-MuSK myasthenia gravis, where it is particularly effective and can produce durable remission. In AChR-positive disease, rituximab is a reasonable option after failure of conventional immunosuppression.
Moderate Rec Moderate Evidence ICG MG Update 2020Immunosuppressive Agents at a Glance
| Drug | Typical Maintenance Dose | Time to Onset | Monitoring and Practical Tips |
|---|---|---|---|
| Prednisone | Start 10–20 mg; titrate to 0.75–1 mg/kg; taper once stable | 2–4 weeks | Bone protection, glucose monitoring, PPI if indicated. Warn about early worsening. |
| Azathioprine | 2–3 mg/kg/day | 6–12 months | Check TPMT activity before starting. Monitor FBC and LFTs regularly. |
| Mycophenolate mofetil | 1000–1500 mg twice daily | 6–12 months | Teratogenic. Monitor FBC. Counsel on contraception in women of childbearing age. |
| Tacrolimus | 3–5 mg/day (by trough levels) | 3–6 months | Watch renal function, blood pressure, glucose. Useful when thiopurines fail. |
| Rituximab | Induction 1 g × 2, then redose by clinical course | Weeks to months | Particularly effective in MuSK-positive disease. Screen for hepatitis B. |
Advanced Biologics in Myasthenia Gravis Treatment
Targeted biologics have transformed the management of refractory disease. The complement inhibitors (eculizumab, ravulizumab, and zilucoplan) block downstream membrane attack complex formation at the neuromuscular junction, while FcRn antagonists (efgartigimod and rozanolixizumab) rapidly reduce circulating IgG including pathogenic autoantibodies.
These agents are typically reserved for AChR-positive patients with refractory generalised disease, though the eligible population is expanding as real-world experience accumulates.
Consider a complement inhibitor (eculizumab, ravulizumab) in AChR-positive generalised myasthenia gravis that remains refractory despite adequate trials of corticosteroids and at least one steroid-sparing agent. Ensure meningococcal vaccination is up to date before starting.
Moderate Rec High Evidence REGAIN 2017 ICG MG Update 2020Consider an FcRn antagonist (efgartigimod or rozanolixizumab) in AChR-positive generalised disease refractory to standard therapy. Efgartigimod produces rapid, measurable reductions in total IgG and in MG-ADL scores within weeks.
Moderate Rec High Evidence ADAPT 2021Do not start a complement inhibitor or FcRn antagonist as first-line therapy in treatment-naive patients. The evidence base supports their use in refractory disease, and cost plus long-term safety data favour a sequential approach.
Against Low Evidence ICG MG Update 2020Clinical Decision Pathway
A practical, question-based approach to building a treatment plan for newly diagnosed or inadequately controlled myasthenia gravis. Work through the questions in order from diagnosis to escalation.
Thymectomy in Myasthenia Gravis
Thymectomy has two distinct indications. In patients with a thymoma, thymectomy is oncologic and mandatory. In AChR-positive, non-thymomatous generalised disease, thymectomy is immunomodulatory and offers long-term clinical benefit — the MGTX trial established this with randomised, controlled evidence.
Perform thymectomy in every patient with a thymoma. This is an oncologic indication and applies regardless of age, antibody status, or severity.
Strong Rec High Evidence ICG MG 2016Offer thymectomy (preferably via video-assisted thoracoscopic or robotic approach) to adults with AChR-positive, non-thymomatous generalised myasthenia gravis aged roughly 18–65, within the first few years of disease onset.
Strong Rec High Evidence MGTX 2016Do not perform thymectomy routinely in anti-MuSK or LRP4-positive disease — evidence of benefit is lacking in these subgroups. Thymectomy in seronegative disease can be considered on an individualised basis.
Against Moderate Evidence ICG MG Update 2020Optimise disease control before elective thymectomy. Pre-operative IVIG or plasmapheresis is commonly used in patients with more than mild generalised weakness, to reduce the risk of post-operative crisis.
Strong Rec Moderate Evidence ICG MG 2016Managing Myasthenic Crisis
Myasthenic crisis is defined as respiratory failure requiring invasive or non-invasive ventilation, or severe bulbar weakness threatening airway protection. Approximately 15–20% of patients experience at least one crisis in their lifetime. Survival has improved dramatically with modern intensive care, but early recognition and rapid initiation of IVIG or plasmapheresis remain central.
Admit to a monitored or intensive care setting any patient with bulbar weakness limiting secretion management, a forced vital capacity below about 20 mL/kg, negative inspiratory force below 30 cmH₂O, or rapidly progressive weakness.
Strong Rec Moderate Evidence ICG MG 2016Start IVIG (2 g/kg divided over 2–5 days) or plasmapheresis (5–7 exchanges) promptly in crisis. Choice between the two depends on availability, comorbidities (renal function, volume status), and institutional expertise — both are effective.
Strong Rec High Evidence ICG MG 2016 ICG MG Update 2020Identify and treat the precipitating factor at the same time as IVIG or plasmapheresis — infection, missed medications, surgery, pregnancy, or a newly prescribed interacting drug are the most common triggers.
Strong Rec Moderate Evidence ICG MG 2016Withhold or reduce pyridostigmine in intubated patients to decrease airway secretions. Resume once the patient is extubated and able to clear secretions effectively.
Moderate Rec Low Evidence ICG MG 2016Monitoring and Follow-Up
Structured follow-up catches drift early. Combine objective measures, drug safety monitoring, and an ongoing review of precipitants.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| MG-ADL and MGFA class | Every visit | Improving or stable trajectory | Relying on gestalt impression rather than documented scores |
| Immunosuppressant safety | FBC and LFT every 1–3 months initially, then 3–6 monthly | Cytopenias, transaminase rise, infections | Missing late-onset marrow toxicity, skin cancer surveillance |
| Steroid-related complications | Every visit; bone density at baseline and every 2 years | Glucose, blood pressure, weight, bone health, mood | Forgetting calcium, vitamin D, and bisphosphonate prophylaxis |
| Medication list review | Every visit | Any new drug that may worsen myasthenia gravis | Prescribing fluoroquinolones or macrolides without checking |
| Vaccinations | Annually and before new biologics | Influenza, pneumococcal, COVID-19, meningococcal (before complement inhibitor) | Giving live vaccines while on significant immunosuppression |
Evidence in Context
A brief map of the key trials and consensus documents that define modern myasthenia gravis treatment, and where the practice is still evolving.
The International Consensus Guidance
The 2016 International Consensus Guidance (Sanders and colleagues) and its 2020 update (Narayanaswami and colleagues) provide the most widely adopted framework for myasthenia gravis treatment. Together they define treatment goals, staging, standard drug regimens, thymectomy indications, and the place of newer biologics.
MGTX Trial — The Case for Thymectomy
The MGTX trial (Wolfe and colleagues, 2016) randomly assigned adults with AChR-positive non-thymomatous generalised disease to extended thymectomy plus prednisone or prednisone alone. Over 3 years, the thymectomy group had better quantitative myasthenia gravis scores and required substantially less prednisone. The effect persisted through longer-term follow-up.
REGAIN, ADAPT, and the Biologic Era
REGAIN (eculizumab), CHAMPION MG (ravulizumab), ADAPT (efgartigimod), and MycarinG (rozanolixizumab) collectively established complement inhibition and FcRn antagonism as effective strategies in refractory AChR-positive disease. The landscape is changing rapidly, and new head-to-head data will shape sequencing decisions over the coming years.
Open Questions
Outstanding questions include how to sequence complement inhibitors versus FcRn antagonists, the place of rituximab in AChR-positive disease, the role of thymectomy in older adults or anti-MuSK patients, optimal management during pregnancy, and whether emerging T-cell-targeted agents will reshape first-line therapy.
References
- 1.Sanders DB, Wolfe GI, Benatar M, et al. International consensus guidance for management of myasthenia gravis: Executive summary. Neurology. 2016;87(4):419–425. doi:10.1212/WNL.0000000000002790
- 2.Narayanaswami P, Sanders DB, Wolfe G, et al. International Consensus Guidance for Management of Myasthenia Gravis: 2020 Update. Neurology. 2021;96(3):114–122. doi:10.1212/WNL.0000000000011124
- 3.Wolfe GI, Kaminski HJ, Aban IB, et al. Randomized Trial of Thymectomy in Myasthenia Gravis. N Engl J Med. 2016;375(6):511–522. doi:10.1056/NEJMoa1602489
- 4.Howard JF Jr, Utsugisawa K, Benatar M, et al. Safety and efficacy of eculizumab in anti-acetylcholine receptor antibody-positive refractory generalised myasthenia gravis (REGAIN). Lancet Neurol. 2017;16(12):976–986. doi:10.1016/S1474-4422(17)30369-1
- 5.Howard JF Jr, Bril V, Vu T, et al. Safety, efficacy, and tolerability of efgartigimod in patients with generalised myasthenia gravis (ADAPT). Lancet Neurol. 2021;20(7):526–536. doi:10.1016/S1474-4422(21)00159-9
How to Read the Evidence Tags
Every recommendation in this article carries two tags — for recommendation strength and evidence quality — along with a source tag. These are Medaptly’s own simplified interpretations, not reproductions of any guideline body’s classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |