
Myasthenic Crisis Management: Respiratory Support and Rescue Immunotherapy
Clinical Practice Update — Recognition, Respiratory Monitoring, and Emergency Management in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Recognition and emergency myasthenic crisis management in adults
- Target Audience
- Neurologists, emergency physicians, intensivists, hospitalists, residents
- Setting
- Emergency department, intensive care unit, neurology ward
- Source Evidence
- •AAN/MGFA International Consensus Guidance for Management of Myasthenia Gravis (2021 update)
- •EFNS/EAN Guidelines on the Treatment of Autoimmune Neuromuscular Transmission Disorders
- •Cochrane Review — Plasma Exchange and IVIG for Myasthenia Gravis Exacerbations
- •Neurocritical Care Society guidance on neuromuscular respiratory failure
Key Clinical Takeaways
Effective myasthenic crisis management turns on a single clinical truth: the danger is respiratory, and it arrives before oxygen saturation falls. A crisis is the point at which weakness in a patient with myasthenia gravis threatens the airway or ventilation enough to require respiratory support. The points below distill the evidence into actionable rules for the bedside, the emergency department, and the intensive care unit.
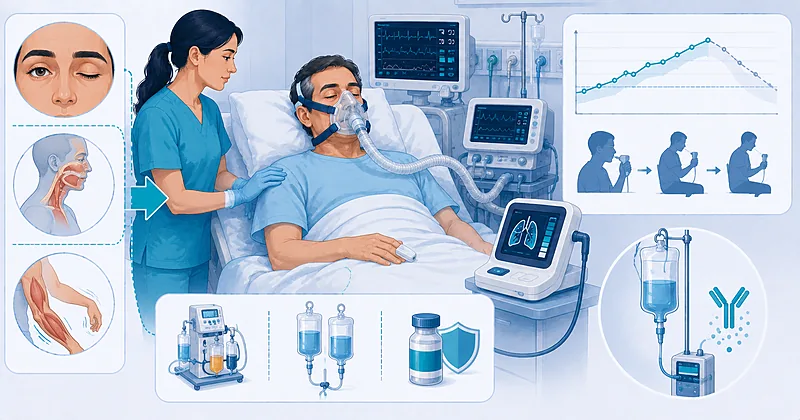
- 1Track serial bedside spirometry, not pulse oximetry — a normal oxygen saturation can persist until moments before respiratory arrest → Recognizing Failure
- 2Treat the “20/30/40” thresholds as triggers to escalate care, not as the moment intubation has already become unavoidable → Recognizing Failure
- 3Consider non-invasive ventilation early in the deteriorating patient, before hypercapnia, to potentially avoid intubation → Airway Decisions
- 4Start either plasma exchange or intravenous immunoglobulin promptly — both are effective rescue immunotherapy for crisis → Rescue Immunotherapy
- 5Begin or continue corticosteroids, but anticipate a possible transient worsening of weakness in the first one to two weeks → Immunosuppression
- 6Hunt for the trigger — infection, aspiration, surgery, or a culprit drug underlies most crises and changes the plan → Finding the Trigger
- 7Hold or reduce high-dose cholinesterase inhibitors in the intubated patient to cut secretions and avoid cholinergic excess → Avoiding Pitfalls
- 8Plan extubation around objective respiratory recovery and secretion control, not simply on improved limb strength → Monitoring
Recognizing Respiratory Failure in Myasthenic Crisis Management
The first skill in myasthenic crisis management is noticing trouble before the patient looks distressed. Neuromuscular respiratory failure is insidious: the lungs are healthy, gas exchange is preserved until late, and a comfortable-appearing patient can decompensate within hours. Bedside respiratory mechanics give the earliest warning.
Monitor serial forced vital capacity and maximal inspiratory and expiratory pressures every two to four hours in any patient with worsening generalized or bulbar weakness. Falling or fluctuating values are more informative than any single reading.
Strong Rec Moderate Evidence AAN/MGFA 2021Do not rely on pulse oximetry or arterial blood gas to detect early decline. Both stay reassuring until ventilatory reserve is nearly exhausted, by which point intervention is urgent rather than elective.
Against Moderate Evidence Neurocritical Care SocietyEvaluate bulbar function directly: ask the patient to count aloud on a single breath, watch for a weak or wet cough, and assess swallowing. Bulbar weakness predicts aspiration and airway loss independently of vital capacity.
Moderate Rec Low Evidence AAN/MGFA 2021Bedside Respiratory Thresholds That Should Prompt Escalation
The figures below are escalation triggers, not guarantees. A patient trending toward them on serial testing warrants intensive monitoring and an early airway conversation, framed by overall trajectory and bulbar status rather than one number in isolation.
| Bedside Measure | Escalation Trigger (Approx.) | What It Reflects | Practical Pitfall |
|---|---|---|---|
| Forced vital capacity | Below ~20 mL/kg, or a rapid downward trend | Overall ventilatory reserve and tidal capacity | Facial weakness breaks the mouth seal and falsely lowers values — note seal quality |
| Maximal inspiratory pressure | Weaker than about −30 cm H₂O | Inspiratory (diaphragm) strength | Effort-dependent; coach the patient and take the best of several attempts |
| Maximal expiratory pressure | Below about 40 cm H₂O | Cough and secretion-clearing strength | A weak cough drives aspiration risk even when oxygenation looks fine |
| Single-breath count | Unable to reach ~20 | A rough proxy for vital capacity at the bedside | Useful for trends; not a substitute for a measured value |
Airway and Ventilation Decisions
Once deterioration is recognized, the central question becomes how to support ventilation: a trial of non-invasive support, or definitive intubation. The right answer depends on bulbar function, secretion burden, carbon dioxide retention, and how fast the patient is falling.
Consider a trial of non-invasive ventilation in the deteriorating but cooperative patient with manageable secretions and without established hypercapnia. Early use may avert intubation in a meaningful share of patients.
Moderate Rec Moderate Evidence Neurocritical Care SocietyDo not attempt non-invasive ventilation when bulbar weakness is severe, secretions are uncontrolled, consciousness is impaired, or carbon dioxide is already rising. In these settings it delays a necessary definitive airway and raises aspiration risk.
Against Low Evidence Neurocritical Care SocietyPerform endotracheal intubation without further delay when the patient cannot protect the airway, fails or cannot tolerate non-invasive support, retains carbon dioxide, or continues to decline. A controlled, planned intubation is safer than an emergent one.
Strong Rec Low Evidence AAN/MGFA 2021Avoid depolarizing and non-depolarizing neuromuscular blockers where possible, and reduce doses substantially when paralysis for intubation is unavoidable. Patients with myasthenia are resistant to depolarizing agents and markedly sensitive to non-depolarizing ones, with prolonged, unpredictable effect.
Conditional Rec Low Evidence EFNS/EANRescue Immunotherapy in Myasthenic Crisis Management
Respiratory support buys time; rescue immunotherapy treats the disease. The two pillars of acute myasthenic crisis management are therapeutic plasma exchange and intravenous immunoglobulin. Major guidance bodies regard them as broadly comparable in efficacy for crisis, so the choice usually turns on the individual patient and local logistics.
Initiate plasma exchange or intravenous immunoglobulin promptly once crisis is established. Do not wait for the patient to fail before starting; earlier treatment shortens the time on ventilatory support.
Strong Rec High Evidence AAN/MGFA 2021 CochranePrefer plasma exchange when a faster response is the priority, when the antibody burden is high, or when immunoglobulin is contraindicated. Onset is often perceived as quicker, though it requires adequate venous access and hemodynamic tolerance.
Moderate Rec Moderate Evidence EFNS/EANPrefer intravenous immunoglobulin when vascular access is poor, hemodynamic instability makes apheresis risky, or sepsis is present. It is simpler to deliver on a general ward and avoids extracorporeal circuit complications.
Moderate Rec Moderate Evidence CochraneDo not routinely combine plasma exchange and immunoglobulin in the same episode expecting additive benefit. If plasma exchange follows immunoglobulin too closely, it can remove the just-infused antibody and waste the treatment.
Against Low Evidence EFNS/EANChoosing Between the Two Rescue Therapies
| Patient Situation | Leans Toward Plasma Exchange | Leans Toward Immunoglobulin | Watch-For Adverse Effect |
|---|---|---|---|
| Speed needed | Often perceived as faster onset | Onset over several days | PLEX: transient post-procedure weakness as proteins shift |
| Vascular access | Needs large-bore or central access | Peripheral line suffices | IVIG: headache, aseptic meningitis |
| Hemodynamics | Requires hemodynamic tolerance | Better tolerated if unstable | PLEX: hypotension, citrate hypocalcemia |
| Comorbidity | Caution with coagulopathy, sepsis | Caution with renal impairment, thrombosis risk | IVIG: acute kidney injury, thromboembolism, volume load |
| Logistics | Needs apheresis service and trained staff | Deliverable on most wards | Confirm IgA status to gauge anaphylaxis risk |
Seronegative status does not exclude a true crisis, and acetylcholine receptor antibody titres do not track severity closely enough to guide acute decisions. When a patient fails to respond to first-line rescue immunotherapy, reconsider the diagnosis, search again for an untreated trigger, and involve a neuromuscular specialist early regarding escalation, including complement-directed or other targeted agents in selected refractory cases.
Corticosteroids, Cholinesterase Inhibitors, and Trigger Control
Alongside rescue immunotherapy, the acute plan must address longer-acting immunosuppression, careful handling of symptomatic drugs, and the precipitant that tipped the patient into crisis.
Start or continue corticosteroids as the backbone of acute immunosuppression, ideally once respiratory support and rescue immunotherapy are in place. Anticipate a possible early steroid-induced worsening of weakness within roughly one to two weeks of a high starting dose.
Moderate Rec Low Evidence AAN/MGFA 2021Hold or substantially reduce cholinesterase inhibitors in the intubated patient. High doses increase airway and gastrointestinal secretions and add little once mechanical ventilation is established, while raising the risk of cholinergic excess.
Moderate Rec Low Evidence EFNS/EANIdentify and treat the precipitant in every case. Investigate for respiratory or other infection, aspiration, recent surgery, pregnancy, tapering of immunotherapy, and newly started drugs known to unmask weakness.
Strong Rec Low Evidence AAN/MGFA 2021Review the medication chart against agents that worsen neuromuscular transmission, including certain antibiotics, magnesium, and some cardiac and immunomodulatory drugs. Stop or substitute the offending agent where the indication allows.
Strong Rec Low Evidence EFNS/EANCommon Drug Triggers to Review on Admission
| Drug Group | Representative Examples | Practical Action |
|---|---|---|
| Aminoglycoside / macrolide / fluoroquinolone antibiotics | Gentamicin, azithromycin, ciprofloxacin | Use only if no safer alternative; monitor respiratory status closely |
| Magnesium | IV magnesium sulfate, high-dose oral magnesium | Avoid parenteral loading unless strongly indicated; correct cautiously |
| Cardiac agents | Beta-blockers, certain antiarrhythmics | Weigh cardiac benefit against neuromuscular risk; watch for worsening |
| Immune checkpoint inhibitors | Anti-PD-1 and related oncology agents | Recognize as a potent precipitant; coordinate urgently with oncology |
- This list is a prompt for review, not exhaustive — cross-check any new drug against a current reference before starting it in a patient with myasthenia.
Clinical Decision Pathway
A practical, question-based approach to the patient with suspected crisis. Work through the questions in order, reassessing after each step.
Monitoring, Weaning, and Recovery
Recovery is judged on objective respiratory function and secretion control, not limb strength alone. The patient whose arms feel stronger but whose cough is still weak is not yet ready to leave the ventilator.
| What to Track | When | Sign of Progress | Common Pitfall |
|---|---|---|---|
| Vital capacity and inspiratory pressure | At least daily, more often if unstable | Steady, sustained upward trend | Extubating on a single good reading rather than a trend |
| Cough and secretion clearance | Each assessment before weaning | Effective cough, decreasing suctioning need | Overlooking secretion load while focusing on oxygenation |
| Response to rescue therapy | Over the days after PLEX or IVIG | Improving bulbar and respiratory function | Expecting an instant response and abandoning therapy too early |
| Signs of cholinergic excess | Whenever cholinesterase inhibitors are resumed | No hypersalivation, cramps, or fasciculations | Mistaking cholinergic crisis for under-treatment and adding more drug |
Evidence in Context
What the evidence supports, where major guidance converges, and where uncertainty remains.
Plasma Exchange Versus Immunoglobulin: What Trials Show
Randomized comparisons and systematic reviews have not established a clear winner for severe exacerbation and crisis. Both therapies improve strength over the following days, and guidance bodies treat them as broadly equivalent in efficacy, leaving the decision to patient factors and local capability rather than a proven superiority of one over the other.
Where AAN/MGFA and EFNS/EAN Agree
Both frameworks treat crisis as a medical emergency centred on respiratory monitoring, endorse plasma exchange and immunoglobulin as first-line rescue therapy, and recommend early identification of triggers alongside attention to the special anesthetic considerations of myasthenia.
Where Practice Still Varies
The exact respiratory thresholds for intubation, the role and intensity of non-invasive ventilation, and the timing of high-dose steroids relative to rescue therapy differ between centres and remain matters of expert judgement rather than high-certainty evidence.
The Emerging Role of Targeted Agents
Complement inhibitors and neonatal Fc receptor antagonists have changed maintenance therapy for refractory disease, but their place in acute crisis is still being defined. In a refractory crisis, decisions about these agents should involve a neuromuscular specialist rather than following a fixed protocol.
References
- 1.Narayanaswami P, Sanders DB, Wolfe G, et al. International Consensus Guidance for Management of Myasthenia Gravis: 2020 Update. Neurology. 2021;96(3):114–122. doi:10.1212/WNL.0000000000011124
- 2.Gilhus NE, Skeie GO, Romi F, et al. Myasthenia gravis — autoantibody characteristics and their implications for therapy. Nat Rev Neurol. 2016;12(5):259–268. doi:10.1038/nrneurol.2016.44
- 3.Gajdos P, Chevret S, Toyka KV. Plasma exchange for generalised myasthenia gravis. Cochrane Database Syst Rev. 2002;(4):CD002275. doi:10.1002/14651858.CD002275
- 4.Gajdos P, Chevret S, Toyka KV. Intravenous immunoglobulin for myasthenia gravis. Cochrane Database Syst Rev. 2012;12:CD002277. doi:10.1002/14651858.CD002277.pub4
- 5.Wendell LC, Levine JM. Myasthenic crisis. Neurohospitalist. 2011;1(1):16–22. doi:10.1177/1941875210382918
How to Read the Evidence Tags
Every recommendation carries tags for recommendation strength and evidence quality — Medaptly’s own simplified interpretation, not the classification system of any single guideline body. For full grading definitions, consult the original sources listed in References.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |