
Neuromyelitis Optica Spectrum Disorder: Diagnosis and Therapy
Clinical Practice Update — Serologic Diagnosis, Acute Attack Rescue, and Targeted Immunosuppression in Adults
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Diagnosis and long-term immunosuppression of neuromyelitis optica spectrum disorder in adults
- Target Audience
- Neurologists, ophthalmologists, emergency physicians, hospitalists, residents
- Setting
- Neurology clinics, emergency departments, hospital inpatient, infusion centers
- Source Evidence
- •IPND International Consensus Diagnostic Criteria for NMOSD (Wingerchuk et al., 2015)
- •NEMOS Recommendations on NMOSD Management (Parts 1 & 2, 2023–2024)
- •PREVENT Trial — Eculizumab in AQP4-IgG+ NMOSD (NEJM, 2019)
- •N-MOmentum Trial — Inebilizumab (Lancet, 2019)
- •SAkuraSky & SAkuraStar Trials — Satralizumab (NEJM & Lancet Neurology, 2019–2020)
- •CHAMPION-NMOSD Trial — Ravulizumab (Annals of Neurology, 2023)
Key Clinical Takeaways
Effective NMOSD treatment rests on a single principle: every attack can leave permanent disability, so the goals are rapid, accurate diagnosis and durable relapse prevention. Confirming aquaporin-4 antibody status with a cell-based assay, treating acute attacks aggressively, and starting targeted immunosuppression early are the three decisions that change outcomes. The points below distill the evidence into rules you can apply from first presentation onward.
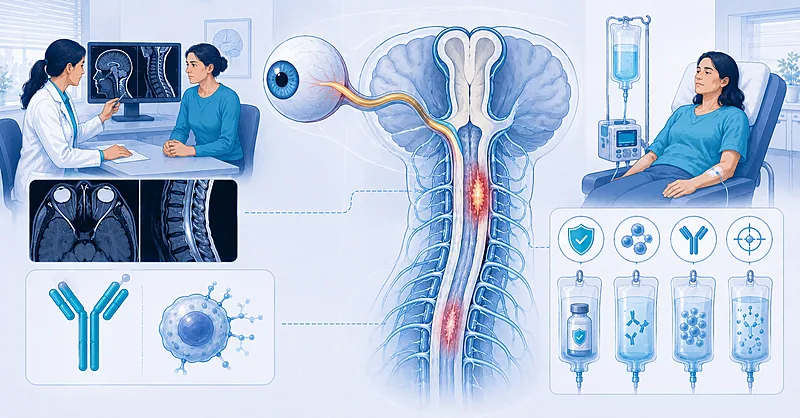
- 1Test serum AQP4-IgG with a cell-based assay in every patient with optic neuritis, myelitis, or area postrema syndrome — it is the single most decisive diagnostic step
- 2A longitudinally extensive cord lesion spanning three or more vertebral segments points strongly toward NMOSD rather than multiple sclerosis
- 3Start high-dose intravenous methylprednisolone the day an attack is recognized — delay measurably worsens recovery
- 4Escalate to plasma exchange early when steroids fail — roughly half of severe attacks need it, and earlier exchange improves visual and motor outcomes
- 5Begin relapse-preventing immunosuppression as soon as the diagnosis is secure — do not wait for a second attack
- 6Four monoclonal antibodies are now FDA-approved for AQP4-IgG+ disease: eculizumab, ravulizumab, inebilizumab, and satralizumab
- 7Vaccinate against meningococcus before any complement inhibitor — C5 blockade markedly raises meningococcal risk
- 8Avoid MS disease-modifying drugs — interferons, natalizumab, fingolimod, and others can worsen NMOSD
- 9Approved biologics outperform older agents on relapse-free survival, but rituximab, mycophenolate, and azathioprine remain important where access is limited
Confirming the Diagnosis Before NMOSD Treatment Begins
NMOSD treatment hinges on a correct diagnosis because several therapies that help multiple sclerosis actively harm NMOSD. The diagnostic framework integrates a core clinical event, serologic status, and supportive imaging. Antibody status splits the disease into two streams: AQP4-IgG seropositive disease, which carries all four drug approvals, and seronegative disease, which requires stricter clinical and radiologic criteria.
Perform serum AQP4-IgG testing by cell-based assay in any adult presenting with optic neuritis, acute myelitis, or area postrema syndrome with intractable hiccups or vomiting. Cell-based assays offer the highest sensitivity and near-complete specificity among available methods.
Strong Rec High Evidence IPND 2015 NEMOS 2023Test serum in preference to cerebrospinal fluid, and draw the sample before plasma exchange or high-dose steroids when feasible, since both can lower antibody titers and produce false-negative results.
Moderate Rec Moderate Evidence NEMOS 2023Evaluate for MOG-IgG when AQP4-IgG returns negative but the clinical picture still suggests an antibody-mediated demyelinating syndrome. MOG-associated disease is a distinct entity with its own course and treatment, and conflating it with NMOSD misdirects therapy.
Moderate Rec Moderate Evidence NEMOS 2023Obtain MRI of the brain and full spine with and without gadolinium. A longitudinally extensive lesion crossing three or more contiguous vertebral segments, periependymal brain involvement, or dorsal medulla lesions support NMOSD and argue against multiple sclerosis.
Strong Rec Moderate Evidence IPND 2015Apply the stricter seronegative criteria when antibody testing is negative: at least two core clinical events meeting dissemination requirements, one of which must be optic neuritis, longitudinally extensive myelitis, or area postrema syndrome, plus supportive MRI features.
Moderate Rec Low Evidence IPND 2015Acute Attack Rescue in NMOSD Treatment
Acute NMOSD treatment is a neurological emergency. Each attack carries the risk of irreversible blindness or paralysis, and the window to limit damage is short. The strategy is to suppress inflammation immediately with corticosteroids and to remove circulating antibody with apheresis when the response is incomplete.
Start intravenous methylprednisolone 1 g daily for three to five consecutive days at the first recognition of an acute attack. Faster initiation correlates with better visual recovery after optic neuritis, so treatment should not wait for serologic confirmation.
Strong Rec Moderate Evidence NEMOS 2023Perform plasma exchange when an attack responds poorly to steroids, typically five exchanges over seven to ten days. About half of severe attacks need apheresis, and shorter time from onset to first exchange predicts better visual and motor recovery.
Strong Rec Moderate Evidence NEMOS 2023Consider plasma exchange alongside corticosteroids from the outset, rather than only after steroid failure, in attacks that threaten vision or are accompanied by dense paraparesis. Early combined treatment is increasingly favored for the most severe presentations.
Conditional Rec Low Evidence NEMOS 2023Follow the steroid course with an oral taper over two to eight weeks in patients with severe or incomplete recovery, bridging the gap until maintenance immunosuppression takes effect and reducing the risk of early rebound.
Moderate Rec Low Evidence NEMOS 2023Maintenance Immunosuppression: The Core of NMOSD Treatment
Long-term immunosuppression is where NMOSD treatment is won or lost. Because more than nine in ten patients follow a relapsing course and disability accrues attack by attack, preventive therapy should start as soon as the diagnosis is confirmed and continue indefinitely. Four targeted biologics now hold FDA approval for seropositive disease, each striking a different point in the immune cascade.
Complement Inhibition
Initiate eculizumab, a terminal complement C5 inhibitor, in adults with AQP4-IgG+ disease. In its pivotal trial, eculizumab cut adjudicated relapse risk by roughly 94% versus placebo, and long-term follow-up found most patients relapse-free at four years. Maintenance requires intravenous dosing every two weeks.
Strong Rec High Evidence PREVENT 2019Prescribe ravulizumab as a longer-acting C5 inhibitor for patients who want less frequent infusions. In CHAMPION-NMOSD, no treated patient relapsed during the primary period, yielding a relapse risk reduction near 99% against an external placebo, with maintenance every eight weeks after loading.
Strong Rec Moderate Evidence CHAMPION 2023Vaccinate every patient against Neisseria meningitidis at least two weeks before the first complement inhibitor dose, and provide antibiotic prophylaxis if therapy must begin sooner. Terminal complement blockade substantially raises the risk of meningococcal infection.
Strong Rec High Evidence FDA LabelB-Cell Depletion and IL-6 Blockade
Initiate inebilizumab, an anti-CD19 monoclonal that depletes a broad B-cell range, for seropositive adults. In N-MOmentum it lowered relapse risk by roughly 77% overall and near 79% in seropositive patients, and also reduced disability worsening. Maintenance is a single infusion every six months after loading.
Strong Rec High Evidence N-MOmentum 2019Offer satralizumab, an IL-6 receptor antagonist, when a subcutaneous self-administered option is preferred. In its seropositive trial subgroups it reduced relapse risk by roughly 74% as monotherapy and 79% when added to baseline immunosuppression, dosed every four weeks after loading.
Strong Rec High Evidence SAkura 2019–2020Do not use approved complement inhibitors or satralizumab as the basis for a seronegative treatment decision expecting trial-level benefit. The pivotal programs enrolled predominantly or exclusively seropositive patients, and efficacy in seronegative disease is unproven.
Against Moderate Evidence N-MOmentum 2019Off-Label Agents Where Access Is Limited
Use rituximab as an off-label B-cell depleting option when approved biologics are unavailable. Real-world data place its five-year relapse-free survival near 70% — below the approved agents but well above older oral immunosuppressants — making it a widely used and reasonable alternative.
Moderate Rec Moderate Evidence NEMOS 2024Consider mycophenolate mofetil or azathioprine as oral alternatives in resource-limited settings, bridging with corticosteroids for the first several weeks while the agent reaches effect. Both leave a meaningful residual relapse rate, so monitor closely and escalate if breakthrough attacks occur.
Conditional Rec Moderate Evidence NEMOS 2024Do not prescribe multiple-sclerosis disease-modifying therapies — interferon-beta, natalizumab, fingolimod, dimethyl fumarate, and alemtuzumab — in NMOSD. Several are ineffective and some provoke severe relapses, which is precisely why securing the antibody diagnosis first matters so much.
Against Moderate Evidence NEMOS 2023Clinical Decision Pathway
A practical, question-based route through diagnosis and the start of long-term therapy. Work through the questions in order.
Matching Maintenance Therapy to the Patient
The four approved agents are all highly effective in seropositive disease, so selection often turns on mechanism, dosing burden, and the safety conversation rather than relative efficacy. This table organizes them by what tends to matter most to patients.
| Agent | Mechanism | Maintenance Interval | Best Suited For | Key Safety Watch-Point |
|---|---|---|---|---|
| Eculizumab | C5 complement inhibitor | IV every 2 weeks | Highest-risk patients needing rapid, profound protection | Meningococcal infection — vaccinate first |
| Ravulizumab | Long-acting C5 inhibitor | IV every 8 weeks | Complement-pathway protection with lower infusion burden | Meningococcal infection — vaccinate first |
| Inebilizumab | Anti-CD19 B-cell depletion | IV every 6 months | Patients prioritizing the fewest annual visits | Hypogammaglobulinemia, infection over time |
| Satralizumab | IL-6 receptor antagonist | Subcutaneous every 4 weeks | Patients who prefer self-administration at home | Masked infection signs, liver enzyme rise |
| Rituximab (off-label) | Anti-CD20 B-cell depletion | IV every ~6 months | Settings without access to approved biologics | Infusion reactions, residual relapse risk |
Monitoring and Follow-Up
Once therapy is underway, surveillance shifts to catching breakthrough activity early and managing the infection risk that comes with sustained immunosuppression. The schedule below frames monitoring around what to check, when, and the mistakes that catch teams out.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| New or worsening symptoms | At every visit; patient-initiated between visits | Visual change, weakness, sensory level, bladder dysfunction | Attributing a true attack to a benign symptom flare and delaying steroids |
| Infection screen and vaccines | Before therapy, then ongoing | Meningococcal cover for C5 inhibitors; baseline hepatitis and TB | Starting a complement inhibitor before vaccination is documented |
| Immunoglobulin levels | Baseline, then periodically on B-cell therapy | Falling IgG predicting infection susceptibility | Overlooking gradual hypogammaglobulinemia on long-term depletion |
| Liver enzymes and counts | Per agent schedule | Transaminase rise with IL-6 blockade; cytopenias with oral agents | IL-6 blockade can mask fever and blunt CRP, hiding infection |
Evidence in Context
What the trials established, where the data are strong, and where they leave open questions.
Why Seropositive and Seronegative Disease Diverge
Every pivotal maintenance trial was built around AQP4-IgG seropositive patients. Where seronegative patients were included, numbers were small and benefit did not reach significance. As a result, all four approvals are restricted to seropositive disease, and seronegative management leans on off-label agents and expert judgment.
Comparing Across Trials Is Difficult
The headline relapse-reduction figures are not directly comparable because the trials differed in design, background therapy, and relapse adjudication. CHAMPION-NMOSD used an external placebo comparison borrowed from the eculizumab trial because a fresh placebo arm was deemed unethical once effective therapy existed. Cross-trial percentages should guide expectations, not rank the drugs.
Approved Biologics Versus Older Agents
Recent real-world cohorts report markedly higher relapse-free survival with approved biologics and rituximab than with mycophenolate or azathioprine. Older oral agents leave a substantial fraction of patients relapsing within five years, which is the central argument for moving to targeted therapy wherever access allows.
Relapse Prevention Does Not Equal Disability Prevention
Even in trials where treated patients had essentially no relapses, a small minority still showed disability worsening. This reinforces that attack prevention, while central, is not the whole picture, and that rehabilitation and symptomatic care remain part of comprehensive management.
References
- 1.Wingerchuk DM, Banwell B, Bennett JL, et al. International consensus diagnostic criteria for neuromyelitis optica spectrum disorders. Neurology. 2015;85(2):177–189. doi:10.1212/WNL.0000000000001729
- 2.Pittock SJ, Berthele A, Fujihara K, et al. Eculizumab in aquaporin-4–positive neuromyelitis optica spectrum disorder. N Engl J Med. 2019;381(7):614–625. doi:10.1056/NEJMoa1900866
- 3.Cree BAC, Bennett JL, Kim HJ, et al. Inebilizumab for the treatment of neuromyelitis optica spectrum disorder (N-MOmentum): a double-blind, randomised placebo-controlled phase 2/3 trial. Lancet. 2019;394(10206):1352–1363. doi:10.1016/S0140-6736(19)31817-3
- 4.Yamamura T, Kleiter I, Fujihara K, et al. Trial of satralizumab in neuromyelitis optica spectrum disorder. N Engl J Med. 2019;381(22):2114–2124. doi:10.1056/NEJMoa1901747
- 5.Pittock SJ, Barnett M, Bennett JL, et al. Ravulizumab in aquaporin-4–positive neuromyelitis optica spectrum disorder (CHAMPION-NMOSD). Ann Neurol. 2023;93(6):1053–1068. doi:10.1002/ana.26626
- 6.Kümpfel T, Giglhuber K, Aktas O, et al. Update on the diagnosis and treatment of neuromyelitis optica spectrum disorders (NMOSD) – revised recommendations of the Neuromyelitis Optica Study Group (NEMOS). J Neurol. 2024;271(1):141–176. doi:10.1007/s00415-023-11910-z
How to Read the Evidence Tags
Each recommendation carries two tags for recommendation strength and evidence quality — Medaptly’s own simplified interpretations, not any guideline body’s classification system.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | The benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |