
Adolescent Obesity Treatment: 8 Essential AAP Pathway Steps
Clinical Practice Update — Intensive Lifestyle Therapy, Pharmacotherapy, and Bariatric Referral
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based adolescent obesity treatment in patients aged 12–18 years
- Target Audience
- Pediatricians, family physicians, pediatric endocrinologists, advanced practice nurses
- Setting
- Primary care, pediatric weight management clinics, multidisciplinary obesity centers
- Source Evidence
- •AAP Clinical Practice Guideline for the Evaluation and Treatment of Children and Adolescents With Obesity (2023)
- •STEP TEENS Trial — Semaglutide in Adolescents With Obesity (NEJM 2022)
- •ASMBS Pediatric Metabolic and Bariatric Surgery Guidelines (2018)
- •Endocrine Society Clinical Practice Guideline on Pediatric Obesity (2017)
Key Clinical Takeaways
Modern adolescent obesity treatment is no longer a watch-and-wait exercise. The updated AAP pathway pushes clinicians to act early, treat the disease at the highest level of available care, and combine intensive lifestyle therapy with medication or surgery when indicated. The points below distill that pathway into actionable steps for routine practice.
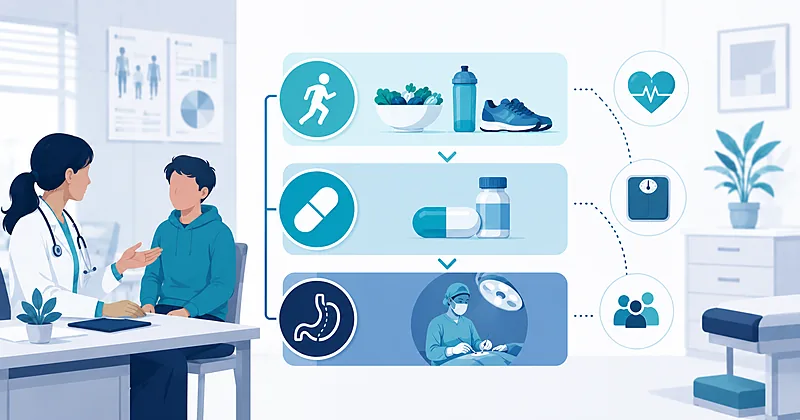
- 1Calculate BMI at every well-adolescent visit and treat any BMI at or above the 95th percentile as obesity warranting active management → Identifying Patients
- 2Screen every adolescent with obesity for the standard set of cardiometabolic and mental-health comorbidities at diagnosis
- 3Offer intensive health behavior and lifestyle treatment (IHBLT) totalling at least 26 contact hours over 3–12 months as the cornerstone of care → Intensive Lifestyle
- 4Add an FDA-approved anti-obesity medication for adolescents aged 12 and older when lifestyle therapy alone is insufficient → Pharmacotherapy
- 5Consider weekly subcutaneous semaglutide as the most effective approved option, with around 16% mean BMI reduction in trials
- 6Refer adolescents aged 13 and older with class III obesity or class II obesity plus a serious comorbidity for evaluation at a comprehensive metabolic and bariatric surgery program → Bariatric Referral
- 7Discard the practice of “watchful waiting” — delay measurably worsens outcomes and rarely reverses on its own
- 8Use motivational interviewing throughout, addressing the family unit and avoiding stigmatising language at every visit → Intensive Lifestyle
Identifying Adolescents Who Need Treatment
Adolescent obesity treatment begins with consistent measurement and accurate classification. Roughly one in five US adolescents now meets criteria for obesity, and a growing share fall into the severe categories that demand more aggressive intervention than lifestyle counselling alone.
Calculate BMI percentile at every well-adolescent visit using the CDC age- and sex-specific growth charts, and plot the trajectory rather than relying on a single value.
Strong Rec High Evidence AAP 2023Classify obesity into clinically meaningful tiers: class I (BMI ≥ 95th percentile), class II (≥ 120% of the 95th percentile or BMI ≥ 35), and class III (≥ 140% of the 95th percentile or BMI ≥ 40). The class determines the intensity of adolescent obesity treatment offered.
Strong Rec High Evidence AAP 2023Evaluate every adolescent diagnosed with obesity for the standard cardiometabolic comorbidity set at diagnosis: fasting lipid panel, ALT, fasting glucose or HbA1c, and blood pressure at the appropriate cuff size.
Strong Rec High Evidence AAP 2023Perform additional type 2 diabetes screening with a fasting glucose, 2-hour OGTT, or HbA1c in any adolescent with BMI ≥ 95th percentile plus at least one additional risk factor (family history, high-risk ethnicity, signs of insulin resistance, or maternal gestational diabetes).
Strong Rec Moderate Evidence AAP 2023Ask routinely about symptoms of obstructive sleep apnea, depression, anxiety, eating disorders, and bullying. Each is over-represented in adolescent obesity and changes the treatment plan.
Strong Rec Moderate Evidence AAP 2023Evaluate for a secondary or syndromic cause when obesity is severe, of early onset (before age 5), associated with hyperphagia from infancy, or accompanied by developmental delay or dysmorphic features.
Moderate Rec Low Evidence Endocrine Society 2017Intensive Lifestyle Treatment for Adolescent Obesity
Intensive health behavior and lifestyle treatment (IHBLT) is the foundation on which every other component of adolescent obesity treatment is built. Brief in-office counselling at routine visits is not enough; the evidence supports a structured, family-based, high-contact program delivered over several months.
Offer or refer every adolescent aged 12 and older with BMI at or above the 95th percentile to an IHBLT program delivering at least 26 contact hours over 3–12 months. This is the strongest non-medication intervention in adolescent obesity treatment.
Strong Rec High Evidence AAP 2023 USPSTF 2017Engage the entire family, not just the adolescent, in the IHBLT program. Family-based behavioral intervention outperforms adolescent-only formats in head-to-head trials.
Strong Rec High Evidence AAP 2023Use motivational interviewing as the consultation framework. Confrontational or weight-shaming language reliably worsens engagement and is associated with binge-eating behaviors.
Moderate Rec Moderate Evidence AAP 2023Counsel adolescents and families on a balanced eating pattern that limits sugar-sweetened beverages, prioritises vegetables and whole foods, and preserves three meals daily with planned snacks. Avoid prescribing rigid calorie counts.
Moderate Rec Moderate Evidence AAP 2023Prescribe at least 60 minutes of moderate-to-vigorous physical activity on most days, plus muscle-strengthening activity three days a week. Begin where the patient is — many adolescents with severe obesity cannot reach 60 minutes at the start.
Strong Rec Moderate Evidence AAP 2023Address sleep duration and screen time directly at every visit — both are independently associated with weight gain in adolescents and respond to specific, written family agreements.
Moderate Rec Moderate Evidence AAP 2023Do not delay escalation to medication or surgical evaluation while waiting for lifestyle therapy to “work.” The updated AAP pathway frames IHBLT as the foundation of every tier — not a prerequisite to be completed first.
Against Moderate Evidence AAP 2023Pharmacotherapy in Adolescent Obesity Treatment
A major change in adolescent obesity treatment is the formal endorsement of anti-obesity medication as an adjunct to lifestyle therapy in patients aged 12 and older. The medication menu has expanded substantially, and the FDA-approved options now include agents with weight-loss efficacy that approaches what was previously only possible with surgery.
Offer pharmacotherapy as an adjunct to IHBLT for any adolescent aged 12 or older with obesity (BMI ≥ 95th percentile) when lifestyle therapy alone has not produced sufficient improvement after 3–6 months, or upfront when severity warrants it.
Strong Rec Moderate Evidence AAP 2023Prescribe weekly subcutaneous semaglutide 2.4 mg as the first-line anti-obesity medication for most adolescents based on the largest absolute weight effect seen in published trials.
Moderate Rec High Evidence STEP TEENS 2022Initiate the GLP-1 receptor agonist at a low dose with a planned monthly titration, and counsel families that the first 4–8 weeks of nausea typically settle.
Strong Rec High Evidence FDA labellingConsider once-daily phentermine/topiramate ER as an alternative or step-up agent when GLP-1 access is limited. Excellent contraceptive counselling is essential before starting because of teratogenicity risk.
Moderate Rec Moderate Evidence FDA labellingConsider daily liraglutide as a GLP-1 alternative when weekly dosing is impractical, accepting somewhat lower mean weight effect than weekly semaglutide.
Moderate Rec High Evidence FDA labellingRefer adolescents with confirmed rare genetic causes (POMC, LEPR, PCSK1 deficiency, Bardet-Biedl syndrome) to a center able to prescribe setmelanotide. These patients respond poorly to standard anti-obesity medications.
Conditional Rec Low Evidence Endocrine Society 2017Discontinue an anti-obesity medication if the adolescent has not lost > 4% of body weight after 12 weeks at the maximum tolerated dose, or if intolerable adverse effects occur.
Moderate Rec Low Evidence AAP 2023Do not use anti-obesity medication in isolation. Continue IHBLT for as long as the medication is prescribed; weight rebound after stopping pharmacotherapy is the rule, not the exception.
Against Moderate Evidence AAP 2023Anti-Obesity Medications: A Drug-by-Drug Comparison
| Drug | Approved Age | Typical Dose | Mean BMI Effect | Practical Counselling Points |
|---|---|---|---|---|
| Semaglutide (Wegovy) | ≥ 12 | 2.4 mg SC weekly (titrated over 16 weeks) | ~16% BMI reduction vs placebo | Nausea peaks during titration. Avoid with personal/family history of MTC or MEN2. |
| Liraglutide (Saxenda) | ≥ 12 | 3.0 mg SC daily | ~5% BMI reduction vs placebo | Daily injection burden; better tolerated if escalated weekly. |
| Phentermine/topiramate ER (Qsymia) | ≥ 12 | Start 3.75/23 mg PO daily; titrate to 15/92 mg | ~7–10% BMI reduction at top dose | Teratogenic — confirm contraception. Watch for paresthesias, mood change. |
| Orlistat (Xenical) | ≥ 12 | 120 mg PO TID with meals | ~2–3% BMI reduction | GI side effects often limit adherence. Supplement fat-soluble vitamins. |
| Phentermine | ≥ 16 | 15–37.5 mg PO daily, short-term | ~3–5% short-term | Controlled substance; screen for cardiovascular contraindications. |
| Setmelanotide | ≥ 6 (rare genetic) | SC daily, weight-based | Variable; only effective in specific genotypes | Restricted to specialty centers. Watch for skin pigmentation changes. |
Metabolic and Bariatric Surgery Referral
Metabolic and bariatric surgery is the most effective long-term intervention for severe obesity in adolescents. The updated AAP pathway explicitly endorses earlier referral than has been routine in many practices, citing evidence that surgical outcomes in adolescents match or exceed adult outcomes for both weight and comorbidity remission.
Refer adolescents aged 13 years and older with class III obesity (BMI ≥ 140% of the 95th percentile or BMI ≥ 40), or class II obesity (BMI ≥ 120% of the 95th percentile or BMI ≥ 35) plus a major comorbidity, to a comprehensive metabolic and bariatric surgery program.
Strong Rec High Evidence AAP 2023 ASMBS 2018Refer for evaluation, not for surgery itself. Decision-making belongs to the multidisciplinary surgical team, which assesses physical, psychological, and family-system readiness.
Strong Rec Moderate Evidence AAP 2023Do not require failure of intensive lifestyle therapy as a precondition for surgical referral when class III obesity is present. The data do not support waiting.
Against Moderate Evidence AAP 2023 ASMBS 2018Counsel families that vertical sleeve gastrectomy is now the most commonly performed adolescent procedure, with Roux-en-Y gastric bypass reserved for selected patients with severe metabolic disease.
Moderate Rec Moderate Evidence ASMBS 2018Plan for lifelong nutritional follow-up after bariatric surgery, including B12, iron, vitamin D, calcium, and (for RYGB) thiamine monitoring. Loss to follow-up is the most common avoidable surgical complication in this age group.
Strong Rec High Evidence ASMBS 2018Counsel female adolescents that pregnancy should be avoided for at least 12–18 months after surgery, and arrange reliable contraception (non-oral preferred after malabsorptive procedures) before referral.
Strong Rec Moderate Evidence ASMBS 2018Bariatric Procedures: Choosing Between Options
| Decision Point | Vertical Sleeve Gastrectomy | Roux-en-Y Gastric Bypass | Practical Discussion Point |
|---|---|---|---|
| Average weight effect at 5y | ~25–28% TBWL | ~28–30% TBWL | Both substantial; bypass marginally greater. |
| T2DM remission | High | Higher | Favors RYGB when diabetes is severe or insulin-dependent. |
| Reflux risk | May worsen | Often improves | Pre-existing severe GERD often shifts choice toward bypass. |
| Long-term nutritional risk | Lower | Higher | Adherence to supplements is the single biggest determinant of safety. |
| Reversibility | Not reversible | Anatomically reconfigurable | Discuss permanence explicitly with the adolescent. |
Clinical Decision Pathway
A practical, question-based pathway for adolescent obesity treatment. Move through each question in order; the answer determines the next step.
Monitoring and Follow-Up
Monitoring in adolescent obesity treatment is more than weighing the patient. The most useful follow-up tracks comorbidities, growth and pubertal progression, and the behavioral health domains that often determine whether the treatment plan succeeds.
| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| BMI percentile and %BMIp95 | Every 3 months during active treatment | Trajectory flattening or declining | Reading single BMI rather than the trend; using adult BMI cutoffs. |
| Fasting lipid panel | At diagnosis, then yearly | Non-HDL < 145, TG < 130 mg/dL | Forgetting non-HDL is the preferred screening metric. |
| HbA1c or fasting glucose | At diagnosis if risk factors; repeat every 2–3 years | Detect progression to prediabetes / T2DM | Underestimating speed of T2DM onset in adolescents. |
| ALT (non-alcoholic fatty liver disease screening) | Age 9–11 and any obesity-related visit thereafter | Sustained ALT > 2× ULN for sex | Using adult ALT cutoffs; missing referral threshold. |
| Blood pressure | Every visit, correct cuff size | BP percentile, confirm elevated on 3 occasions | Cuff too small inflates the value; ABPM is the confirmatory step. |
| Mood and disordered-eating screen | At diagnosis and at every escalation | PHQ-A ≥ 10 or any binge/purge symptoms | Skipping mental health screen before starting AOM. |
Reassess the full adolescent obesity treatment plan at minimum every 3 months during active intervention, with shared decision-making on whether to escalate, continue, or de-intensify.
Strong Rec Moderate Evidence AAP 2023Monitor growth and pubertal progression in addition to weight metrics. A flattening BMI in a still-growing adolescent represents excellent response that pure weight measurement misses.
Strong Rec Moderate Evidence AAP 2023Document weight bias mitigation explicitly: use person-first language (“adolescent with obesity”), use neutral equipment, and weigh patients in private. Bias in the clinic is a measured driver of treatment dropout.
Strong Rec Moderate Evidence AAP 2023Evidence in Context
Where the major sources for adolescent obesity treatment agree, where they differ, and how the most influential trials shape day-to-day practice.
Where AAP, ASMBS, and the Endocrine Society Agree
All three sources frame obesity as a chronic disease, endorse intensive lifestyle therapy as foundational, support pharmacotherapy in adolescents aged 12 and older when criteria are met, and recommend referral for surgical evaluation in adolescents with severe obesity. They share strong wording against weight-shaming language and against the prior practice of indefinite watchful waiting.
Where the Major Sources Differ
The AAP 2023 guideline is more explicit than older Endocrine Society guidance in endorsing earlier escalation to medication and surgery. The Endocrine Society document predates the modern GLP-1 trials and places more weight on a lifestyle-first sequencing. ASMBS focuses more narrowly on the surgical population and provides operational standards (center accreditation, multidisciplinary team composition) that the AAP guideline references rather than reproduces.
STEP TEENS — What the Semaglutide Trial Showed
STEP TEENS randomised 201 adolescents with obesity to weekly semaglutide 2.4 mg or placebo, on top of lifestyle counselling, for 68 weeks. The mean BMI change favored semaglutide by approximately 16 percentage points, with about three-quarters of treated adolescents losing at least 5% of body weight. Adverse events were mostly gastrointestinal during titration and largely resolved.
Teen-LABS — Long-Term Bariatric Outcomes in Adolescents
The Teen-LABS prospective cohort followed adolescents who underwent bariatric surgery for 5 years and beyond. Five-year follow-up data showed durable weight reduction and high rates of remission of type 2 diabetes and hypertension, with surgical safety profiles comparable to adult cohorts. These outcomes underpin the AAP recommendation to refer earlier.
Areas of Genuine Uncertainty
The optimal duration of anti-obesity medication in growing adolescents is unsettled. Most trials studied 1–2 years; longer-term skeletal, reproductive, and psychosocial outcomes are still being collected. The same caveat applies to bariatric surgery performed under age 16 — an area where individual benefits are clear but pediatric-specific late effects continue to be characterised.
References
- 1.Hampl SE, Hassink SG, Skinner AC, et al. Clinical Practice Guideline for the Evaluation and Treatment of Children and Adolescents With Obesity. Pediatrics. 2023;151(2):e2022060640. doi:10.1542/peds.2022-060640
- 2.Weghuber D, Barrett T, Barrientos-Pérez M, et al. Once-Weekly Semaglutide in Adolescents with Obesity. N Engl J Med. 2022;387(24):2245–2257. doi:10.1056/NEJMoa2208601
- 3.Pratt JSA, Browne A, Browne NT, et al. ASMBS pediatric metabolic and bariatric surgery guidelines, 2018. Surg Obes Relat Dis. 2018;14(7):882–901. doi:10.1016/j.soard.2018.03.019
- 4.Styne DM, Arslanian SA, Connor EL, et al. Pediatric Obesity-Assessment, Treatment, and Prevention: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2017;102(3):709–757. doi:10.1210/jc.2016-2573
- 5.Inge TH, Courcoulas AP, Jenkins TM, et al. Five-Year Outcomes of Gastric Bypass in Adolescents as Compared with Adults. N Engl J Med. 2019;380(22):2136–2145. doi:10.1056/NEJMoa1813909
- 6.US Preventive Services Task Force. Screening for Obesity in Children and Adolescents: US Preventive Services Task Force Recommendation Statement. JAMA. 2017;317(23):2417–2426. doi:10.1001/jama.2017.6803
How to Read the Evidence Tags
Every recommendation in this article carries two tags — one for recommendation strength and one for evidence quality — using Medaptly’s simplified interpretation.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favours this action. |
| Conditional Rec | Benefit is less certain — individualise. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |