
Pediatric Bacterial Meningitis: 8 Essential Empiric Steps
Clinical Practice Update — Age-Stratified Antibiotics, Dexamethasone, and Contact Prophylaxis in Children
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Empiric antibiotic selection, adjunctive dexamethasone, and post-exposure prophylaxis in suspected pediatric bacterial meningitis
- Target Audience
- Pediatricians, emergency physicians, neonatologists, hospitalists, family physicians, pediatric residents
- Setting
- Pediatric emergency departments, inpatient wards, NICU/PICU, primary care urgent referrals
- Source Evidence
- •NICE Guideline NG240: Meningitis (bacterial) and meningococcal disease (2024)
- •ESCMID Guideline on Diagnosis and Treatment of Acute Bacterial Meningitis (2016)
- •IDSA Practice Guidelines for the Management of Bacterial Meningitis (Tunkel et al., 2004)
- •Cochrane Review: Corticosteroids for Acute Bacterial Meningitis (Brouwer et al., 2015)
- •AAP Red Book: Report of the Committee on Infectious Diseases (current edition)
Key Clinical Takeaways
Pediatric bacterial meningitis remains one of the most time-critical diagnoses in children. The empiric antibiotic regimen, the decision about adjunctive dexamethasone, and post-exposure prophylaxis for close contacts all unfold within the first hour of presentation. The points below distil current evidence on pediatric bacterial meningitis into actions you can apply at the bedside.
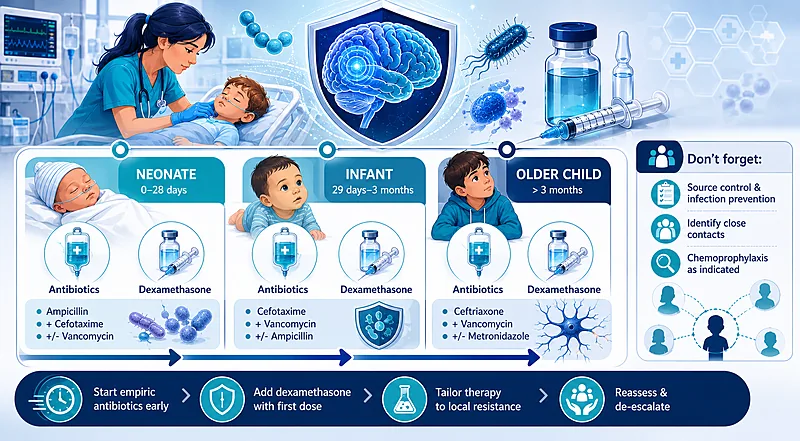
- 1Suspect pediatric bacterial meningitis in any febrile child with altered consciousness, neck stiffness, bulging fontanelle, petechial rash, or unexplained seizures.
- 2Give empiric IV antibiotics within 1 hour — never delay therapy for imaging or lumbar puncture if those are not immediately feasible.
- 3For neonates 0–28 days, start ampicillin plus cefotaxime to cover Group B Streptococcus, gram-negative enteric organisms, and Listeria.
- 4For infants 1–3 months, give ampicillin plus ceftriaxone — Listeria cover is still essential at this age.
- 5For children over 3 months, ceftriaxone plus vancomycin is the standard empiric regimen — vancomycin covers cephalosporin-resistant pneumococcus.
- 6Give dexamethasone 0.15 mg/kg IV with or just before the first antibiotic dose for confirmed or suspected Hib meningitis in children older than 6 weeks.
- 7Identify close contacts within 24 hours and give meningococcal prophylaxis (rifampin, ceftriaxone, or ciprofloxacin) promptly.
- 8Arrange formal audiology assessment 4–6 weeks after recovery — sensorineural hearing loss is the most common neurologic sequela.
Recognizing Pediatric Bacterial Meningitis Early
The classical triad of fever, neck stiffness, and altered consciousness is present in fewer than half of pediatric cases. In neonates and young infants, presentation is often nonspecific: poor feeding, irritability, lethargy, hypothermia, or a tense fontanelle. Maintaining a low threshold for suspecting pediatric bacterial meningitis — and acting on that suspicion — is the single most important determinant of outcome.
Evaluate any infant or child with fever and one or more of the following for pediatric bacterial meningitis: altered mental status, neck stiffness or photophobia (older children), bulging fontanelle, petechial or purpuric rash, unexplained seizures, or unexplained shock.
Strong Rec High Evidence NICE NG240 IDSA 2004In neonates and infants under 3 months with fever or hypothermia, include lumbar puncture as part of a full neonatal sepsis evaluation unless a clear contraindication exists — CSF should always be examined in this age group when sepsis is being investigated.
Strong Rec Moderate Evidence AAP Red Book NICE NG240Obtain blood cultures (ideally two sets) and CSF cultures before antibiotics whenever it can be done within 30 minutes of presentation. If that window cannot be met, give antibiotics immediately and draw cultures alongside.
Strong Rec High Evidence ESCMID 2016 IDSA 2004Order pre-LP head CT only when there are specific risk factors for cerebral herniation: focal neurologic deficits, GCS below 12, papilledema, a new-onset seizure within the past week, or significant immunocompromise. In their absence, perform the LP without imaging.
Strong Rec Moderate Evidence IDSA 2004Document the time of antibiotic administration. Time-to-antibiotics is a central quality indicator in pediatric bacterial meningitis — institutional audits should track the proportion of cases treated within one hour of suspicion.
Strong Rec Moderate Evidence NICE NG240Age-Stratified Empiric Antibiotics for Pediatric Bacterial Meningitis
Empiric antibiotic choice in pediatric bacterial meningitis is driven by age, because the likely pathogens shift dramatically across the first months of life. Neonates remain vulnerable to maternally acquired Group B Streptococcus, gram-negative enterics, and Listeria. Beyond 3 months, community-acquired pathogens — Streptococcus pneumoniae and Neisseria meningitidis — dominate, with Haemophilus influenzae type b rare in fully vaccinated populations but still a consideration in unvaccinated children.
Start empiric IV antibiotics within 1 hour of suspecting pediatric bacterial meningitis. Each hour of delay beyond this point is associated with worsening neurologic outcomes and increased mortality.
Strong Rec High Evidence NICE NG240For neonates aged 0–28 days, prescribe ampicillin 50 mg/kg IV every 6–8 hours (interval depends on postnatal age) plus cefotaxime 50 mg/kg IV every 6–8 hours. This pairing covers Group B Streptococcus, gram-negative enteric organisms (E. coli, Klebsiella), and Listeria monocytogenes.
Strong Rec High Evidence AAP Red Book IDSA 2004For infants aged 1–3 months, prescribe ampicillin 75 mg/kg IV every 6 hours plus ceftriaxone 100 mg/kg IV daily (or split 50 mg/kg every 12 hours), maximum 4 g/day. This regimen bridges late-neonatal Listeria coverage with the community organisms of older infancy.
Strong Rec High Evidence AAP Red BookFor children older than 3 months, prescribe ceftriaxone 100 mg/kg IV daily (max 4 g, split 12-hourly if dose exceeds 2 g) plus vancomycin 15–20 mg/kg IV every 6 hours (max 60 mg/kg/day, target trough 15–20 mcg/mL). Vancomycin is added empirically because cephalosporin-resistant pneumococcus is common enough to warrant cover until susceptibilities return.
Strong Rec High Evidence IDSA 2004 ESCMID 2016For a child with documented penicillin allergy and no cephalosporin cross-reactivity, ceftriaxone remains preferred. In the unusual case of true beta-lactam allergy, substitute vancomycin plus a fluoroquinolone (moxifloxacin) or chloramphenicol where available — consult pediatric infectious diseases urgently.
Conditional Rec Low Evidence IDSA 2004Add ampicillin to the empiric regimen for any pediatric patient with significant immunocompromise (oncology, transplant, congenital immunodeficiency) regardless of age — Listeria remains a concern.
Strong Rec Moderate Evidence IDSA 2004Do not co-administer ceftriaxone with calcium-containing IV fluids in neonates — fatal calcium-ceftriaxone precipitates have been reported in the lungs and kidneys. Use cefotaxime in neonates whenever calcium-containing solutions are needed.
Against Moderate Evidence FDA Safety CommunicationNarrow therapy to the most targeted agent as soon as the organism and susceptibilities return. For a fully cephalosporin-susceptible pneumococcus, vancomycin can usually be discontinued and ceftriaxone continued alone.
Strong Rec Moderate Evidence ESCMID 2016Antibiotic Choices in Pediatric Bacterial Meningitis: A Drug-by-Drug View
| Drug | IV Dose (max/day) | Used In | Key Coverage | Common Pitfalls |
|---|---|---|---|---|
| Ampicillin | 50–100 mg/kg q6h (max 12 g) | All ages under 3 months; immunocompromised | Listeria, Group B Strep, susceptible enterics | Underdosing in older infants — meningitic doses are higher than for sepsis |
| Cefotaxime | 50 mg/kg q6–8h (max 12 g) | Neonates (preferred over ceftriaxone) | Gram-negative enterics, pneumococcus, meningococcus | Frequent global shortages — have a local substitution plan |
| Ceftriaxone | 100 mg/kg/day (max 4 g) | Infants from 1 month onward; children | Pneumococcus, meningococcus, Hib, susceptible enterics | Avoid in neonates with calcium-containing fluids; check biliary sludging on prolonged courses |
| Vancomycin | 15–20 mg/kg q6h (max 60 mg/kg/day) | Children over 3 months (added to ceftriaxone) | Cephalosporin-resistant pneumococcus, MRSA | Therapeutic drug monitoring required; concurrent dexamethasone may reduce CSF penetration |
| Gentamicin | 4–5 mg/kg/day (extended interval) | Neonates (synergy with ampicillin) when cefotaxime unavailable | Gram-negative synergy with ampicillin | Poor CSF penetration as monotherapy; not adequate alone |
0–28 days: Ampicillin + Cefotaxime (substitute gentamicin if cefotaxime unavailable, with caution)
1–3 months: Ampicillin + Ceftriaxone
>3 months: Ceftriaxone + Vancomycin
Any age, immunocompromised: Add ampicillin to the age-appropriate regimen
Dexamethasone in Pediatric Bacterial Meningitis
The adjunctive role of dexamethasone in pediatric bacterial meningitis is one of the more nuanced decisions in empiric management. Evidence is strongest for reducing severe hearing loss in Hib meningitis when given before or with the first antibiotic dose. For pneumococcal meningitis in children the benefit is less certain, and routine use in low-income settings has not been supported by trials.
Give dexamethasone 0.15 mg/kg IV (maximum 10 mg per dose) immediately before or together with the first antibiotic dose in children older than 6 weeks with suspected or confirmed Hib meningitis — particularly relevant in children with an incomplete Hib vaccine schedule. Continue every 6 hours for 4 days.
Strong Rec High Evidence Cochrane 2015 AAP Red BookConsider dexamethasone for suspected or confirmed pneumococcal meningitis in children — meta-analyses suggest a reduction in severe hearing loss when steroids are given before or with the first antibiotic dose, though the magnitude of benefit is smaller than for Hib disease.
Conditional Rec Moderate Evidence Cochrane 2015 ESCMID 2016Do not give dexamethasone to neonates with bacterial meningitis — there is no evidence of benefit in this age group, and developmental concerns argue against routine corticosteroid exposure.
Against Low Evidence AAP Red BookDo not start dexamethasone more than 4 hours after the first antibiotic dose — once bacterial lysis is well underway, modulating the inflammatory response with steroids no longer alters outcome.
Against Moderate Evidence Cochrane 2015Discontinue dexamethasone early if cultures and CSF PCR exclude bacterial meningitis or another non-bacterial diagnosis becomes apparent. There is no role for completing the full 4-day course in viral meningoencephalitis.
Conditional Rec Low Evidence ESCMID 2016Dexamethasone Decision Snapshot
| Clinical Scenario | Recommend? | Dose & Timing | Evidence Strength | Practical Notes |
|---|---|---|---|---|
| Suspected/confirmed Hib meningitis, child > 6 weeks | Yes | 0.15 mg/kg IV q6h × 4 days, before/with first dose | High (RCT-supported) | Reduces severe hearing loss; rare in fully vaccinated populations |
| Suspected/confirmed pneumococcal meningitis | Consider | Same dose, same timing | Moderate; benefit setting-dependent | Watch for reduced vancomycin CSF penetration |
| Suspected meningococcal meningitis | No clear benefit | — | Low | If already started empirically and meningococcus confirmed, complete or stop based on clinical course |
| Neonate with bacterial meningitis | No | — | Low (no benefit shown) | Routine use not recommended in this age group |
| First antibiotic dose given > 4 hours ago | No | — | Moderate (window has closed) | Document the rationale for not starting |
Contact Prophylaxis After Pediatric Bacterial Meningitis
Once pediatric bacterial meningitis is suspected on epidemiologic grounds (meningococcal disease, Hib disease in an unvaccinated household), public health management runs in parallel with treatment. The two organisms that mandate chemoprophylaxis are Neisseria meningitidis and Haemophilus influenzae type b. Streptococcus pneumoniae does not require prophylaxis — secondary attack rates are not elevated.
Identify close contacts of a meningococcal index case within 24 hours. Close contacts include household members, anyone who shared sleeping quarters in the 7 days before symptom onset, regular childcare or preschool contacts, and anyone with direct mucosal exposure to oral secretions (kissing, mouth-to-mouth resuscitation, unprotected intubation).
Strong Rec Moderate Evidence CDC 2024Prescribe rifampin 10 mg/kg PO every 12 hours (maximum 600 mg per dose) for 2 days as first-line meningococcal chemoprophylaxis in children. For neonates under 1 month, use 5 mg/kg every 12 hours.
Strong Rec High Evidence CDC 2024 AAP Red BookUse ceftriaxone 125 mg IM as a single dose (children younger than 15 years) or 250 mg IM (15 years and older) as an alternative — especially useful for pregnant contacts and for ensuring a single observed dose. Ciprofloxacin 20 mg/kg PO as a single dose (max 500 mg) is another option for children who can swallow tablets. Use the exposure as a chance to review and update meningococcal vaccination.
Moderate Rec Moderate Evidence CDC 2024For invasive Hib disease, prescribe rifampin 20 mg/kg/day PO (max 600 mg/day) for 4 days to all unvaccinated or incompletely vaccinated household contacts younger than 4 years. Treat all household members — including fully vaccinated adults — when the household contains an immunocompromised child regardless of that child’s vaccination status.
Strong Rec Moderate Evidence AAP Red BookDo not give chemoprophylaxis to contacts of children with pneumococcal meningitis. Secondary attack rates are not increased above background, and prophylaxis has not been shown to prevent transmission.
Against High Evidence CDCContact Prophylaxis at a Glance
| Index Organism | Who Needs Prophylaxis | First-Line (Pediatric Dose) | Alternatives | Timing |
|---|---|---|---|---|
| N. meningitidis | Household, sleeping-quarter, childcare, and oral-secretion contacts in prior 7 days | Rifampin 10 mg/kg q12h × 2 days (max 600 mg/dose); 5 mg/kg if <1 month | Ceftriaxone IM × 1; ciprofloxacin PO × 1 (older children/adults) | Within 24 hours of index identification |
| H. influenzae type b | Unvaccinated household contacts <4 yrs; all household members if immunocompromised child in home | Rifampin 20 mg/kg/day × 4 days (max 600 mg/day) | No equivalent single-dose alternative is endorsed | Within 7 days of index identification |
| S. pneumoniae | None | Not indicated | — | — |
Clinical Decision Pathway
A question-based approach to the first hour of suspected pediatric bacterial meningitis. Work through the questions in order; do not return to question 1 once treatment has started.
Monitoring and Follow-Up
Survival from bacterial meningitis in children is no longer the only outcome that matters. Hearing loss, neurodevelopmental impairment, and seizure disorders affect a substantial minority of survivors, and structured follow-up is essential.
Repeat lumbar puncture 24–48 hours after starting therapy only when the clinical course is atypical, the patient is not improving, or the isolate is resistant or unusual. Routine repeat LP is not required in straightforward courses.
Conditional Rec Moderate Evidence IDSA 2004Arrange formal audiology follow-up within 4–6 weeks of discharge. Sensorineural hearing loss occurs in 5–30% of bacterial meningitis survivors, with the highest risk after pneumococcal disease. Early identification supports timely amplification or cochlear implantation referral.
Strong Rec High Evidence NICE NG240Plan neurodevelopmental review at 6 and 12 months post-discharge for any child who survived pediatric bacterial meningitis. Screen specifically for motor delay, language regression, behavioral change, and new-onset epilepsy.
Strong Rec Moderate Evidence NICE NG240Review the child’s immunization record and bring all vaccines up to date before discharge, with particular attention to PCV, Hib, and meningococcal conjugate vaccines. Use the admission as a catch-up opportunity for household contacts as well.
Strong Rec Low Evidence AAP Red Book| Parameter | When to Check | What to Look For | Common Pitfalls |
|---|---|---|---|
| Clinical review | Every 4–6 h in the first 24 h | Defervescence, improving GCS, hemodynamic stability | Persistent fever for 48 h is common — don’t change antibiotics on fever alone |
| Repeat LP | 24–48 h only if not improving or unusual organism | Sterilization of CSF; declining WBC | Not routine; avoid in straightforward cases |
| Neuroimaging | If no improvement at 48–72 h, focal signs, or new seizures | Subdural empyema, infarct, hydrocephalus, abscess | Don’t routinely image at admission unless red flags |
| Audiology | 4–6 weeks post-discharge | Sensorineural hearing loss; early labyrinthitis ossificans | Frequently missed at outpatient handover — set a reminder at discharge |
| Neurodevelopment | 6 and 12 months | Motor, language, behavior, new epilepsy | Symptoms can emerge late — review even if early recovery looked complete |
Evidence in Context
What the trials and major guidelines actually show, where they agree, and where local practice has to fill the gaps.
Where IDSA, ESCMID, and NICE Agree
The three frameworks converge on the central principles: rapid empiric therapy, age-stratified regimens with broad coverage for the most likely pathogens, ceftriaxone-plus-vancomycin for older children with suspected pneumococcal disease, and structured audiology follow-up. All endorse dexamethasone for confirmed or suspected Hib meningitis in vaccinated and unvaccinated populations.
Where the Guidelines Differ
The most notable difference concerns dexamethasone for pneumococcal disease in children. ESCMID 2016 supports its use in adults and conditionally in children when pneumococcus is likely. The AAP is more cautious in children, citing mixed pediatric trial data. The 2024 NICE guideline (NG240) takes an intermediate position, recommending dexamethasone primarily on suspicion of bacterial meningitis in children older than 3 months, regardless of expected pathogen, provided it is given before or with the first antibiotic dose.
The Dexamethasone Evidence in Children
The Cochrane review by Brouwer et al. (2015) pooled data from over 4,000 patients across multiple RCTs. In children, adjunctive corticosteroids reduced severe hearing loss (relative risk approximately 0.5) primarily in high-income settings. Trials from sub-Saharan Africa, where presentation is later and HIV co-infection prevalent, showed no mortality or hearing benefit. The take-home is that early administration is critical, and benefit is most clearly demonstrated in well-resourced settings with prompt presentation.
Why Vancomycin Is Empirical for Older Children
Penicillin and cephalosporin resistance among Streptococcus pneumoniae varies geographically, with rates of cephalosporin non-susceptibility reaching 10–25% in some regions. Because CSF concentrations of ceftriaxone are barely above the MIC against intermediate-susceptibility strains, empirical addition of vancomycin until susceptibilities return is justified. Where local resistance rates are very low, some institutions omit vancomycin — review the local antibiogram annually.
Has the Vaccine Era Changed the Game?
Hib vaccination has reduced invasive Hib disease in many settings by more than 95%, and the introduction of conjugate pneumococcal vaccines (PCV10 and PCV13) has substantially reduced pediatric pneumococcal meningitis. Meningococcal conjugate vaccines have similarly reduced serogroup C and ACWY disease. The corollary is that any child presenting today with pediatric bacterial meningitis is more likely to come from an unvaccinated or under-vaccinated background — always check the immunization record.
Why Cefotaxime Over Ceftriaxone in Neonates
Ceftriaxone displaces bilirubin from albumin and can precipitate when given alongside calcium-containing IV fluids — both substantial concerns in neonates. Cefotaxime has similar antibacterial coverage without these specific risks, which is why neonatal regimens almost universally favor it. Where cefotaxime is unavailable due to supply issues, an aminoglycoside (gentamicin) plus ampicillin is an accepted substitute, though CSF penetration is weaker.
References
- 1. Tunkel AR, Hartman BJ, Kaplan SL, et al. Practice guidelines for the management of bacterial meningitis. Clin Infect Dis. 2004;39(9):1267–1284. doi:10.1086/425368
- 2. van de Beek D, Cabellos C, Dzupova O, et al. ESCMID guideline: diagnosis and treatment of acute bacterial meningitis. Clin Microbiol Infect. 2016;22(Suppl 3):S37–S62. doi:10.1016/j.cmi.2016.01.007
- 3. Brouwer MC, McIntyre P, Prasad K, van de Beek D. Corticosteroids for acute bacterial meningitis. Cochrane Database Syst Rev. 2015;(9):CD004405. doi:10.1002/14651858.CD004405.pub5
- 4. Kim KS. Acute bacterial meningitis in infants and children. Lancet Infect Dis. 2010;10(1):32–42. doi:10.1016/S1473-3099(09)70306-8
- 5. National Institute for Health and Care Excellence (NICE). Meningitis (bacterial) and meningococcal disease: recognition, diagnosis and management. NICE guideline [NG240]. 2024. nice.org.uk/guidance/ng240
- 6. McGill F, Heyderman RS, Michael BD, et al. The UK joint specialist societies guideline on the diagnosis and management of acute meningitis and meningococcal sepsis in immunocompetent adults. J Infect. 2016;72(4):405–438. doi:10.1016/j.jinf.2016.01.007
- 7. American Academy of Pediatrics. Red Book: Report of the Committee on Infectious Diseases. Itasca, IL: AAP. publications.aap.org/redbook
How to Read the Evidence Tags
Every recommendation in this Practice Update carries two tags — one for the strength of the recommendation, one for the underlying evidence quality — followed by the source(s). These are Medaptly’s simplified interpretations of the underlying guideline grading systems.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | The weight of evidence favors this action. |
| Conditional Rec | Benefit is less certain — individualize. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large, well-conducted observational studies. |
| Low Evidence | Expert consensus, small studies, or extrapolated data. |