
Carotid Artery Stenosis: 7 Critical Management Rules
Clinical Practice Update — Symptomatic and Asymptomatic Management, CEA vs CAS vs TCAR
This is an original clinical education article informed by current guidelines and evidence. See References below for source documents.
- Clinical Focus
- Evidence-based diagnosis, medical therapy, and revascularization of carotid artery stenosis in adults
- Target Audience
- Vascular surgeons, stroke physicians, neurologists, interventional radiologists, primary care physicians
- Setting
- Stroke clinic, vascular surgery clinic, interventional suite, operating theatre, primary care
- Source Evidence
- •Society for Vascular Surgery (SVS) Guidelines on Management of Extracranial Cerebrovascular Disease (2022)
- •ESVS Clinical Practice Guidelines on Carotid and Vertebral Artery Disease (2023)
- •AHA/ASA Guideline for Secondary Stroke Prevention (2021)
- •CREST Trial — Carotid Revascularization Endarterectomy vs Stenting Trial (NEJM, 2010)
- •ACST-2 Trial — Asymptomatic Carotid Surgery Trial 2 (Lancet, 2021)
Key Clinical Takeaways
Effective carotid artery stenosis management rests on three decisions: is the lesion symptomatic, is the patient a candidate for best medical therapy alone, and which revascularization technique fits the individual. The points below distil the evidence into bedside rules.
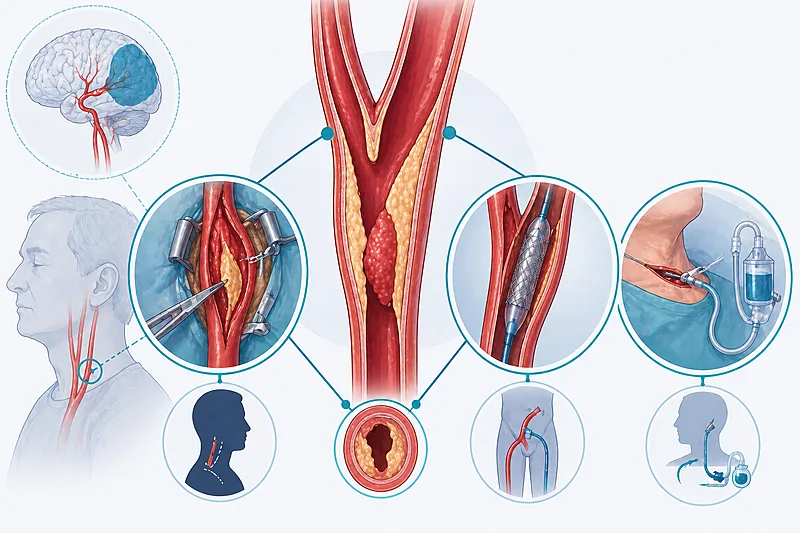
- 1Image the carotids urgently in any patient with a transient ischaemic attack or non-disabling ischaemic stroke → Recognition
- 2Operate on symptomatic 50–99% stenosis within 14 days of the index event — benefit falls sharply after that window → Symptomatic
- 3Offer best medical therapy to every patient regardless of procedure plans — statin, antiplatelet, BP control, and smoking cessation → Medical Therapy
- 4CEA is the default technique for most operative candidates — durable and supported by the largest body of evidence → Revascularization
- 5Consider transfemoral CAS in patients younger than 70 with hostile neck anatomy or prior radical neck surgery → Technique Choice
- 6Consider TCAR with flow reversal for high-risk anatomic or medical candidates — especially older patients → TCAR
- 7Keep the perioperative stroke/death rate under 6% for symptomatic disease and 3% for asymptomatic — above that, the procedure harms more than it helps → Quality Standard
- 8Book surveillance duplex at 6 weeks, 6 months, then annually after any carotid intervention → Surveillance
Recognising Carotid Artery Stenosis
Most carotid artery stenosis is either found on imaging for stroke workup or picked up incidentally during investigation of a bruit or unrelated neck imaging. Distinguishing symptomatic from asymptomatic disease is the first and most important classification step — it changes everything about treatment intensity and timing.
Perform urgent duplex ultrasound of the carotids in any patient with a suspected TIA, non-disabling ischaemic stroke, or amaurosis fugax ipsilateral to the suspected lesion.
Strong Rec High Evidence SVS 2022 ESVS 2023Confirm high-grade stenosis identified on duplex with a second modality — CT angiography or MR angiography — before proceeding to revascularization.
Strong Rec Moderate Evidence SVS 2022Do not perform routine carotid screening in asymptomatic adults from the general population — the prevalence is too low and the harms of over-intervention outweigh any benefit.
Against High Evidence USPSTF 2021Classify stenosis as symptomatic only when the patient has had an ipsilateral TIA, stroke, or retinal event within the past six months — an audible bruit alone is not a symptom.
Strong Rec High Evidence SVS 2022 ESVS 2023Symptomatic Disease: The Two-Week Window
The risk of a second stroke after TIA or minor stroke is front-loaded into the first two weeks. Revascularization prevents roughly one stroke for every six symptomatic 70–99% stenoses treated early, but the absolute benefit shrinks dramatically with delay.
Offer revascularization to patients with symptomatic 50–99% internal carotid artery stenosis, ideally within 14 days of the index TIA or non-disabling stroke.
Strong Rec High Evidence SVS 2022 ESVS 2023Counsel patients that the stroke risk in the first two weeks after a TIA is particularly high — approximately 10% in untreated high-grade lesions — and use this to drive urgency of workup.
Strong Rec High Evidence AHA/ASA 2021Do not offer revascularization in patients with symptomatic stenosis less than 50% — the trial evidence shows no benefit and demonstrable procedural harm.
Against High Evidence SVS 2022 NASCETEvaluate for revascularization only after a major disabling stroke has been carefully reviewed — severely disabled patients often do not benefit and may be harmed by the perioperative risk.
Conditional Rec Moderate Evidence SVS 2022Asymptomatic Disease: A Harder Call
Modern best medical therapy has halved the stroke rate seen in the landmark ACAS and ACST-1 trials. The absolute benefit of revascularization for asymptomatic stenosis is now narrower and depends on individual stroke risk factors, life expectancy, and the ability to deliver a very low complication rate.
Consider revascularization in selected patients with asymptomatic 70–99% stenosis who have a life expectancy beyond five years and can be operated on with a stroke/death rate under 3%.
Moderate Rec Moderate Evidence SVS 2022 ACST-2Start best medical therapy for every patient with asymptomatic carotid artery stenosis regardless of whether revascularization is planned — statin, antiplatelet, BP and diabetes control, smoking cessation.
Strong Rec High Evidence SVS 2022 AHA/ASA 2021Identify asymptomatic patients at higher stroke risk using imaging markers — silent ischaemic lesions on brain MRI, plaque echolucency, or microembolic signals — which tip the balance toward revascularization.
Moderate Rec Moderate Evidence ESVS 2023Do not routinely revascularize asymptomatic patients with a life expectancy under three to five years — the benefit of stroke prevention accrues late and is offset by the early procedural risk.
Against Moderate Evidence SVS 2022Best Medical Therapy for Carotid Artery Stenosis
Best medical therapy is not the consolation prize when revascularization is declined — it is the foundation of care for every patient with carotid artery stenosis, operated or not. The four pillars are antiplatelet therapy, lipid lowering, blood pressure control, and lifestyle change.
Prescribe high-intensity statin therapy (atorvastatin 40–80 mg or rosuvastatin 20–40 mg) in every patient with carotid artery stenosis, targeting an LDL-C below 1.8 mmol/L (70 mg/dL).
Strong Rec High Evidence AHA/ASA 2021 SVS 2022Start aspirin 75–100 mg daily as the default antiplatelet for long-term therapy; clopidogrel 75 mg daily is an equivalent alternative.
Strong Rec High Evidence AHA/ASA 2021Consider short-term dual antiplatelet therapy (aspirin plus clopidogrel) for the first 21–90 days after TIA or minor stroke, then step down to monotherapy.
Moderate Rec High Evidence AHA/ASA 2021Optimise blood pressure to below 130/80 mmHg in every patient with carotid artery stenosis; start with an ACE inhibitor or ARB plus a thiazide-like diuretic or calcium-channel blocker.
Strong Rec High Evidence AHA/ASA 2021Counsel every current smoker on cessation at each visit and offer pharmacotherapy — continued tobacco use is a potent driver of plaque progression and recurrent stroke.
Strong Rec High Evidence AHA/ASA 2021Medical Therapy Bundle by Clinical Scenario
| Scenario | Antiplatelet | Lipid Target | Practical Tips |
|---|---|---|---|
| Asymptomatic stenosis | Aspirin 75–100 mg monotherapy | LDL-C < 1.8 mmol/L | BP <130/80; structured lifestyle clinic |
| Recent TIA or minor stroke | DAPT (aspirin + clopidogrel) 21–90 days | LDL-C < 1.4 mmol/L if very high risk | Same-day statin load; stroke clinic within 24 h |
| Post-CEA | Aspirin lifelong | LDL-C < 1.8 mmol/L | Duplex at 6 weeks, 6 months, then yearly |
| Post-CAS / TCAR | DAPT 30 days then aspirin lifelong | LDL-C < 1.8 mmol/L | Check clopidogrel loading done pre-procedure |
Revascularization for Carotid Artery Stenosis: CEA, CAS, or TCAR?
Carotid endarterectomy (CEA), transfemoral carotid artery stenting (CAS), and transcarotid artery revascularization (TCAR) each have a defined patient profile. CREST and the pooled trial data consistently show CEA as the durable default; CAS is preferred in younger patients with hostile necks; TCAR adds flow reversal to reduce embolic risk and has become the preferred endovascular option in older patients.
Offer CEA as the first-line revascularization technique for most patients with symptomatic 50–99% or selected asymptomatic 70–99% stenosis.
Strong Rec High Evidence SVS 2022 CRESTConsider transfemoral CAS in patients under 70 with contraindications to open surgery — prior neck irradiation, radical neck dissection, contralateral laryngeal nerve palsy, or surgically inaccessible high bifurcation.
Moderate Rec High Evidence CREST SVS 2022Consider TCAR with dynamic flow reversal in anatomically or medically high-risk patients — particularly older patients where transfemoral CAS carries higher stroke risk.
Moderate Rec Moderate Evidence SVS 2022 ROADSTER-2Do not offer transfemoral CAS in patients over 75 with hostile aortic arches or heavy aortic calcification — the embolic stroke risk is disproportionately high.
Against Moderate Evidence CREST SVS 2022Ensure the centre audits and maintains a combined perioperative stroke/death rate below 6% for symptomatic and 3% for asymptomatic intervention — the surgical benefit is lost above this threshold.
Strong Rec High Evidence SVS 2022 ESVS 2023Choosing Between CEA, CAS, and TCAR
| Patient Profile | Preferred Technique | Rationale | Watch-Out |
|---|---|---|---|
| Standard-risk, surgically accessible, any age | CEA | Durable, lowest long-term restenosis | Hypoglossal or recurrent laryngeal nerve injury |
| Younger (<70), hostile neck (irradiated, redo) | Transfemoral CAS | Avoids reoperative neck; favourable arch anatomy | Requires DAPT; access-site complications |
| Older (≥70), anatomic high risk, arch disease | TCAR | Flow reversal reduces embolic stroke | Centre and operator experience needed |
| Crescendo TIA or stroke-in-evolution | Urgent CEA (expert choice) | Highest early stroke risk; operate same day | Haemorrhagic transformation risk |
| Very high medical risk, severe comorbidity | Best medical therapy alone | Any procedure risk exceeds stroke prevention benefit | Revisit if comorbidity improves |
Perioperative Management and Early Complications
The 30-day window is where most of the procedure-related stroke and death risk lives. Prepared teams, defined anaesthetic plans, and vigilant early recovery management meaningfully reduce harm.
Monitor and actively manage postoperative hypertension — aim for systolic BP between 120 and 150 mmHg in the first 24 hours; higher values risk cerebral hyperperfusion syndrome.
Strong Rec Moderate Evidence SVS 2022 ESVS 2023Perform a detailed neurological examination immediately post-emergence and then hourly for the first 4–6 hours — any new deficit triggers immediate duplex and consideration of return to theatre.
Strong Rec Moderate Evidence SVS 2022Document pre-procedure cranial nerve examination (specifically hypoglossal, vagus, and marginal mandibular branch of facial) so that any new postoperative deficit can be attributed correctly.
Moderate Rec Low Evidence SVS 2022Post-Procedure Surveillance
Restenosis rates run 5–10% over 5 years after CEA or stenting. Structured duplex surveillance catches re-narrowing before it becomes symptomatic and allows timely reintervention.
Arrange duplex ultrasound at 6 weeks, 6 months, and annually thereafter following CEA, CAS, or TCAR to detect recurrent stenosis early.
Strong Rec Moderate Evidence SVS 2022Consider reintervention for high-grade restenosis (≥70%) that is symptomatic, or asymptomatic with progressive luminal loss across consecutive scans.
Moderate Rec Moderate Evidence SVS 2022Reassess medical therapy at every surveillance visit — check statin dose, LDL-C, BP, tobacco status, and adherence to antiplatelet therapy.
Strong Rec Moderate Evidence AHA/ASA 2021Clinical Decision Pathway
A practical, question-based approach to the patient with a newly discovered carotid lesion. Work through the questions in order.
Monitoring and Follow-Up
| Parameter | When to Check | Action Threshold | Common Pitfalls |
|---|---|---|---|
| Duplex surveillance | 6 weeks, 6 months, then yearly | PSV >300 cm/s or velocity ratio >4 → reimage | Operator variability — cross-calibrate the lab |
| Blood pressure | Every clinic visit | Target <130/80 mmHg | Over-aggressive lowering in bilateral disease |
| LDL-C | 6–12 weeks after statin change, then yearly | >1.8 mmol/L → add ezetimibe or PCSK9i | Stopping statin for minor aches without re-challenge |
| Antiplatelet adherence | Every visit | Gaps → explore reasons and resume promptly | Accidental dual-therapy prolongation past 90 days |
| Smoking status | Every visit | Any continued use → brief advice + pharmacotherapy | Assuming the patient will raise it themselves |
Evidence in Context
What the landmark trials show, where the major guidelines agree, and where honest evidence gaps remain.
Where SVS, ESVS, and AHA/ASA Agree
All three frameworks agree on: urgent imaging after TIA or minor stroke, the 14-day window for symptomatic revascularization, CEA as the default technique in standard-risk patients, lifelong best medical therapy for everyone, and the audited procedural complication thresholds of 6% (symptomatic) and 3% (asymptomatic).
Where the Guidelines Differ
Asymptomatic thresholds: SVS is more permissive toward revascularization in asymptomatic 70–99% stenosis with favourable stroke risk factors; ESVS emphasises that best medical therapy alone is appropriate for many asymptomatic patients and calls for risk stratification before offering intervention.
TCAR endorsement: SVS has embraced TCAR more enthusiastically given US registry data; ESVS positions it as one endovascular option among several.
What NASCET, ACAS, and CREST Showed
NASCET established CEA’s benefit in symptomatic 50–99% stenosis and remains the anchor trial for current thresholds. ACAS and ACST-1 demonstrated a modest benefit for CEA in asymptomatic disease, although the modern medical-therapy bar is now higher.
CREST compared CEA with transfemoral CAS and found similar composite outcomes but a telling age interaction: younger patients fared better with CAS; older patients fared better with CEA. The result reshaped clinical practice.
TCAR and the ROADSTER Series
ROADSTER and ROADSTER-2 established TCAR as feasible and safe in high-surgical-risk patients. Registry data suggest lower stroke rates than transfemoral CAS in older patients, though randomised direct comparisons against CEA remain limited.
Evidence Gaps We Still Face
The CREST-2 trial (best medical therapy alone vs CEA/CAS for asymptomatic disease under modern medical therapy) will clarify the central question of whether asymptomatic revascularization still offers meaningful benefit. Robust randomised data comparing TCAR with CEA are also awaited.
References
- 1. AbuRahma AF, Avgerinos ED, Chang RW, et al. Society for Vascular Surgery clinical practice guidelines for management of extracranial cerebrovascular disease. J Vasc Surg. 2022;75(1S):4S–22S. doi:10.1016/j.jvs.2021.04.073
- 2. Naylor R, Rantner B, Ancetti S, et al. Editor’s Choice — European Society for Vascular Surgery (ESVS) 2023 Clinical Practice Guidelines on the Management of Atherosclerotic Carotid and Vertebral Artery Disease. Eur J Vasc Endovasc Surg. 2023;65(1):7–111. doi:10.1016/j.ejvs.2022.04.011
- 3. Kleindorfer DO, Towfighi A, Chaturvedi S, et al. 2021 Guideline for the Prevention of Stroke in Patients With Stroke and Transient Ischemic Attack. Stroke. 2021;52(7):e364–e467. doi:10.1161/STR.0000000000000375
- 4. Brott TG, Hobson RW, Howard G, et al. Stenting versus Endarterectomy for Treatment of Carotid-Artery Stenosis (CREST). N Engl J Med. 2010;363(1):11–23. doi:10.1056/NEJMoa0912321
- 5. Halliday A, Bulbulia R, Bonati LH, et al. Second asymptomatic carotid surgery trial (ACST-2): a randomised comparison of carotid artery stenting versus carotid endarterectomy. Lancet. 2021;398(10305):1065–1073. doi:10.1016/S0140-6736(21)01910-3
How to Read the Evidence Tags
Every recommendation in this article carries two tags — recommendation strength and evidence quality. These are Medaptly’s simplified interpretations, designed for bedside use.
Recommendation Strength
| Tag | What It Means |
|---|---|
| Strong Rec | High-quality evidence broadly supports this action. |
| Moderate Rec | Evidence favours this action for most patients. |
| Conditional Rec | Benefit is less certain — individualise based on patient factors. |
| Against | Evidence shows no benefit or potential harm. |
Evidence Quality
| Tag | What It Means |
|---|---|
| High Evidence | Multiple well-designed RCTs or high-quality meta-analyses. |
| Moderate Evidence | Single RCT or large observational studies. |
| Low Evidence | Expert consensus or small studies. |