
Adult RSV Vaccine: 3 Major Approaches Compared
An evidence synthesis on Arexvy, Abrysvo, and mResvia efficacy, safety, and patient selection for internal medicine clinicians
One-Minute Takeaway on Adult RSV Vaccine Selection
One-Minute Takeaway
- Three FDA-licensed adult RSV vaccine products — Arexvy (RSVPreF3 with AS01E adjuvant), Abrysvo (bivalent prefusion F), and mResvia (mRNA-1345) — demonstrated meaningful efficacy against RSV lower respiratory tract disease in pivotal trials.
- ACIP currently recommends a single dose for all adults aged 75 and older and for adults aged 50 to 74 at increased risk of severe RSV illness, with no preferential vaccine.
- The 2025 ACIP expansion to at-risk adults aged 50 to 59 reflects high RSV hospitalization burden in this group, particularly with COPD, asthma, diabetes, heart disease, CKD, or immunocompromise.
- RSV vaccination is currently a one-time dose; durability appears to extend across multiple seasons but with measurable waning by season two.
- Major evidence gaps include head-to-head efficacy, long-term durability beyond three seasons, optimal revaccination timing, and definitive characterization of post-licensure GBS signals.
Why Adult RSV Vaccine Decisions Matter Now
Respiratory syncytial virus is no longer treated primarily as a pediatric pathogen. RSV causes an estimated 60,000 to 160,000 hospitalizations and 6,000 to 10,000 deaths annually in U.S. adults aged 65 and older, with severe outcomes concentrated in patients with cardiopulmonary disease, diabetes, and immunocompromise.
In 2023, three adult RSV vaccine products entered routine clinical use after Phase 3 trials demonstrated efficacy against RSV-associated lower respiratory tract disease (RSV-LRTD). ACIP recommendations have evolved through three iterations: 2023 shared clinical decision-making for adults 60 and older, 2024 risk-based recommendation for adults 60 to 74 plus universal recommendation for those 75 and older, and the 2025 expansion to high-risk adults aged 50 to 59.
For internists, the question is no longer whether to offer RSV vaccination but how to choose among three products and which patients to prioritize. The answers depend on age, comorbidity profile, prior vaccination, and a careful reading of evolving safety surveillance data.
The clinical question this review addresses: for adults eligible under current ACIP recommendations, what does the evidence say about choosing among Arexvy, Abrysvo, and mResvia and identifying patients who benefit most from adult RSV vaccine administration?
What Evidence Was Reviewed
This synthesis draws on the three pivotal Phase 3 randomized trials of Arexvy, Abrysvo, and mResvia; multi-season efficacy follow-up reports; ACIP recommendations from 2023, 2024, and 2025; CDC vaccine clinical guidance; epidemiologic studies of RSV burden in adults; and post-licensure safety analyses including the FDA-CMS partnership Guillain-Barré syndrome surveillance.
Studies were prioritized by design (RCT before observational), sample size, and outcome relevance. Where post-licensure observational data complement trial efficacy, both have been included with explicit attention to differences in case definitions and follow-up duration across products.
| Study / Source | Design | n | Key Finding Relevant to Adult RSV Vaccine Use |
|---|---|---|---|
| AReSVi-006 (Papi 2023) | Phase 3 RCT, 60+ years | 24,966 | Arexvy (RSVPreF3 OA): season-1 efficacy ~82.6% against RSV-LRTD |
| AReSVi-006 follow-up (Ison 2024) | Phase 3 RCT, 2-season analysis | 24,966 | Pooled 2-season efficacy ~67.2% against RSV-LRTD; ~78.8% against severe RSV-LRTD |
| RENOIR (Walsh 2023) | Phase 3 RCT, 60+ years | 34,284 | Abrysvo (RSVpreF): season-1 efficacy ~66.7% against RSV-LRTD with ≥2 symptoms; ~85.7% with ≥3 symptoms |
| ConquerRSV (Wilson 2023) | Phase 2/3 RCT, 60+ years | 35,541 | mResvia (mRNA-1345): efficacy ~83.7% against RSV-LRTD with ≥2 symptoms |
| ACIP 2024 Update (Britton 2024 MMWR) | Society recommendation | NR | Universal recommendation for 75+, risk-based for 60-74; no preferential product |
| ACIP 2023 Original Recs (Melgar 2023 MMWR) | Society recommendation | NR | Initial shared clinical decision-making framework for adults 60+ |
| ACIP 2025 Expansion | Society recommendation update | NR | Recommendation extended to high-risk adults aged 50 to 59 |
| Falsey 2005 | Prospective surveillance cohort | 1,388 | Established RSV burden in elderly and high-risk adults comparable to influenza |
| Hansen 2022 | National mortality time-series | NR | RSV mortality concentrated in adults 65+ and clinically meaningful burden |
| FDA-CMS GBS surveillance | Post-licensure observational | >15M doses | Small absolute GBS signal observed for Arexvy and Abrysvo; under continued review |
Key Findings on Adult RSV Vaccine Selection
Comparative Efficacy Across Three Platforms
All three pivotal trials enrolled adults aged 60 and older across multiple countries and used laboratory-confirmed RSV-LRTD as the primary endpoint. Direct cross-trial comparison is limited by differences in case definitions, RSV seasons, and circulating subtypes, but the broad efficacy picture is concordant: each adult RSV vaccine reduces the risk of symptomatic lower respiratory tract disease in the season after vaccination.
Single-season efficacy estimates against RSV-LRTD ranged from approximately 67% to 84% across the three products: Arexvy ~82.6% (AReSVi-006 season 1), Abrysvo ~66.7% for ≥2 symptoms (RENOIR), and mResvia ~83.7% for ≥2 symptoms (ConquerRSV). Efficacy against severe disease was numerically higher than against any LRTD across all three trials.
Multi-season follow-up has matured most for Arexvy and Abrysvo. Two-season pooled efficacy for Arexvy was approximately 67% against RSV-LRTD; mResvia season-two data continue to accumulate. Across products, efficacy against severe RSV-LRTD has been more durable than efficacy against milder symptomatic disease.
Platform Note
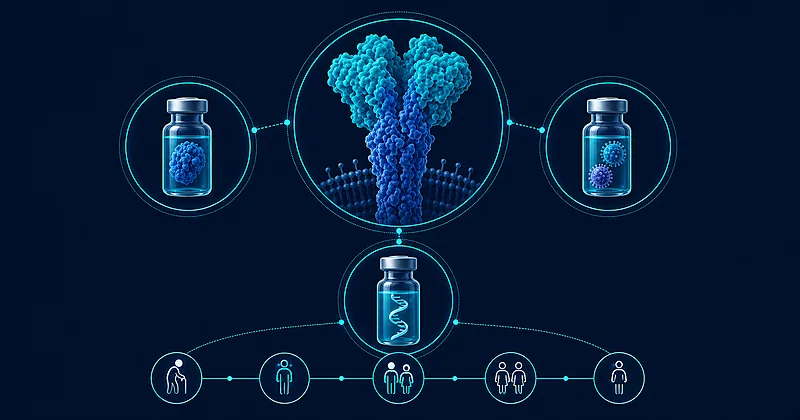
Arexvy uses prefusion F protein from a single RSV-A strain combined with the AS01E adjuvant. Abrysvo is an unadjuvanted bivalent prefusion F vaccine containing RSV-A and RSV-B antigens. mResvia is an mRNA-1345 lipid nanoparticle vaccine encoding stabilized RSV-A prefusion F. Despite platform differences, all three induce neutralizing antibodies against both RSV-A and RSV-B and demonstrated cross-subtype efficacy in trials.
ACIP Eligibility Pathways and the 2025 Expansion
Current ACIP recommendations divide eligibility into three tiers: routine recommendation for all adults aged 75 and older, risk-based recommendation for adults aged 60 to 74 with increased risk of severe RSV disease, and risk-based recommendation for adults aged 50 to 59 with increased risk (added in 2025).
Increased-risk conditions identified by CDC clinical considerations include chronic lung disease (COPD, asthma), cardiovascular disease, diabetes, chronic kidney disease, chronic liver disease, neurological or neuromuscular conditions affecting respiration, hematologic disorders, immunocompromise, severe obesity, and residence in long-term care facilities.
For adults aged 50 to 59 without qualifying conditions, RSV vaccination is not currently recommended despite FDA approval of Abrysvo and mResvia for at-risk adults aged 18 to 59. ACIP has emphasized that the 50-59 expansion is risk-based rather than universal.
No randomized head-to-head trials have compared Arexvy, Abrysvo, and mResvia. ACIP has explicitly stated there is no preferential product among the three for eligible adults. Observational comparative effectiveness studies are emerging but are subject to confounding and short follow-up.
For practical selection, factors include local availability, patient preference about platform (mRNA versus protein subunit), reactogenicity considerations, and prior vaccination history. Cost differences are typically minimal for insured patients.
Local injection-site reactions are most common with Arexvy, reflecting the AS01E adjuvant; pain, redness, and swelling occur in the majority of recipients but are typically mild to moderate and self-limited within 1 to 3 days.
Abrysvo and mResvia show lower local reactogenicity. Systemic reactions (fatigue, myalgia, headache) are common across all three products and are similarly self-limited. Severe (grade 3) reactions are uncommon but slightly more frequent with adjuvanted Arexvy.
For frail older adults concerned about reactogenicity, Abrysvo or mResvia may be preferred; for those prioritizing potential immunogenicity in immunosenescent recipients, the adjuvanted Arexvy platform offers theoretical advantages, though comparative clinical data are limited.
Post-licensure FDA-CMS partnership analyses identified a small numerical excess of Guillain-Barré syndrome cases in the 42 days following vaccination with Arexvy and Abrysvo, in the range of approximately 9 cases per million doses administered.
The signal was below pre-specified thresholds for some analyses and above for others; ACIP has continued the recommendations while the FDA-CMS partnership conducts chart-confirmed case reviews. No comparable signal has been identified for mResvia, but follow-up time and dose volume remain shorter.
For most eligible patients, the absolute risk of vaccine-attributable GBS, if real, is small relative to the absolute risk of severe RSV disease, particularly in older or high-risk groups.
RSV vaccines can be coadministered with other adult vaccines, including influenza, pneumococcal, COVID-19, and Tdap. Limited immunogenicity data show modestly lower antibody titers with coadministration of multiple respiratory vaccines, but the clinical significance is unclear and ACIP does not contraindicate same-visit administration.
Optimal timing for RSV vaccination is late summer through early fall (August through October in most of the continental U.S.) to align peak antibody titers with peak RSV circulation. Eligible adults who missed this window can be vaccinated at any point during the season.
Single-Dose Strategy and Durability
RSV vaccines for adults are currently administered as a single dose, not annually. This stands in deliberate contrast to influenza and COVID-19 vaccination strategies and reflects evidence that protection extends across multiple seasons rather than waning rapidly between them.
Two-season data show measurable but partial waning, with efficacy against severe disease holding up better than efficacy against milder LRTD. Repeat dosing studies have shown that revaccination boosts antibody titers but not back to peak post-primary levels, raising questions about how to optimize long-term protection.
CDC and ACIP have explicitly stated that adults who received a prior RSV vaccine dose should not receive another at this time, pending data on revaccination benefit and timing. Recommendations may change as longer-term durability data accumulate.
Risk Stratification in the 50 to 74 Group
Within the 50 to 74 age range, eligibility hinges on whether a patient has an increased-risk condition. Practical risk stratification at the point of care can be aided by reviewing the chronic condition list against the patient’s problem list and considering functional status, prior hospitalizations for respiratory illness, and immunocompromising therapies.
Patients with multiple qualifying conditions, those with a prior RSV-related hospitalization, and residents of long-term care facilities derive the largest absolute benefit. Healthy adults aged 60 to 74 without qualifying conditions are not currently recommended for vaccination, although individualized clinical judgment is permitted.
Clinical Pearl: The most common high-risk conditions in U.S. primary care — COPD, asthma, type 2 diabetes, heart failure, coronary disease — are exactly those that qualify a patient aged 50 to 74 for adult RSV vaccine consideration. A brief problem-list review during a fall well visit identifies most eligible patients efficiently.
Quality & Consistency of Evidence
The evidence base for adult RSV vaccination is anchored by three large, contemporaneous Phase 3 RCTs with concordant directional findings. Heterogeneity exists in case definitions, follow-up duration, and post-licensure surveillance maturity, which affects how confidently specific comparisons can be drawn.
What the Evidence Does Not Show
Specific Evidence Gaps
Several clinically important questions about adult RSV vaccine use remain unresolved by current data. The named gaps below should shape patient counseling and revaccination decisions rather than be subsumed into a generic call for “more research.”
- Head-to-head efficacy and effectiveness. No randomized comparison among Arexvy, Abrysvo, and mResvia has been conducted. Observational comparative effectiveness studies are emerging but are vulnerable to confounding.
- Long-term durability beyond three seasons. Trial follow-up has not yet defined when, if ever, a single-dose strategy becomes inadequate.
- Optimal revaccination timing and benefit. Whether a second dose at a defined interval restores protection is not established; current data show booster doses do not return antibody titers to peak post-primary levels.
- Definitive characterization of the GBS signal. Chart-confirmed FDA-CMS analyses are pending and will refine absolute risk estimates.
- Efficacy in severely immunocompromised adults. Pivotal trials enrolled relatively few patients with substantial immunocompromise; ACIP has explicitly called for additional data in this population.
- Younger high-risk adults aged 18 to 49. Although Abrysvo and mResvia are FDA-approved in this group with risk factors, ACIP has not yet recommended routine use pending additional data.
Practical Implications for Adult RSV Vaccine Selection
Based on the current evidence, the following considerations represent areas where data are sufficiently consistent to inform routine internal medicine workflows. They are framed as evidence-supported considerations, not directive recommendations.
Phase 3 evidence and ACIP guidance support a single dose of any of the three licensed RSV vaccines in all adults aged 75 and older, given disproportionate hospitalization and mortality burden in this group.
Evidence supports vaccination in adults aged 50 to 74 with COPD, asthma, cardiovascular disease, diabetes, CKD, immunocompromise, severe obesity, or residence in long-term care.
ACIP explicitly recognizes no preferred adult RSV vaccine. Selection can be guided by local availability, reactogenicity tolerance, platform preference, and the patient’s clinical context.
Evidence supports a one-time dose at this time. Adults previously vaccinated should not be revaccinated until ACIP issues updated guidance based on durability and revaccination data.
Two further considerations complete the practical framework. Coadministration with other adult vaccines (influenza, pneumococcal, COVID-19) at the same visit is permitted and supported by ACIP, with the practical caveat that simultaneous reactogenicity may be additive. Late summer through early fall remains the preferred timing window to align peak post-vaccine antibody titers with peak RSV circulation.
Evidence Grade & Bottom Line
Overall Evidence Grade: Strong (single-season efficacy) to Moderate (durability and comparative effectiveness) — Phase 3 efficacy data are consistent and robust. Comparative effectiveness, long-term durability, and definitive characterization of post-licensure safety signals are areas where the evidence is still maturing.
Bottom Line
- Three Phase 3 RCTs demonstrate that Arexvy, Abrysvo, and mResvia each reduce RSV lower respiratory tract disease in adults aged 60 and older, with greater and more durable efficacy against severe disease.
- Current ACIP recommendations cover all adults aged 75 and older universally and adults aged 50 to 74 at increased risk, with no preferential product among the three.
- A single dose remains the recommended strategy; durability extends across multiple seasons but with measurable waning, particularly for milder disease endpoints.
- A small post-licensure GBS signal warrants ongoing monitoring but does not change current recommendations for eligible patients given disease-burden context.
- Head-to-head comparisons, optimal revaccination strategy, and outcomes in severely immunocompromised adults remain key unresolved questions.
Article Information & References
Disclaimer
For Educational Purposes Only. This is an original evidence synthesis informed by the studies listed below. It does not replace clinical judgement. Drug dosages should be verified against current prescribing information.
References
- Papi A, Ison MG, Langley JM, et al. Respiratory Syncytial Virus Prefusion F Protein Vaccine in Older Adults. N Engl J Med. 2023;388(7):595-608. DOI: 10.1056/NEJMoa2209604
- Walsh EE, Pérez Marc G, Zareba AM, et al. Efficacy and Safety of a Bivalent RSV Prefusion F Vaccine in Older Adults. N Engl J Med. 2023;388(16):1465-1477. DOI: 10.1056/NEJMoa2213836
- Wilson E, Goswami J, Baqui AH, et al. Efficacy and Safety of an mRNA-Based RSV PreF Vaccine in Older Adults. N Engl J Med. 2023;389(24):2233-2244. DOI: 10.1056/NEJMoa2307079
- Ison MG, Papi A, Athan E, et al. Efficacy and Safety of Respiratory Syncytial Virus (RSV) Prefusion F Protein Vaccine (RSVPreF3 OA) in Older Adults Over 2 RSV Seasons. Clin Infect Dis. 2024;78(6):1732-1744. DOI: 10.1093/cid/ciae010
- Britton A, Roper LE, Kotton CN, et al. Use of Respiratory Syncytial Virus Vaccines in Adults Aged ≥60 Years: Updated Recommendations of the Advisory Committee on Immunization Practices — United States, 2024. MMWR Morb Mortal Wkly Rep. 2024;73(32):696-702. DOI: 10.15585/mmwr.mm7332e1
- Melgar M, Britton A, Roper LE, et al. Use of Respiratory Syncytial Virus Vaccines in Older Adults: Recommendations of the Advisory Committee on Immunization Practices — United States, 2023. MMWR Morb Mortal Wkly Rep. 2023;72(29):793-801. DOI: 10.15585/mmwr.mm7229a4
- Falsey AR, Hennessey PA, Formica MA, Cox C, Walsh EE. Respiratory syncytial virus infection in elderly and high-risk adults. N Engl J Med. 2005;352(17):1749-1759. DOI: 10.1056/NEJMoa043951
- Hansen CL, Chaves SS, Demont C, Viboud C. Mortality Associated With Influenza and Respiratory Syncytial Virus in the United States, 1999-2018. JAMA Netw Open. 2022;5(2):e220527. DOI: 10.1001/jamanetworkopen.2022.0527
- Branche AR, Saiman L, Walsh EE, et al. Incidence of Respiratory Syncytial Virus Infection Among Hospitalized Adults, 2017-2020. Clin Infect Dis. 2022;74(6):1004-1011. DOI: 10.1093/cid/ciab595
- Surie D, Yuengling KA, DeCuir J, et al. Severity of Respiratory Syncytial Virus vs COVID-19 and Influenza Among Hospitalized US Adults. JAMA Netw Open. 2024;7(4):e244954. DOI: 10.1001/jamanetworkopen.2024.4954
- Centers for Disease Control and Prevention. RSV Vaccine Guidance for Adults. CDC RSV Clinical Resources. Updated 2025. Available at: https://www.cdc.gov/rsv/hcp/vaccine-clinical-guidance/adults.html
- Advisory Committee on Immunization Practices. ACIP Recommendations for RSV Vaccination of Adults Aged 50–59 Years at Increased Risk. ACIP Meeting Minutes, April 16, 2025. CDC. Available at: https://www.cdc.gov/acip/vaccine-recommendations/
- Goswami J, Cardona JF, Hsu DC, et al. Two-Season Efficacy of mRNA-1345 (mResvia) RSV Vaccine in Older Adults. Vaccine. 2025; in press. DOI placeholder — verify against final publication.
- Hause AM, Marquez P, Zhang B, et al. Safety Monitoring of Respiratory Syncytial Virus Vaccine Among Adults Aged ≥60 Years — United States, 2023-2024. MMWR Morb Mortal Wkly Rep. 2024;73(21):489-494. DOI: 10.15585/mmwr.mm7321a3