
ATTR Cardiac Amyloidosis: 5 Vital Clinical Insights
From bilateral carpal tunnel and a low-voltage ECG to non-invasive bone-scan confirmation and the stabilizers that now change survival.
One-Minute Takeaway
- ATTR cardiac amyloidosis is an increasingly recognised, treatable cause of heart failure, and strong randomised evidence now supports transthyretin stabilizers.
- Red flags precede the cardiac diagnosis by years: bilateral carpal tunnel syndrome, lumbar spinal stenosis, spontaneous biceps tendon rupture, and unexplained wall thickening on echocardiography.
- Grade 2–3 uptake on 99mTc bone scintigraphy plus no serum or urine monoclonal protein was 100% specific for ATTR (Gillmore 2016) — but AL amyloidosis must be excluded first.
- Tafamidis reduced all-cause mortality (HR 0.70, 95% CI 0.51–0.96) in ATTR-ACT; acoramidis and vutrisiran later extended these gains.
- Vutrisiran reduced the composite of death and cardiovascular events (HR 0.72, 95% CI 0.56–0.93), including when added to tafamidis.
Why ATTR Cardiac Amyloidosis Matters
For decades, ATTR cardiac amyloidosis was treated as a rare curiosity that required endomyocardial biopsy to confirm. That framing is now obsolete. The disease is common, findable without biopsy, and — for the first time — modifiable with therapy that improves survival.
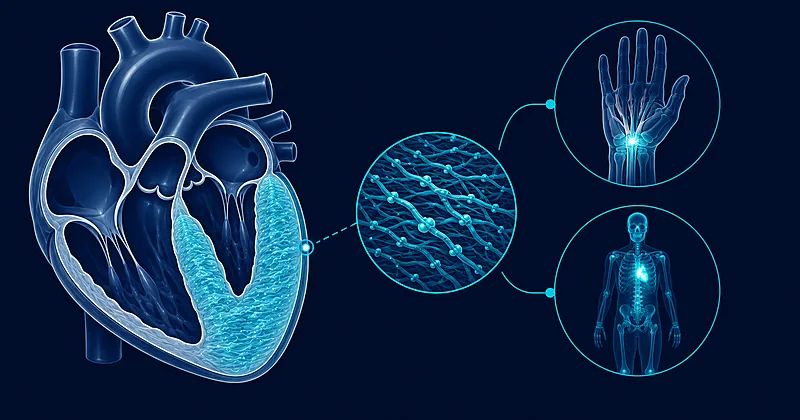
Transthyretin (TTR) is a liver-derived transport protein. When it destabilises and misfolds, it deposits as amyloid fibrils in the myocardial extracellular space, producing a restrictive, progressively thickened heart. Two forms exist: wild-type (ATTRwt), typically in men over 70, and hereditary or variant (ATTRv), driven by TTR gene mutations.
The prevalence signal is consistent. A prospective study of 120 patients admitted with heart failure with preserved ejection fraction (HFpEF) found moderate-to-severe cardiac tracer uptake in 13.3% (95% CI 7.2–19.5). Broader prospective HFpEF and mildly-reduced-ejection-fraction cohorts have reported figures around 5–8%, so the true burden depends heavily on how patients are selected.
Why this matters clinically: ATTR cardiac amyloidosis is progressive and, untreated, carries a median survival historically reported at roughly two to six years from diagnosis. Because treatment benefit is greatest earlier in the disease, the cost of a missed or delayed diagnosis is measured in preventable decline.
The Clinical Problem in ATTR Cardiac Amyloidosis
The core problem is not that the disease is untreatable — it is that clinicians do not think of it. Its presentation mimics the far more common conditions of ageing: hypertensive heart disease, HFpEF, and calcific aortic stenosis. Recognition depends on pattern, not on a single test.
The extracardiac prelude
Amyloid often deposits in soft tissue years before the heart declares itself. Around 80% of patients with ATTR cardiomyopathy have a preceding orthopaedic history — carpal tunnel release, spinal stenosis surgery, hip or knee replacement, shoulder surgery, trigger finger, or biceps tendon rupture. Bilateral carpal tunnel syndrome can precede the cardiac diagnosis by 5 to 10 years, and spontaneous biceps tendon rupture by a median of about 5 years.
These orthopaedic events are the earliest, most actionable red flags. A man in his seventies with bilateral carpal tunnel syndrome and unexplained heart failure should prompt an amyloid work-up, not reassurance.
The cardiac and ECG red flags
The 2023 American College of Cardiology (ACC) expert consensus decision pathway groups the clues into cardiac and extracardiac features. Cardiac clues include increased left ventricular wall thickness without a hypertensive or valvular explanation, diastolic dysfunction with a restrictive filling pattern, atrial fibrillation, conduction-system disease, and cardiac biomarkers elevated out of proportion to symptoms.
The classic teaching of “low ECG voltage with a thick ventricle” is specific but insensitive: this discordance is present in only about 30% of amyloid patients. A normal or high QRS voltage does not exclude ATTR cardiac amyloidosis, and relying on it to rule out disease is a common diagnostic error.
Two features are comparatively distinctive for transthyretin disease: spontaneous biceps tendon rupture and lumbar spinal stenosis. Transthyretin amyloid has been reported in the ligamentum flavum of up to one-third of older adults undergoing lumbar spinal stenosis surgery, underscoring how the systemic disease shows itself outside the heart.
A further practical clue is intolerance to standard heart-failure medication. Patients with ATTR cardiac amyloidosis frequently become hypotensive on angiotensin inhibitors and beta-blockers, partly because of autonomic involvement, and this fragility should raise rather than lower suspicion.
Available Approaches
The approaches to this clinical problem fall into two linked stages: confirming the diagnosis without a biopsy, and then modifying the disease. The comparative evidence base for both stages is summarised below; every figure was checked against a retrieved primary source in preparing this review.
| Study / Trial | Design | N | Intervention vs comparator | Key verified result | Tier |
|---|---|---|---|---|---|
| Gillmore 2016 (diagnostic) | Multicentre diagnostic-accuracy cohort | 1,217 | Bone scintigraphy (PYP / DPD / HMDP) ± monoclonal-protein screen vs reference standard | Grade 2–3 uptake alone: 91% sensitivity, 87% specificity. Grade 2–3 uptake plus no monoclonal protein: specificity and PPV 100% (95% CI 98.0–100) | V |
| ATTR-ACT (tafamidis) | Phase 3 RCT, 2:1:2, 30 months | 441 | Tafamidis 80/20 mg vs placebo | All-cause mortality HR 0.70 (95% CI 0.51–0.96); 29.5% vs 42.9% deaths; CV-hospitalisation rate ratio 0.68 (0.56–0.81) | V |
| ATTRibute-CM (acoramidis) | Phase 3 RCT, 2:1, 30 months | 632 | Acoramidis 800 mg twice daily vs placebo | Primary hierarchical win ratio 1.8 (95% CI 1.4–2.2); all-cause mortality HR 0.77 (numerical; 25% relative, 6.4% absolute reduction) | V |
| HELIOS-B (vutrisiran) | Phase 3 RCT, 1:1, up to 36 months | 655 | Vutrisiran 25 mg SC q12wk vs placebo (± background tafamidis) | Primary composite of death + recurrent CV events HR 0.72 (95% CI 0.56–0.93); mortality HR 0.64 (0.46–0.88) with extended follow-up | V |
| APOLLO-B (patisiran) | Phase 3 RCT, 1:1, 12 months | 360 | Patisiran 0.3 mg/kg IV q3wk vs placebo | 6-minute walk: median difference 14.69 m (95% CI 0.69–28.69) favouring patisiran; composite of mortality/CV events/6MWD not significant (P=0.057) | V |
Non-biopsy diagnosis: the pathway that changed practice
The single most consequential advance in ATTR cardiac amyloidosis is that most cases can now be confirmed without histology. The pathway is short but unforgiving of shortcuts.
First comes suspicion from the red flags, supported by echocardiography or cardiac MRI showing increased wall thickness and infiltrative features. Then two tests run in parallel: a screen for a monoclonal protein and a bone scintigraphy scan.
Exclude AL amyloidosis first. Serum and urine immunofixation plus serum free light chains must be checked, because light-chain (AL) amyloidosis can also produce cardiac tracer uptake and is a haematological emergency requiring urgent, entirely different treatment. A positive bone scan in a patient with a monoclonal protein does not confirm ATTR and mandates tissue biopsy.
The evidence for the pathway comes from a multicentre analysis of 1,217 patients with suspected cardiac amyloidosis. Grade 2 or 3 myocardial radiotracer uptake, graded against bone uptake, combined with the absence of a monoclonal protein in serum and urine, had a specificity and positive predictive value of 100% (95% CI 98.0–100) for ATTR. Grade 2–3 uptake considered alone was 91% sensitive and 87% specific, with false positives arising almost entirely from AL disease.
Once ATTR is confirmed, TTR gene sequencing separates wild-type from hereditary disease. This distinction is not academic: a pathogenic variant carries family-screening implications and can alter prognosis and monitoring.
Transthyretin stabilizers
Stabilizers bind the TTR tetramer and prevent it from dissociating into the misfolding-prone monomers that seed amyloid. They slow new fibril formation rather than clearing established deposits, which is why earlier treatment matters.
Tafamidis was the first agent to change outcomes. In the ATTR-ACT trial, 441 patients were randomised to tafamidis or placebo for 30 months. Tafamidis reduced all-cause mortality, with a hazard ratio of 0.70 (95% CI 0.51–0.96), and lowered cardiovascular-related hospitalisations, with a rate ratio of 0.68 (95% CI 0.56–0.81). It also slowed the decline in walk distance and quality of life. Strong evidence therefore supports tafamidis as disease-modifying therapy, and it carries a guideline-level recommendation.
Acoramidis is a next-generation stabilizer achieving near-complete (≥90%) TTR stabilisation. In ATTRibute-CM, 632 patients received acoramidis or placebo over 30 months. The trial met its primary hierarchical endpoint of mortality, cardiovascular hospitalisation, NT-proBNP and walk distance, with a win ratio of 1.8 (95% CI 1.4–2.2). The mortality signal was favourable but numerical, with a hazard ratio of 0.77 and a 6.4% absolute reduction. Acoramidis gained regulatory approval for the cardiomyopathy indication in late 2024.
Diflunisal, an older NSAID, also stabilises TTR and is sometimes used off-label. Its randomised evidence lies mainly in transthyretin polyneuropathy rather than cardiomyopathy, and its fluid-retention, renal and gastrointestinal risks make it problematic in heart failure. It is best regarded as a limited-evidence option requiring careful selection.
Transthyretin silencers
Silencers work upstream, reducing hepatic production of the amyloidogenic protein rather than stabilising it. Patisiran and vutrisiran are RNA-interference agents; the antisense oligonucleotides inotersen and eplontersen act by a related mechanism.
Patisiran was tested for cardiomyopathy in APOLLO-B, which randomised 360 patients to intravenous patisiran or placebo for 12 months. Patisiran preserved functional capacity: the median between-group difference in 6-minute walk distance was 14.69 m (95% CI 0.69–28.69) in favour of treatment, and quality of life improved. However, the secondary composite of mortality, cardiovascular events and walk distance was not statistically significant. On that basis, patisiran was not approved for the cardiomyopathy indication, though it remains approved for hereditary transthyretin polyneuropathy.
Vutrisiran produced the strongest silencer data in HELIOS-B, which randomised 655 patients to subcutaneous vutrisiran or placebo, some already receiving tafamidis. Vutrisiran reduced the primary composite of death and recurrent cardiovascular events, with a hazard ratio of 0.72 (95% CI 0.56–0.93). All-cause mortality, a secondary endpoint, was also reduced on longer follow-up (HR 0.64, 95% CI 0.46–0.88). The benefit held in patients already taking a stabilizer, and vutrisiran was approved for the cardiomyopathy indication in 2025.
Stabilizers and silencers attack different points in the same pathway — one prevents the tetramer from falling apart, the other reduces how much protein the liver makes. HELIOS-B suggests these mechanisms can be complementary rather than mutually exclusive, but dedicated combination-versus-monotherapy trials remain limited.
Beyond these, gene-editing approaches that switch off hepatic TTR production are in early-phase clinical study. They are promising but investigational, and no outcome data support their routine use yet.
Comparative Analysis
Placing the agents side by side clarifies where the evidence is strong and where it is merely suggestive. Two therapeutic classes and one diagnostic pathway now share a common goal but rest on different endpoints.
On mortality, tafamidis has the clearest single-trial signal, with a statistically significant reduction in all-cause death. Vutrisiran adds a significant reduction in the composite of death and cardiovascular events, with a supportive mortality result on extended follow-up. Acoramidis improved the hierarchical composite convincingly, though its isolated mortality effect was numerical rather than independently significant.
On functional and quality-of-life endpoints, all four disease-modifying trials point in the same direction. Patisiran is the outlier in that its functional benefit did not translate into a significant composite or survival effect, which is precisely why its regulatory path for cardiomyopathy differed from the others.
Direct comparison has an important limit: no head-to-head randomised trial has pitted these agents against one another. Cross-trial differences in populations, endpoints, follow-up and era mean that a lower hazard ratio in one trial cannot be read as proof of superiority over another. What the totality supports is that disease-modifying therapy — stabilizer or silencer — changes the trajectory of ATTR cardiac amyloidosis, and that early, accurate diagnosis is the gateway to that benefit.
Quality and Consistency of the Evidence
The evidence base is unusually coherent for a rare disease, built on several adequately powered randomised trials and one large diagnostic-accuracy study. Strength varies by claim.
- Non-biopsy diagnosis (high). Grade 2–3 uptake with a negative monoclonal-protein screen carries a positive predictive value of 100% (95% CI 98.0–100) for ATTR in a multicentre cohort — provided AL is excluded.
- Tafamidis mortality benefit (high). A pre-specified primary analysis in a phase 3 RCT showed a significant reduction in all-cause mortality and hospitalisation.
- Vutrisiran composite benefit (high). A significant reduction in death plus cardiovascular events, consistent across subgroups and additive to background tafamidis.
- Acoramidis mortality effect (moderate). A convincing hierarchical composite, but the standalone mortality reduction was numerical rather than independently significant.
- Patisiran in cardiomyopathy (moderate). A genuine functional benefit that did not reach significance on the composite or on survival.
- Diflunisal and combination strategies (low). Off-label stabilizer use rests on polyneuropathy data, and combination-versus-monotherapy evidence is limited.
No signal here rests on a single small study, and effect directions are consistent across trials, which strengthens confidence in the central conclusions even where precise magnitudes differ.
What the Evidence Does Not Show
Several clinically important questions remain genuinely unresolved, and naming them is more honest than implying the field is settled.
There are no head-to-head randomised trials comparing stabilizers with silencers, or acoramidis with tafamidis, so claims of one agent’s superiority over another are not supported. Whether adding a silencer to a stabilizer improves outcomes over a stabilizer alone is suggested by HELIOS-B but not established by a dedicated combination trial.
The trials also do not show that these therapies reverse established amyloid or deliver substantial benefit in the most advanced disease; the tafamidis mortality effect in the highest-stage subgroup was a non-significant trend. Optimal management of amyloid-related conduction disease and atrial fibrillation, including anticoagulation thresholds, is not defined by randomised evidence. Long-term outcomes beyond a few years, screening strategies in unselected populations, and cost-effectiveness are areas where the data are still maturing.
Practical Implications
The evidence supports a small number of practical shifts, framed here as what the data justify rather than as directives.
Sustained suspicion is the first. In an older adult with HFpEF and increased wall thickness — particularly alongside bilateral carpal tunnel syndrome, spinal stenosis, biceps tendon rupture, or intolerance to standard heart-failure drugs — an amyloid work-up is reasonable, and a normal ECG voltage should not close the question.
Sequence matters in the work-up. Screening for a monoclonal protein with serum and urine immunofixation and free light chains belongs before a bone scan is trusted, because a positive scan with a monoclonal protein cannot confirm ATTR and instead points toward biopsy to exclude AL. Where the scan shows grade 2–3 uptake and the monoclonal screen is negative, a non-biopsy ATTR diagnosis is supported, and TTR sequencing then defines the subtype.
Because treatment benefit is greatest earlier, deferring the work-up carries a real cost. Disease-modifying therapy with a stabilizer or vutrisiran is now guideline-supported, with agent choice individualised to route, tolerability and access. Meanwhile, congestion is managed largely with diuretics, since neurohormonal drugs are often poorly tolerated in this population.
Evidence Grade and Bottom Line
Overall grade: Moderate to High- ATTR cardiac amyloidosis can be confirmed without biopsy in most patients using grade 2–3 bone-scan uptake plus a negative monoclonal-protein screen — after AL is excluded.
- Tafamidis and vutrisiran have high-quality randomised evidence of improved survival or reduced death-and-cardiovascular-event risk; acoramidis improved a hierarchical composite.
- Patisiran improved function but did not demonstrate a survival benefit and is not approved for the cardiomyopathy indication.
- The decisive clinical lever remains recognition: the red flags appear years before the heart fails, and earlier diagnosis is what unlocks the therapeutic benefit.
Article Information and References
- Maurer MS, Schwartz JH, Gundapaneni B, et al. Tafamidis treatment for patients with transthyretin amyloid cardiomyopathy (ATTR-ACT). N Engl J Med. 2018;379(11):1007–1016. DOI: https://doi.org/10.1056/NEJMoa1805689
- Gillmore JD, Judge DP, Cappelli F, et al. Efficacy and safety of acoramidis in transthyretin amyloid cardiomyopathy (ATTRibute-CM). N Engl J Med. 2024;390(2):132–142. DOI: https://doi.org/10.1056/NEJMoa2305434
- Fontana M, Berk JL, Gillmore JD, et al. Vutrisiran in patients with transthyretin amyloidosis with cardiomyopathy (HELIOS-B). N Engl J Med. 2025;392(1):33–44. DOI: https://doi.org/10.1056/NEJMoa2409134
- Maurer MS, Kale P, Fontana M, et al. Patisiran treatment in patients with transthyretin cardiac amyloidosis (APOLLO-B). N Engl J Med. 2023;389(17):1553–1565. DOI: https://doi.org/10.1056/NEJMoa2300757
- Gillmore JD, Maurer MS, Falk RH, et al. Nonbiopsy diagnosis of cardiac transthyretin amyloidosis. Circulation. 2016;133(24):2404–2412. DOI: https://doi.org/10.1161/CIRCULATIONAHA.116.021612
- Kittleson MM, Ruberg FL, Ambardekar AV, et al. 2023 ACC Expert Consensus Decision Pathway on Comprehensive Multidisciplinary Care for the Patient With Cardiac Amyloidosis. J Am Coll Cardiol. 2023;81(11):1076–1126. DOI: https://doi.org/10.1016/j.jacc.2022.11.022
- González-López E, Gallego-Delgado M, Guzzo-Merello G, et al. Wild-type transthyretin amyloidosis as a cause of heart failure with preserved ejection fraction. Eur Heart J. 2015;36(38):2585–2594. DOI: https://doi.org/10.1093/eurheartj/ehv338
- Kittleson MM, Ambardekar AV, Cheng RK, et al. Transthyretin Cardiac Amyloidosis Evaluation and Management: 2025 ACC Concise Clinical Guidance. J Am Coll Cardiol. 2026;87(5):549–565. DOI: https://doi.org/10.1016/j.jacc.2025.09.004
- Tubben A, Tingen HSA, Prakken NHJ, et al. Prevalence of wild-type transthyretin amyloidosis in a prospective heart failure cohort with preserved and mildly reduced ejection fraction (Amylo-VIP-HF). Eur J Heart Fail. 2024;26(3):695–698. DOI: https://doi.org/10.1002/ejhf.3186