
Delirium Prevention: 5 Practical Approaches Compared
Multicomponent care remains the only broadly effective way to keep hospitalised patients lucid — while most sedatives and antipsychotics fall short, and one infusion earns a place in a single setting.
1-min One-Minute Takeaway
- Delirium prevention works best through multicomponent non-pharmacological care: pooled randomised and matched trials show incidence roughly halved (OR 0.47, 95% CI 0.38–0.58), with a number needed to treat near 14.Verified
- No medication matches that breadth. Prophylactic haloperidol did not lower delirium or improve 28-day survival among 1,789 ICU patients.Verified
- One drug is a genuine exception in one setting: low-dose dexmedetomidine cut delirium from 23% to 9% (OR 0.35) in older post-surgical ICU patients.Verified
- Melatonin’s effect is inconsistent across meta-analyses; cholinesterase inhibitors failed and signalled higher mortality, halting one trial early.Verified
- Guidelines recommend a tailored multicomponent package first and advise against antipsychotics for prevention.
Why Delirium Prevention Matters
Delirium is an acute, fluctuating disturbance of attention and cognition, and it is one of the most common complications of hospitalisation in older adults. Depending on the setting, it affects up to half of hospitalised older patients, and the majority of episodes go unrecognised.
The consequences extend far beyond a confused night. Delirium in older patients is associated with higher mortality, new institutionalisation, and incident dementia after discharge, based on a large meta-analysis of cohort studies. It is also the leading contributor to hospital falls.
The most important point for clinicians is that a substantial share is preventable. At least 30% to 40% of delirium cases can be averted by addressing modifiable risk factors before delirium develops. That makes delirium prevention a genuine clinical lever rather than an aspiration.
Prevention also carries economic weight, because delirium adds substantially to the cost of a hospital admission. The practical question this review addresses is which delirium prevention strategy actually delivers on that potential, and how the leading options compare head to head.
The Clinical Problem in Delirium Prevention
Delirium is multifactorial. It emerges from the interaction between predisposing vulnerabilities — age, cognitive impairment, sensory deficits, frailty — and acute precipitants such as infection, surgery, sedatives, dehydration, and immobility. Rarely does a single cause explain a single case.
This multifactorial nature shapes two competing philosophies of prevention. One approach modifies as many risk factors as possible at once through structured nursing and multidisciplinary care. The other targets a single neurotransmitter pathway with a drug.
Each pharmacological candidate reflects a mechanistic hypothesis: dopamine excess motivates antipsychotics, cholinergic deficiency motivates cholinesterase inhibitors, circadian disruption motivates melatonin, and sympathetic and sleep pathways motivate dexmedetomidine. The clinical instinct to “give something” is strong. Whether that instinct is supported by evidence is the crux of the comparison below.
There is a structural reason to be sceptical of a single-drug fix. A medicine acting on one pathway is unlikely to neutralise the many converging insults that produce delirium, which is why the most effective delirium prevention has tended to be multifactorial rather than molecular.
Available Approaches
The table summarises the strongest comparative evidence for each of the five delirium prevention approaches. Effect sizes are drawn from systematic reviews, meta-analyses, and the landmark randomised or matched trials that anchor this field. Every figure below traces to a primary source retrieved for this review.
| Source | Design | N | Population | Approach | Key result | Tier |
|---|---|---|---|---|---|---|
| Hshieh 2015 | MA of 14 studies | 4,267 | Older hospitalised (medical & surgical) | Multicomponent | Delirium OR 0.47 (0.38–0.58); NNT ≈14; falls OR 0.38 (0.25–0.60) | V |
| Inouye 1999 (HELP) | Controlled trial, prospective matching | 852 | Medical inpatients ≥70 | Multicomponent | Delirium 9.9% vs 15.0%; matched OR 0.60 (0.39–0.92) | V |
| Siddiqi 2016 (Cochrane) | Systematic review, 39 trials | — | Hospitalised non-ICU | Multicomponent | Incidence reduced by about one-third vs usual care (moderate certainty) | V |
| Su 2016 | RCT | 700 | ≥65, post non-cardiac surgery, ICU | Dexmedetomidine | Delirium 9% vs 23%; OR 0.35 (0.22–0.54) | V |
| van den Boogaard 2018 (REDUCE) | RCT | 1,789 | ICU, high delirium risk | Haloperidol | No effect on 28-day survival or delirium incidence | V |
| Neufeld 2016 | Systematic review & MA | — | Hospitalised adults | Antipsychotics | No reduction in delirium incidence; evidence does not support use | V |
| Oh & Neufeld 2019 | Systematic review (AHRQ) | — | Hospitalised adults | Antipsychotics | Typical & atypical agents did not reduce incidence vs placebo | V |
| Campbell 2019 | MA (surgical) | — | Older surgical patients | Melatonin/ramelteon | POD OR 0.63 (0.46–0.87) but high heterogeneity (I²=72%); other pooled analyses null | S |
| van Eijk 2010 | RCT (halted early) | 104 | ICU patients with delirium | Rivastigmine | No shorter delirium; higher mortality signal; stopped by safety board | V |
Multicomponent Non-Pharmacological Care Strongest evidence
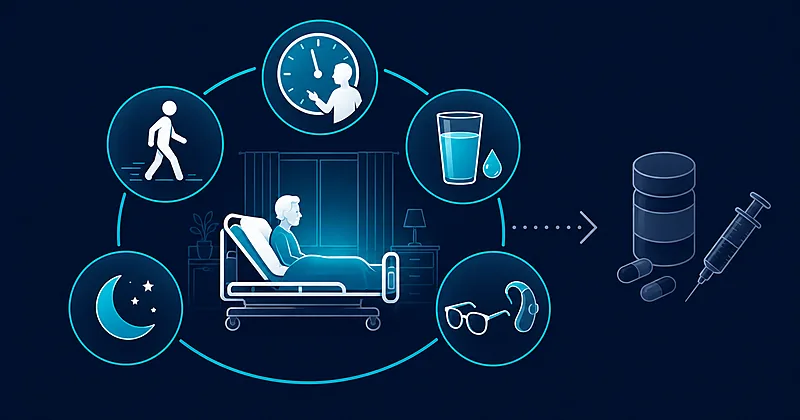
Multicomponent care is the founding and best-supported strategy. The original Hospital Elder Life Program tested standardised protocols for six risk factors: cognitive impairment, sleep deprivation, immobility, visual impairment, hearing impairment, and dehydration. In its landmark matched trial of 852 medical inpatients, delirium developed in 9.9% of the intervention group versus 15.0% with usual care (matched OR 0.60, 95% CI 0.39–0.92).
That signal has been reproduced at scale. A meta-analysis of 14 studies and roughly 4,267 patients found the odds of delirium roughly halved with multicomponent care (OR 0.47, 95% CI 0.38–0.58), with a number needed to treat near 14. Among the higher-quality randomised or matched trials, incidence fell by 44% (OR 0.56, 95% CI 0.42–0.76).
A separate benefit is fall prevention. The same analysis found the odds of falling reduced by more than 60% (OR 0.38, 95% CI 0.25–0.60) — a meaningful secondary gain, since delirium is a leading driver of hospital falls. A Cochrane review of 39 trials reached a concordant conclusion: multicomponent interventions reduce delirium incidence by about one-third in non-ICU inpatients.
This convergence across independent reviews is what gives multicomponent delirium prevention its unusual credibility. The approach is also the one for which cost-effectiveness has been most consistently described, reflecting fewer delirium episodes, fewer falls, and the downstream costs each avoids.
The multicomponent effect is remarkably setting-agnostic. It has been demonstrated across general medical wards, geriatric units, and surgical populations, in academic and community hospitals alike. No single component is the “active ingredient”; the benefit comes from correcting several risk factors at once, which mirrors how delirium actually arises.
Antipsychotics No prevention benefit
Antipsychotics remain the most frequently prescribed drugs for delirium, often given prophylactically. The evidence does not justify that practice for prevention. The REDUCE trial randomised 1,789 critically ill adults at high delirium risk to haloperidol 1 mg, haloperidol 2 mg, or placebo. Prophylactic haloperidol did not improve 28-day survival, the primary outcome, and did not reduce delirium incidence or length of stay.
Pooled evidence agrees. A systematic review and meta-analysis concluded that current evidence does not support antipsychotics for preventing or treating delirium. A later, rigorous review commissioned for United States practice found that neither typical nor atypical agents reduced delirium incidence, duration, severity, length of stay, or mortality compared with placebo.
Antipsychotics also carry real harms, including sedation, extrapyramidal effects, and QT prolongation. Guidance is explicit that these drugs should be used with particular caution, or avoided, in people with Parkinson’s disease or dementia with Lewy bodies. For prevention, the risk-benefit balance points away from routine use.
Dexmedetomidine Effective in one setting
Dexmedetomidine is the one drug with convincing prevention evidence — within a defined niche. In a randomised trial of 700 patients aged 65 or older admitted to intensive care after non-cardiac surgery, a low-dose overnight infusion cut delirium in the first postoperative week from 23% to 9% (OR 0.35, 95% CI 0.22–0.54). At this sub-sedative dose, hypotension and bradycardia did not differ from placebo, and hypertension and tachycardia were actually less frequent.
The signal is not isolated. A meta-analysis of 18 trials and 3,309 surgical patients found a consistent reduction in postoperative delirium (OR 0.35, 95% CI 0.24–0.51), with firm evidence on trial sequential analysis and effects in both cardiac and non-cardiac surgery.
The caveats define its scope. The benefit is established in monitored perioperative and ICU settings, not on general wards. Dexmedetomidine is a sedative infusion requiring continuous monitoring, and the landmark trial studied a relatively low-severity population with some baseline imbalance. It is best understood as a setting-specific adjunct, not a replacement for multicomponent care.
Melatonin and Ramelteon Inconsistent
Melatonin and the melatonin-receptor agonist ramelteon are attractive because they are low-risk and target the sleep-wake disruption common in delirium. The evidence, however, is genuinely inconsistent. One meta-analysis of older surgical patients found melatonin reduced postoperative delirium (OR 0.63, 95% CI 0.46–0.87), but with high heterogeneity (I²=72%), and removing a single study shifted the estimate substantially.
Other pooled analyses reach different conclusions. Some report no significant effect overall, and analyses restricted to ICU patients have been null. Effects appear concentrated at higher melatonin doses and in surgical patients, while the ramelteon evidence base is smaller and less consistent. Preliminary evidence suggests melatonin may help selected surgical patients, but the inconsistency across trials means it is not established for routine prevention.
Cholinesterase Inhibitors Failed and harmful
The cholinergic-deficiency hypothesis made cholinesterase inhibitors mechanistically plausible, but trials have been discouraging. A randomised trial in cardiac surgery found no preventive benefit from rivastigmine. More striking was a multicentre ICU trial that added rivastigmine to usual care with haloperidol in patients with delirium.
Rivastigmine did not shorten delirium and was associated with higher mortality, prompting the independent safety board to halt the trial early. The investigators recommended against its use in critically ill patients. This safety signal has effectively removed cholinesterase inhibitors from delirium prevention and treatment protocols.
Comparative Analysis
Placed side by side, the five delirium prevention approaches separate along three axes: how broadly they apply, how consistently they work, and how safe they are. Ranking them on these axes, rather than on any single trial, is what makes the comparison clinically useful.
On breadth, multicomponent care stands alone. It applies to essentially any at-risk hospitalised older adult, on any ward. Dexmedetomidine applies only to monitored perioperative and ICU patients. Antipsychotics, melatonin, and cholinesterase inhibitors have no population in which they reliably prevent delirium.
On consistency, the multicomponent effect is reproduced across many trials and multiple meta-analyses, all pointing the same direction. Dexmedetomidine is consistent within its surgical niche. Melatonin is inconsistent between analyses, antipsychotics are consistently null, and cholinesterase inhibitors are null or harmful.
On safety, multicomponent care has no pharmacological downside and reduces falls as a bonus. Dexmedetomidine needs monitoring but was well tolerated at low dose. Antipsychotics carry sedation, movement, and cardiac risks; cholinesterase inhibitors raised mortality.
For routine, generalisable prevention, multicomponent non-pharmacological care outperforms every drug: it is broader, more consistent, safer, and the only strategy guidelines recommend as first-line. Dexmedetomidine is the honest exception — genuinely effective, but only as a targeted adjunct in surgical and ICU care. No medication substitutes for the multicomponent foundation.
Quality and Consistency of the Evidence
Certainty differs sharply by approach and by outcome, and honest delirium prevention practice depends on grading each option rather than treating them as equivalent. The ratings below reflect the strength and consistency of the underlying trials.
- Multicomponent care — delirium incidence: Moderate to high. Multiple randomised and matched trials and several meta-analyses agree on a roughly one-third to one-half reduction. Blinding is inherently difficult and some included trials were non-randomised, which tempers certainty.
- Dexmedetomidine — post-surgical/ICU delirium: Moderate. Randomised trials plus a meta-analysis with trial sequential analysis show a reproducible effect, but the evidence is confined to monitored settings and some trials had baseline imbalances.
- Antipsychotics — prevention: Moderate-certainty null. Consistent absence of benefit across systematic reviews, including a large randomised trial, supports a clear “does not prevent” conclusion.
- Melatonin/ramelteon: Low. High heterogeneity and directly conflicting meta-analyses leave the effect uncertain and dose-dependent.
- Cholinesterase inhibitors: Low, with a safety concern. No benefit for prevention and a mortality signal in treatment.
What the Evidence Does Not Show
Multicomponent care reduces incidence, not every downstream harm. Pooled analyses have not shown statistically significant reductions in length of stay (mean difference −0.16 day, 95% CI −0.97 to 0.64) or institutionalisation (OR 0.95, 95% CI 0.71–1.26). The strongest, most reproducible benefit is on delirium occurrence and falls.
The active components are undefined. Trials bundle two to thirteen elements, and which ones matter most is unresolved.
Dexmedetomidine outside monitored settings is unproven, and its optimal dose, timing, and head-to-head standing against other sedatives remain open.
Whether preventing delirium prevents later dementia is not established by prevention trials, despite the known association between delirium and subsequent cognitive decline.
Practical Implications
The evidence supports a clear hierarchy for delirium prevention, framed as what the data back rather than as directives. The sequence below moves from the broadly supported foundation to narrow, setting-specific adjuncts.
For any at-risk hospitalised older adult, a tailored multicomponent package is the evidence-supported foundation. Its typical elements are reorientation, early mobilisation, sleep hygiene, adequate hydration and nutrition, provision of glasses and hearing aids, and review of deliriogenic medications. This is the strategy guidelines endorse first, delivered by a trained multidisciplinary team.
In the perioperative and ICU setting, low-dose dexmedetomidine may be considered as a monitored adjunct where clinically appropriate. It complements, rather than replaces, the multicomponent approach.
Antipsychotics should not be used to prevent delirium. Their role, if any, is short-term management of severe agitation or distress in established delirium, used cautiously and briefly. Cholinesterase inhibitors have no place in prevention, and melatonin’s weak, inconsistent evidence makes it at most an optional low-risk adjunct in selected patients.
Read together, these points describe a single delirium prevention posture: invest first in the multidisciplinary, non-pharmacological package for everyone at risk, treat dexmedetomidine as a monitored surgical or ICU option, and resist reflexive prescribing where the evidence does not support it.
Evidence Grade and Bottom Line
Bottom line
- Multicomponent non-pharmacological care is the most effective and most broadly applicable delirium-prevention strategy, roughly halving incidence and reducing falls, and is recommended first-line.
- No drug prevents delirium as broadly or as safely. Antipsychotics do not prevent it and carry harms; cholinesterase inhibitors failed and signalled higher mortality.
- Low-dose dexmedetomidine is the one genuinely effective agent, but only as a monitored adjunct in surgical and ICU patients.
- Melatonin’s benefit is inconsistent and dose-dependent, so it cannot be relied upon for routine prevention.
- The practical message: build prevention on the multicomponent foundation for everyone at risk, and add drugs only where the evidence specifically supports them.
Article Information and References
References
- Hshieh TT, Yue J, Oh E, et al. Effectiveness of multicomponent nonpharmacological delirium interventions: a meta-analysis. JAMA Intern Med. 2015;175(4):512–520. DOI: https://doi.org/10.1001/jamainternmed.2014.7779
- Siddiqi N, Harrison JK, Clegg A, et al. Interventions for preventing delirium in hospitalised non-ICU patients. Cochrane Database Syst Rev. 2016;(3):CD005563. DOI: https://doi.org/10.1002/14651858.CD005563.pub3
- Neufeld KJ, Yue J, Robinson TN, Inouye SK, Needham DM. Antipsychotic medication for prevention and treatment of delirium in hospitalized adults: a systematic review and meta-analysis. J Am Geriatr Soc. 2016;64(4):705–714. DOI: https://doi.org/10.1111/jgs.14076
- Oh ES, Needham DM, Nikooie R, et al. Antipsychotics for preventing delirium in hospitalized adults: a systematic review. Ann Intern Med. 2019;171(7):474–484. DOI: https://doi.org/10.7326/M19-1859
- Nikooie R, Neufeld KJ, Oh ES, et al. Antipsychotics for treating delirium in hospitalized adults: a systematic review. Ann Intern Med. 2019;171(7):485–495. DOI: https://doi.org/10.7326/M19-1860
- Campbell AM, Axon DR, Martin JR, Slack MK, Mollon L, Lee JK. Melatonin for the prevention of postoperative delirium in older adults: a systematic review and meta-analysis. BMC Geriatr. 2019;19(1):272. DOI: https://doi.org/10.1186/s12877-019-1297-6
- Witlox J, Eurelings LS, de Jonghe JF, Kalisvaart KJ, Eikelenboom P, van Gool WA. Delirium in elderly patients and the risk of postdischarge mortality, institutionalization, and dementia: a meta-analysis. JAMA. 2010;304(4):443–451. DOI: https://doi.org/10.1001/jama.2010.1013
- Inouye SK, Bogardus ST Jr, Charpentier PA, et al. A multicomponent intervention to prevent delirium in hospitalized older patients. N Engl J Med. 1999;340(9):669–676. DOI: https://doi.org/10.1056/NEJM199903043400901
- Su X, Meng ZT, Wu XH, et al. Dexmedetomidine for prevention of delirium in elderly patients after non-cardiac surgery: a randomised, double-blind, placebo-controlled trial. Lancet. 2016;388(10054):1893–1902. DOI: https://doi.org/10.1016/S0140-6736(16)30580-3
- van den Boogaard M, Slooter AJC, Brüggemann RJM, et al. Effect of haloperidol on survival among critically ill adults with a high risk of delirium: the REDUCE randomized clinical trial. JAMA. 2018;319(7):680–690. DOI: https://doi.org/10.1001/jama.2018.0160
- van Eijk MMJ, Roes KCB, Honing MLH, et al. Effect of rivastigmine as an adjunct to usual care with haloperidol on duration of delirium and mortality in critically ill patients: a multicentre, double-blind, placebo-controlled randomised trial. Lancet. 2010;376(9755):1829–1837. DOI: https://doi.org/10.1016/S0140-6736(10)61855-7
- National Institute for Health and Care Excellence. Delirium: prevention, diagnosis and management in hospital and long-term care. NICE guideline CG103. Available at: https://www.nice.org.uk/guidance/cg103