
Deprescribing in Older Adults: Which Drug Classes Have Real Stop Evidence
Where randomised trials support stopping a medication — and where the case for continuing still holds.
One-Minute Takeaway
What the evidence supports
- Deprescribing in older adults has its strongest randomised-trial support for two drug classes — benzodiazepines and antipsychotics — where planned withdrawal is feasible and, for antipsychotics, linked to better survival.
- A mailed patient-education programme discontinued benzodiazepines in 27% of chronic users versus 5% with usual care (risk difference 23%; number needed to treat 4).
- In Alzheimer’s disease, continuing antipsychotics carried higher long-term mortality than switching to placebo (hazard ratio 0.58 favouring withdrawal), without a clear cognitive cost to stopping.
- Reducing antihypertensives in adults aged 80+ was non-inferior for short-term blood-pressure control, and stopping statins near the end of life did not raise 60-day mortality while modestly improving quality of life.
- Proton pump inhibitors can often be stepped down, but symptom recurrence is common and the trial evidence is the weakest and least age-specific of these classes.
01Why Deprescribing in Older Adults Matters
Polypharmacy is now the default state of later life. Many adults over 65 take five or more regular medicines, and each added drug raises the risk of adverse drug events, falls, cognitive effects, and drug-related hospital admissions.
Deprescribing is the planned, supervised reduction or withdrawal of a medicine whose risks may outweigh its benefits for a particular person. The idea is intuitive; the evidence base is more uneven than the enthusiasm around it suggests.
The Page 2016 systematic review synthesised 132 studies. In non-randomised designs, deprescribing polypharmacy was associated with lower mortality, but that signal disappeared in the randomised trials, where the effect was not statistically significant.
An updated 2024 synthesis of over 250 studies reached the same headline conclusion: no overall mortality reduction across pooled designs, though subgroup benefits appeared in adults aged 65–79 and with individually tailored interventions. The practical reading is that most deprescribing is justified by reducing harm and treatment burden rather than by extending life.
Structured tools help clinicians decide what to target. The Beers Criteria and the STOPP/START framework both flag medications that are potentially inappropriate in older adults, and they anchor much of the deprescribing conversation. What follows examines the specific drug classes where discontinuation has been tested directly, class by class.
02A Practical Taxonomy of Deprescribing in Older Adults
The table below groups the classes with the most-cited discontinuation trials, sorted from the strongest to the most conditional stop-evidence. Every figure is drawn from the primary study or a systematic review, and each reference resolves to a real, published source.
| Study / source | Design | N | Population | Class & comparison | Key result |
|---|---|---|---|---|---|
| EMPOWER Tannenbaum 2014 | Cluster RCT | 303 | Community-dwelling, aged 65–95, chronic users | Benzodiazepines — patient education vs usual care | 27% vs 5% discontinued at 6 months; risk difference 23% (95% CI 14–32); NNT 4 |
| DART-AD Ballard 2009 | Placebo-controlled discontinuation RCT | 165 | Alzheimer’s disease in UK care homes | Antipsychotics — continue vs withdraw to placebo | Mortality HR 0.58 (95% CI 0.35–0.95) favouring withdrawal; 24-month survival 46% vs 71% |
| OPTIMISE Sheppard 2020 | Non-inferiority RCT | 569 | Aged 80+, controlled BP, ≥2 agents | Antihypertensives — reduce by one vs continue | SBP <150 mmHg: 86.4% vs 87.7%; adjusted RR 0.98 (97.5% CI 0.92–∞), non-inferior; mean SBP +3.4 mmHg |
| Kutner 2015 | Pragmatic RCT | 381 | Advanced, life-limiting illness on statins | Statins — discontinue vs continue | 60-day mortality 23.8% vs 20.3% (90% CI −3.5 to 10.5), not significant; quality of life better with stopping |
| Boghossian 2017 (Cochrane) | SR of 6 RCTs | 1,758 | Adults on long-term PPIs (mostly middle-aged) | PPIs — on-demand / abrupt vs continued | On-demand use cut consumption by 3.8 pills/week (95% CI −4.73 to −2.84); symptom recurrence common; low-to-moderate certainty |
| Page 2016 | SR / meta-analysis (132 studies) | 34,143 | Older adults, mixed classes | Any medication — deprescribe vs continue | Mortality OR 0.32 (95% CI 0.17–0.60) in non-randomised; OR 0.82 (0.61–1.11) in randomised studies |
Five drug classes carry class-specific discontinuation trials; the sixth row is the cross-class synthesis that frames them. The class sections that follow read each result in context, including where the design limits how far it should be pushed.
03Benzodiazepines and Z-Drugs: The Strongest Case
Chronic benzodiazepine and Z-drug use in older adults is associated with falls, fractures, and cognitive impairment, yet long-term prescriptions persist. This is the class where a randomised trial most cleanly showed that stopping is achievable.
The EMPOWER cluster randomised trial mailed a plain-language brochure describing the harms of sedative-hypnotics and a stepwise tapering schedule directly to patients. At six months, 27% of the intervention group had discontinued their benzodiazepine, compared with 5% under usual care.
Clinical pearl
The active ingredient in EMPOWER was patient activation, not a prescriber order. Sixty-two percent of recipients started a conversation about stopping with their physician or pharmacist, and the number needed to treat to achieve one discontinuation was just four.
Because EMPOWER was randomised, its result supports causal language: the intervention led to more discontinuation. The effect held in a later analysis of participants with mild cognitive impairment, suggesting the approach is not limited to fully intact patients. The same brochure model has been applied to Z-drugs, which share the falls and sedation profile that motivates withdrawal.
The caution is that EMPOWER measured discontinuation, not downstream falls or fractures. The class earns its top ranking here for demonstrating feasibility with low risk and a large effect, which is exactly what a clinician needs before initiating a taper.
04Antipsychotics in Dementia: Withdrawal With a Survival Signal
Antipsychotics are widely prescribed for the neuropsychiatric symptoms of dementia despite regulatory warnings about mortality. The DART-AD programme tested what happens when they are withdrawn.
In the withdrawal trial, 165 patients with Alzheimer’s disease in care facilities were randomised to continue their antipsychotic or switch to an identical placebo. The companion cognitive analysis found no significant difference in cognitive decline between continuing and stopping, indicating that many patients can be withdrawn without measurable cognitive worsening.
The long-term follow-up was more striking than the cognitive result. Patients randomised to continue antipsychotics had higher mortality over the extended follow-up, with survival curves separating progressively after the first year. This is a randomised comparison, so the mortality difference is more than an association of confounded prescribing.
The evidence is not a blanket instruction to stop every antipsychotic. A minority of patients with severe, distressing symptoms relapse after withdrawal, and other discontinuation studies report symptom recurrence in that subgroup. The defensible reading is that most patients warrant a monitored withdrawal attempt, with continuation reserved for those whose symptoms clearly return.
05Antihypertensives: Safe to Reduce, Short-Term
Blood-pressure trials rarely recruited the frail, multimorbid patients who now dominate primary-care registers, and antihypertensives contribute to hypotension, dizziness, and falls. OPTIMISE asked whether one agent could be removed without losing control.
Among 569 patients aged 80 and older with controlled pressure on at least two agents, removing one antihypertensive was non-inferior to usual care for the proportion staying below 150 mmHg at 12 weeks. Control was maintained in 86.4% of the reduction group versus 87.7% of those who continued.
What the numbers mean
Reduction came at a modest cost: mean systolic pressure rose 3.4 mmHg (95% CI 1.1–5.8), and the lower pill burden was sustained in about two-thirds of patients at 12 weeks. Serious adverse events did not differ meaningfully between groups.
The honest limitation is follow-up. OPTIMISE ran for 12 weeks, so it shows that a supervised reduction does not immediately destabilise blood pressure — not that long-term cardiovascular risk is unchanged. Extended follow-up through electronic records later found no clear association between deprescribing and hospitalisation or mortality, but that analysis was underpowered for hard outcomes.
Reducing antihypertensives is therefore reasonable in selected older adults with frailty, hypotension, or a limited prognosis, provided pressure is monitored and treatment can be reinstated. It is a decision about burden and short-term safety, not a demonstration of long-term benefit.
06Statins Near the End of Life
Statins prevent cardiovascular events over years, a horizon that shrinks as illness advances. The Kutner trial tested discontinuation in people whose prognosis was measured in months.
Across 15 US palliative-care sites, 381 adults with advanced life-limiting illness and an estimated survival under a year were randomised to stop or continue a statin taken for prevention. Those on the medication for active cardiovascular disease were excluded.
Stopping did not increase 60-day mortality: 23.8% of the discontinuation group died versus 20.3% of those who continued, a non-significant difference. Median survival was numerically longer after stopping, quality-of-life scores were modestly better, and patients took fewer non-statin medicines.
Read this result carefully
The trial’s primary endpoint was changed from overall survival to 60-day mortality after both arms outlived expectations, and the non-inferiority comparison was formally inconclusive. The finding supports stopping statins in limited life expectancy; it does not license withdrawal in robust older adults with years of expected survival.
Within its intended population, the message is practical. When a statin’s preventive payoff lies beyond a person’s likely lifespan, discontinuation is safe over the near term and eases pill burden and cost. That is a narrower claim than “statins can be stopped in the elderly,” and the distinction matters at the bedside.
07Proton Pump Inhibitors: Feasible but Symptom-Limited
Proton pump inhibitors are among the most over-continued medicines, frequently prescribed beyond their original indication. The Cochrane review by Boghossian and colleagues pooled the randomised evidence for stopping them.
Across six trials enrolling 1,758 adults, on-demand use reduced consumption by roughly 3.8 pills per week compared with continuous therapy. Most participants tolerated the change, and deprescribing clearly lowered drug exposure.
The trade-off was symptoms. Symptom recurrence was more common with on-demand or abrupt stopping than with continuous use, and abrupt discontinuation in particular carried a higher risk of rebound acid symptoms that prompted some patients to resume therapy. The certainty of evidence for patient-important outcomes was low to moderate.
Why this class ranks lowest here
Most PPI trials enrolled middle-aged adults with reflux, not the older, multimorbid population this review concerns. The stop-evidence is real but indirect for older adults, and it points to structured step-down with a recurrence plan rather than a clean discontinuation.
PPIs are still worth deprescribing where the indication has lapsed, but the approach differs from the sedative and antipsychotic classes. Step the dose down, offer on-demand dosing, and agree in advance how returning symptoms will be managed. Abrupt cessation invites rebound and erodes patient confidence in the plan.
08Comparative Analysis
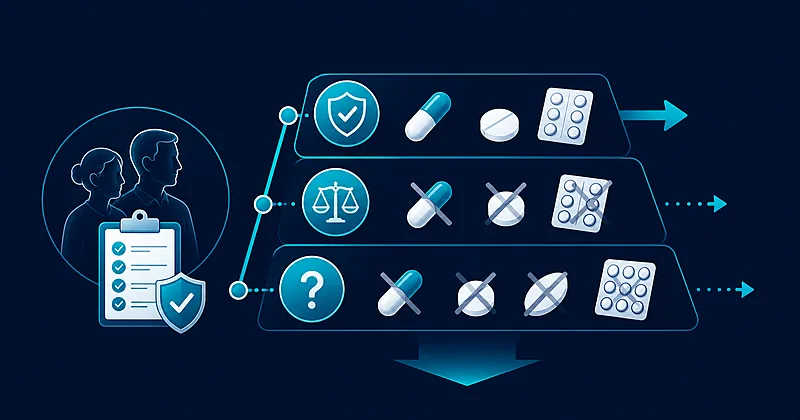
Reading the classes side by side, the stop-evidence separates into three tiers. Benzodiazepines and antipsychotics sit at the top: each has a randomised trial showing that withdrawal is feasible, and for antipsychotics continuation actively raised mortality. These are the classes where the evidence most confidently favours stopping.
Antihypertensives and statins occupy a middle tier. Both have a single strong randomised trial showing that reduction or discontinuation is safe over the short term in a defined population, but neither demonstrates long-term benefit, and the statin result is specific to limited life expectancy. The decision hinges on frailty, prognosis, and monitoring rather than on a universal rule.
Proton pump inhibitors form the most conditional tier. Deprescribing is feasible and reduces exposure, yet symptom recurrence is frequent and the trials sit largely outside the older-adult population. The action is a managed step-down, not a stop.
One cross-cutting finding tempers all of them. Pooled randomised evidence does not show that deprescribing extends life overall — the exception being antipsychotics in dementia. For most classes, the honest rationale is fewer adverse effects, lower burden, and lower cost, not longer survival.
09Quality and Consistency of the Evidence
Strength of evidence varies markedly across these classes, and matching the claim to the design is central to responsible deprescribing.
- Benzodiazepines — moderate to high. A well-conducted cluster randomised trial with a large, replicated discontinuation effect and low risk of harm from the intervention itself.
- Antipsychotics in dementia — moderate to high. A randomised withdrawal trial with a mortality signal on continuation, consistent with meta-analyses of excess mortality in this population.
- Antihypertensives — moderate. One good non-inferiority trial, but short follow-up and outcomes limited to blood-pressure control rather than cardiovascular events.
- Statins — low to moderate. A single pragmatic trial in a specific palliative population, with a changed primary endpoint and an inconclusive non-inferiority margin.
- Proton pump inhibitors — low. Randomised data exist but come largely from younger patients, rely on symptom outcomes, and carry low-to-moderate certainty.
Consistency is strongest where the intervention is low-risk and the population is well-defined. It weakens as the outcomes shift from feasibility toward hard clinical endpoints, which is precisely where the trials are shortest and smallest.
10What the Evidence Does Not Show
Specific, named gaps
These are the questions the current trials leave open, not a generic call for further study.
No randomised trial shows that deprescribing extends life across drug classes; the pooled mortality effect in randomised studies is neutral, with antipsychotic withdrawal the single exception. Claims that stopping medicines lengthens survival are not supported outside that setting.
Long-term outcomes after antihypertensive and statin discontinuation remain unmeasured. OPTIMISE and Kutner establish short-term safety only, so the cardiovascular consequences of sustained withdrawal over years are unknown.
The PPI evidence is not anchored in older adults, and hard endpoints such as fractures, pneumonia, and enteric infection after stopping are not well characterised. Withdrawal syndromes and rebound effects are also understudied across classes, and most trials excluded the frailest patients — the very group in whom deprescribing is most often considered.
11Practical Implications
The evidence supports a tiered, individualised approach rather than a single deprescribing protocol.
Benzodiazepines, Z-drugs, and antipsychotics in dementia are the highest-yield targets. For sedatives, patient-facing education paired with a stepwise taper has the clearest support. For antipsychotics, a monitored withdrawal is reasonable for most patients, with continuation reserved for genuine symptom relapse.
Antihypertensive and statin reduction fits patients with frailty, hypotension, adverse effects, or a limited prognosis. Reduce deliberately, monitor blood pressure or tolerability, and keep reinstatement available. For statins, prognosis is the deciding factor, and the strongest case is when preventive benefit lies beyond likely survival.
Proton pump inhibitors call for step-down and on-demand dosing rather than abrupt cessation, with an agreed plan for returning symptoms. Across every class, structured tools such as the Beers Criteria and STOPP/START help identify candidates, and shared decision-making with the patient anchors the choice. Where a drug can cause withdrawal effects, taper rather than stop outright.
12Evidence Grade and Bottom Line
Deprescribing in older adults is well justified as a strategy to cut harm and treatment burden, and it is demonstrably feasible. Its benefit is largest and best-evidenced for sedative-hypnotics and for antipsychotics in dementia, where withdrawal is safe and, for antipsychotics, linked to longer survival.
For antihypertensives and statins, the evidence licenses careful reduction in selected patients over the short term, framed around frailty and prognosis rather than a universal target. For proton pump inhibitors, a managed step-down suits most lapsed indications better than an abrupt stop. Across all classes, the realistic goal is a safer, lighter medication regimen — not, in general, a longer life.