
Cluster Headache Treatment: 3 Practical Approaches Compared
Matching fast-acting abortives, short-term bridges, and long-term prevention to the punishing rhythm of the attacks.
One-Minute Takeaway
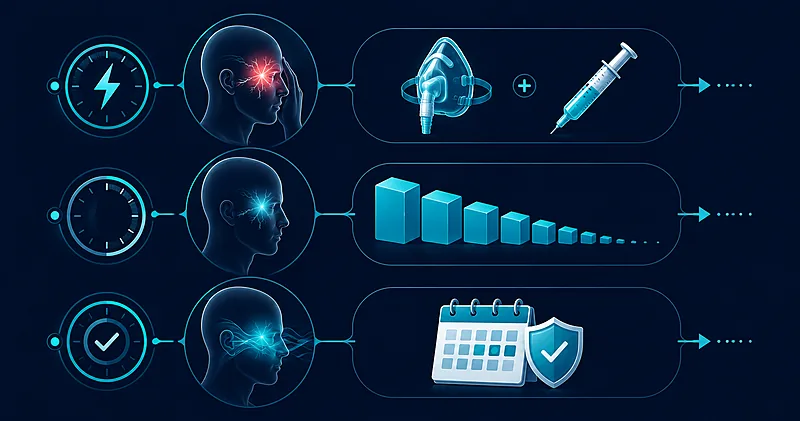
- Cluster headache treatment follows three evidence-based tiers — acute abortive, transitional (bridge), and preventive — each supported by randomised controlled trials.
- For acute attacks, inhaled high-flow oxygen left 78% of patients pain-free versus 20% with air in a randomised crossover trial.
- Subcutaneous sumatriptan 6 mg relieved 74% of attacks within 15 minutes, versus 26% with placebo.
- As a bridge while verapamil takes effect, oral prednisone reduced first-week attacks to 7.1 versus 9.5 on placebo.
- Verapamil is first-line prevention; galcanezumab helped episodic — not chronic — cluster headache, and 2023 European guidelines strongly back oxygen, injectable sumatriptan, and verapamil.
Why Cluster Headache Treatment Matters
Cluster headache is among the most severe pains in clinical medicine. Attacks are strictly unilateral, centred on the eye and temple, and accompanied by ipsilateral autonomic features such as tearing, nasal congestion, and eyelid drooping. Individual attacks last roughly 15 to 180 minutes and can recur up to eight times a day.
The disorder is relatively rare but disabling, and it is frequently misdiagnosed as migraine or sinus disease. This delay matters, because effective, well-tolerated treatments exist and are often underused. Getting the treatment framework right changes the daily experience of a condition that patients describe as unbearable.
Because a single attack peaks within minutes, and because preventive drugs take time to work, no one treatment suffices. Effective care combines a rapid abortive for the attack in progress, a short-term bridge to buy time, and a longer preventive to shorten the cluster period. This review compares those three approaches on the evidence that supports each.
The Clinical Problem
Three features of cluster headache define the therapeutic challenge and explain why a three-tier strategy is standard.
Attacks are too fast for oral drugs. Pain escalates from onset to peak within minutes, so an abortive must act within that window. Oral agents absorb too slowly to help a typical attack, which is why inhaled and injectable routes dominate acute care.
Preventives are slow to take effect. Verapamil, the usual first-line preventive, must be titrated upward gradually for tolerability and cardiac safety, so meaningful benefit can lag by one to several weeks. During that gap, attacks continue unless a faster-acting bridge is added.
The disease has two courses. In episodic cluster headache, bouts last weeks to months and remit; in chronic cluster headache, attacks persist with little or no remission. Much of the trial evidence comes from episodic patients, and several treatments that work in episodic disease have not shown the same benefit in chronic disease.
These constraints frame the comparison. The right question is not which single treatment is best, but how the acute, transitional, and preventive tiers combine to cover the attack, the gap, and the bout.
Available Approaches to Cluster Headache Treatment
The table below summarises the pivotal controlled trials behind each tier. Every sample size and effect estimate was confirmed against the primary source, and each row carries a resolving DOI in the reference list. The structure is organised by treatment role rather than by chronology.
| Study / Source | Tier | Design | N | Population | Intervention vs comparator | Key result |
|---|---|---|---|---|---|---|
| Cohen 2009 V | Acute | RCT, double-blind, crossover | 76 analysed (of 109) | Episodic + chronic | 100% oxygen 12 L/min ×15 min vs air | Pain-free/adequate relief at 15 min: 78% (95% CI 71–85) vs 20% (95% CI 14–26); P<.001 |
| Sumatriptan CH Study Group 1991 V | Acute | RCT, double-blind, crossover | 49 (39 evaluable) | Cluster headache | Subcutaneous sumatriptan 6 mg vs placebo | Response (no/mild pain) at 15 min: 74% vs 26%; P<.001 |
| Ekbom 1993 V | Acute | RCT, DB, crossover, multicentre | 134 | Cluster headache (in-patients) | Subcutaneous sumatriptan 6 mg & 12 mg vs placebo | Relief at 15 min: 75% (6 mg)/80% (12 mg) vs 35%; P<.001; 6 mg preferred on tolerability |
| Leroux 2011 V | Bridge | RCT, DB, placebo-controlled | 43 (21 vs 22) | >2 attacks/day (episodic + chronic) | Suboccipital cortivazol ×3 vs placebo (add-on) | ≤2 attacks/day after injection: 20/21 vs 12/22; OR 14.5 (95% CI 1.8–116.9); P=.012 |
| Obermann 2021 V | Bridge | RCT, DB, placebo-controlled, multicentre | 116 (109 analysed) | Episodic | Oral prednisone (100 mg ×5 d, tapered) + verapamil vs placebo + verapamil | Attacks in first week: 7.1 vs 9.5; difference −2.4 (95% CI −4.8 to −0.03); P=.002 |
| Leone 2000 V | Preventive | RCT, DB, double-dummy | 30 (15 vs 15) | Episodic | Verapamil 360 mg/day vs placebo ×14 d | Significant reduction in attack frequency and abortive use vs placebo (small trial) |
| Goadsby 2019 V | Preventive | RCT, DB, placebo-controlled | 106 (49 vs 57) | Episodic | Galcanezumab 300 mg SC monthly vs placebo | Δ weekly attacks (wk 1–3): −8.7 vs −5.2; difference 3.5 (95% CI 0.2–6.7); P=.04 |
Acute (abortive) therapy
Two treatments carry the strongest acute evidence: high-flow oxygen and subcutaneous sumatriptan. In Cohen 2009, a double-blind crossover randomised trial, inhaling 100% oxygen at 12 L/min for 15 minutes rendered patients pain-free or adequately relieved at 15 minutes far more often than air, 78% versus 20%. There were no important adverse events, which makes oxygen attractive for patients with cardiovascular risk.
Subcutaneous sumatriptan is the licensed acute drug. In the 1991 Sumatriptan Cluster Headache Study Group crossover trial, a 6 mg injection produced a response within 15 minutes in 74% of attacks versus 26% with placebo. The 1993 Ekbom dose-comparison trial confirmed the effect and found the 12 mg dose no better than 6 mg but more likely to cause adverse events, so 6 mg is the recommended dose.
Triptans carry vascular contraindications and daily-use limits, so they are not suitable for everyone or for very frequent attacks. Intranasal options offer an alternative when injection is not feasible: a randomised trial of intranasal sumatriptan showed benefit over placebo, and guidelines also list intranasal zolmitriptan. These nasal formulations act more slowly than the injection but improve tolerability and convenience.
Transitional (bridge) therapy
Transitional therapy suppresses attacks quickly while a slower preventive reaches an effective dose. Corticosteroids have been used for this purpose for decades, and Obermann 2021 provided the first large randomised support. Oral prednisone (100 mg for 5 days, then tapered) added to up-titrating verapamil reduced attacks in the first week to 7.1 versus 9.5 with placebo plus verapamil.
Local steroid injection is the other bridge with trial support. In Leroux 2011, repeated suboccipital injections of cortivazol in patients having more than two attacks per day sharply increased the chance of dropping to two or fewer daily attacks, with an odds ratio of 14.5, and reduced the attack count over the first 15 days. The confidence interval was wide because the trial was small, so the size of the benefit is uncertain even though the direction is clear.
Clinical pearl
The bridge is defined by its purpose, not its drug. Whether by oral prednisone or an occipital steroid injection, transitional treatment exists to cover the days-to-weeks lag before a preventive works — then it is tapered or stopped, because repeated or prolonged steroid exposure carries its own risks.
Preventive therapy
Verapamil is the standard first-line preventive. Leone 2000, a small double-blind, double-dummy randomised trial, found a significant reduction in attack frequency and abortive use with verapamil 360 mg/day versus placebo over 14 days. The trial base is modest and the doses used in practice are often higher, guided by response and cardiac tolerability rather than by large randomised data.
Galcanezumab, a monoclonal antibody against calcitonin gene-related peptide, is the newest option with randomised support. In Goadsby 2019, galcanezumab 300 mg monthly reduced weekly attacks across weeks 1 to 3 by 8.7 versus 5.2 with placebo, a difference of 3.5 attacks per week. The effect narrowed over weeks 4 to 8, and a parallel trial in chronic cluster headache did not meet its primary endpoint.
Additional preventives are used as alternatives or second-line. The 2023 European Academy of Neurology guideline lists lithium and topiramate as alternative preventives, with lithium positioned as a second choice when verapamil is ineffective or contraindicated. Their controlled evidence is more limited than that for verapamil, and lithium in particular did not show efficacy in a randomised trial in episodic cluster headache.
Comparative Analysis
The three tiers answer different clinical questions, so they are complementary rather than competing. Comparing them means asking what each is for, how fast it acts, and how strong the evidence is.
Speed and role. Acute therapy targets the attack in progress and must act within minutes; oxygen and injectable sumatriptan both meet that bar. Bridge therapy acts over days to suppress a run of attacks. Preventive therapy acts over weeks to shorten the whole bout. No tier substitutes for another.
Strength of evidence. Acute care rests on the firmest foundation, with double-blind randomised trials for both oxygen and sumatriptan and consistent, large effects. Bridge and preventive evidence is real but thinner: the bridge trials are small or short, and the preventive base ranges from a small verapamil trial to a single positive galcanezumab trial in episodic disease.
Oxygen versus sumatriptan. These have not been compared head-to-head in a randomised trial, so the choice is individualised. Oxygen has an excellent safety profile and no vascular contraindications but requires equipment; sumatriptan is fast and portable but carries cardiovascular cautions and daily-use limits. Many patients use both, matching the tool to the setting.
Episodic versus chronic disease. The comparison shifts by course. Most positive preventive data come from episodic patients, and galcanezumab’s benefit did not carry over to chronic cluster headache. Chronic patients therefore rely more heavily on verapamil, on careful titration, and on specialist input where standard options fall short.
In short, the tiers are sequenced, not ranked: an abortive for every attack, a bridge when attacks are frequent and a preventive is being started, and a preventive to end the bout — with the acute layer resting on the strongest trials.
Quality and Consistency of the Evidence
Evidence strength varies markedly by treatment and by disease course. The ratings below reflect study design, sample size, and consistency across the retrieved trials.
- High — acute oxygen and subcutaneous sumatriptan: supported by double-blind randomised trials with large, consistent effects and clear safety signals. This is the sturdiest part of the evidence base.
- Moderate — transitional corticosteroids (oral prednisone; occipital injection): each supported by a randomised trial, but samples are small or short-term and dosing regimens are not standardised.
- Moderate — galcanezumab in episodic cluster headache: one positive randomised trial with a modest, partly time-limited effect on weekly attacks.
- Low to moderate — verapamil: widely used and guideline-endorsed as first-line, yet the randomised evidence is a single small trial; higher clinical doses rest largely on observational data.
- Low — lithium and topiramate: used as alternatives with limited controlled evidence; lithium was negative in a randomised episodic-disease trial.
- Negative — galcanezumab in chronic cluster headache: the parallel randomised trial did not meet its primary endpoint, so the episodic benefit should not be extrapolated to chronic disease.
Across the field, effects are most consistent for acute treatment and least certain for prevention in chronic disease. Placebo-controlled trials are also harder to run because of the pain’s severity, which limits how much high-quality preventive evidence exists.
What the Evidence Does Not Show
Specific gaps
- No head-to-head randomised trial compares oxygen with subcutaneous sumatriptan, so the acute choice cannot be ranked on direct evidence.
- Verapamil’s optimal and maximum effective doses are not defined by randomised trials; high-dose use is guided by observation and cardiac monitoring, not trial data.
- Galcanezumab did not meet its primary endpoint in chronic cluster headache, and durable efficacy beyond the first few weeks in episodic disease is not established.
- Bridge steroid regimens lack a standardised, trial-validated dose and schedule, and long-term steroid safety limits how often they can be repeated.
- Chronic cluster headache is under-represented in randomised trials overall, so preventive care for these patients rests on weaker evidence than for episodic disease.
These are specific, named gaps rather than a blanket call for more study. They mark exactly where clinical judgement, monitoring, and shared decision-making fill in for absent trial data.
Practical Implications
The evidence supports offering both high-flow oxygen and subcutaneous sumatriptan as first-line abortives, chosen to fit the patient and the setting. Oxygen suits those with vascular risk or very frequent attacks; the injection suits those who need speed and portability. Many patients benefit from access to both.
For patients with frequent daily attacks or those starting a preventive, the evidence supports a transitional bridge. A tapering course of oral prednisone or a suboccipital steroid injection can suppress attacks while verapamil is up-titrated, after which the bridge is withdrawn.
The evidence supports verapamil as the first preventive to trial, titrated gradually with electrocardiographic monitoring as the dose rises, consistent with the 2023 European guideline. Galcanezumab is a reasonable option in episodic disease, particularly where standard preventives are not tolerated, but its role in chronic disease is not supported by the trial data.
Underpinning all of this is recognising the diagnosis. Because cluster headache is often mistaken for migraine or sinus disease, and because opioids are both ineffective and inappropriate here, the largest practical gain often comes from identifying the syndrome and applying the evidence-based tiers early.
Evidence Grade and Bottom Line
Overall grade: High for acute therapy · Moderate for bridge and prevention- Acute treatment is well established: oxygen and subcutaneous sumatriptan each work in double-blind randomised trials, with strong, consistent effects.
- Transitional therapy has genuine but limited randomised support; corticosteroids bridge the gap before a preventive works and are then tapered.
- Prevention centres on verapamil as first-line despite a modest trial base, with galcanezumab an evidence-based option in episodic — but not chronic — disease.
- The tiers are sequenced, not ranked: cover the attack, cover the gap, and shorten the bout, with acute care resting on the firmest evidence.
Article Information and References
- May A, Evers S, Goadsby PJ, et al. European Academy of Neurology guidelines on the treatment of cluster headache. Eur J Neurol. 2023;30(10):2955–2979. DOI: https://doi.org/10.1111/ene.15956
- Cohen AS, Burns B, Goadsby PJ. High-flow oxygen for treatment of cluster headache: a randomized trial. JAMA. 2009;302(22):2451–2457. DOI: https://doi.org/10.1001/jama.2009.1855
- The Sumatriptan Cluster Headache Study Group. Treatment of acute cluster headache with sumatriptan. N Engl J Med. 1991;325(5):322–326. DOI: https://doi.org/10.1056/NEJM199108013250505
- Ekbom K, Monstad I, Prusinski A, et al. Subcutaneous sumatriptan in the acute treatment of cluster headache: a dose comparison study. Acta Neurol Scand. 1993;88(1):63–69. DOI: https://doi.org/10.1111/j.1600-0404.1993.tb04189.x
- Obermann M, Nägel S, Ose C, et al. Safety and efficacy of prednisone versus placebo in short-term prevention of episodic cluster headache: a multicentre, double-blind, randomised controlled trial. Lancet Neurol. 2021;20(1):29–37. DOI: https://doi.org/10.1016/S1474-4422(20)30363-X
- Leroux E, Valade D, Taifas I, et al. Suboccipital steroid injections for transitional treatment of patients with more than two cluster headache attacks per day: a randomised, double-blind, placebo-controlled trial. Lancet Neurol. 2011;10(10):891–897. DOI: https://doi.org/10.1016/S1474-4422(11)70186-7
- Leone M, D’Amico D, Frediani F, et al. Verapamil in the prophylaxis of episodic cluster headache: a double-blind study versus placebo. Neurology. 2000;54(6):1382–1385. DOI: https://doi.org/10.1212/WNL.54.6.1382
- Goadsby PJ, Dodick DW, Leone M, et al. Trial of galcanezumab in prevention of episodic cluster headache. N Engl J Med. 2019;381(2):132–141. DOI: https://doi.org/10.1056/NEJMoa1813440
- van Vliet JA, Bahra A, Martin V, et al. Intranasal sumatriptan in cluster headache: randomized placebo-controlled double-blind study. Neurology. 2003;60(4):630–633. DOI: https://doi.org/10.1212/01.WNL.0000046589.45855.30