
Meningeal Artery Embolization for Chronic Subdural Hematoma
Five randomized trials now test whether blocking the dura’s blood supply prevents a hematoma from coming back — and the answer depends heavily on how you measure success.
One-Minute Takeaway
- Strong randomized evidence now supports middle meningeal artery embolization as an add-on to surgery for chronic subdural hematoma, where it lowers the need for repeat operations.
- In EMBOLISE, reoperation fell from 11.3% to 4.1% when embolization was added to surgery (RR 0.36, 95% CI 0.11–0.80); STEM cut composite treatment failure from 36% to 16% (NNT 5).
- Two trials were neutral on their primary endpoint — MAGIC-MT (recurrence 6.7% vs 9.9%) and EMPROTECT (14.8% vs 21%) — showing that benefit hinges on the outcome and population studied.
- Pooled analyses find a consistent drop in surgical rescue (RR 0.36, 95% CI 0.25–0.53) but no measurable functional-outcome gain and a possible rise in infections.
- Safety looks acceptable: serious embolization-related events were uncommon and disabling stroke or death did not increase, though standalone use rests on underpowered subgroups.
Why Meningeal Artery Embolization Matters
Chronic subdural hematoma is among the most common conditions neurosurgeons treat, and its incidence is climbing with an ageing, increasingly anticoagulated population. Projections suggest that evacuating a subdural collection will become the most common cranial neurosurgical procedure by 2030.
The persistent problem is durability, not initial drainage. After standard burr-hole surgery, symptomatic collections return in roughly 10–20% of patients. Each reoperation carries real risk in frail older adults with multiple comorbidities.
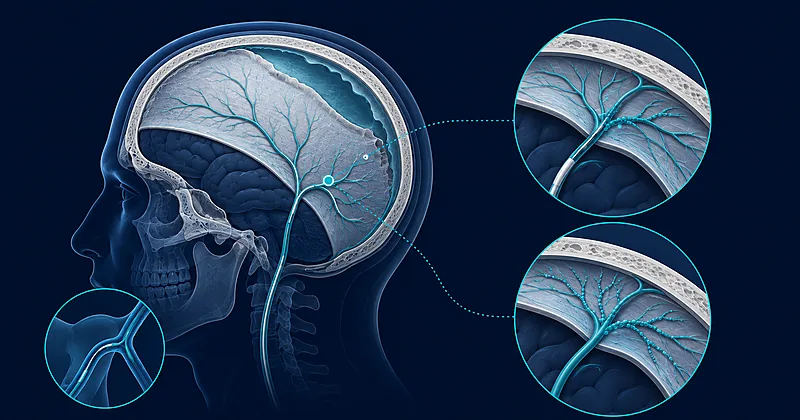
Blocking the middle meningeal artery targets the biology behind that recurrence. The artery supplies the fragile neomembranes lining the hematoma, whose leaky immature vessels keep re-bleeding into the subdural space. Devascularising them is intended to let the collection resorb and stay resolved.
Available Approaches
Five randomized controlled trials have now tested middle meningeal artery embolization. They differ in population, embolic agent, endpoint definition, and whether embolization was added to surgery or used as primary therapy. The table below summarises the pivotal evidence retrieved for this review.
| Trial / Source | Design | N | Population | Comparison | Key result |
|---|---|---|---|---|---|
| EMBOLISE (2024) | Multicenter RCT (US) | 400 | Symptomatic subacute/chronic SDH with a surgical indication | Surgery + MMA embolization (Onyx) vs surgery alone | Reoperation for recurrence/progression 4.1% vs 11.3%; RR 0.36 (95% CI 0.11–0.80) |
| STEM (2024/25) | Multicenter RCT (international) | 310 | Symptomatic chronic SDH ≥10 mm, surgical or nonsurgical standard care | Standard care + MMA embolization (Squid) vs standard care alone | Composite treatment failure at 180 d 16% vs 36%; OR 0.36 (95% CI 0.20–0.66); NNT 5 |
| MAGIC-MT (2024) | Multicenter RCT (China) | 722 | Symptomatic nonacute SDH with mass effect | MMA embolization (Onyx) ± burr-hole vs usual care | Symptomatic recurrence/progression at 90 d 6.7% vs 9.9%; difference −3.3% (95% CI −7.4 to 0.8), NS; serious adverse events 6.7% vs 11.6% |
| EMPROTECT (2025) | Multicenter RCT (France) | 342 | Post-surgical chronic SDH at high recurrence risk | Post-op MMA embolization (gelatin microspheres) vs standard medical care | Recurrence at 6 mo 14.8% vs 21%; adjusted OR 0.64 (95% CI 0.36–1.14), NS |
| Elgendy et al. 2025 | Meta-analysis (6 RCTs) | 1,544 | Nonacute SDH, adjunctive embolization | Adjunctive MMA embolization vs standard care | Surgical rescue 4.5% vs 12.7%, RR 0.36 (95% CI 0.25–0.53); recurrence RR 0.52 (95% CI 0.37–0.73); infection RR 1.81 (95% CI 1.23–2.66) |
| Gillespie et al. 2025 | Meta-analysis (3 RCTs) | 1,432 | Chronic SDH, surgical and nonsurgical strata | MMA embolization vs standard care | Overall RR 0.50 (95% CI 0.23–1.06), NS; nonsurgical stratum RR 0.36 (95% CI 0.22–0.60); functional outcome RR 1.01 (95% CI 0.97–1.04) |
SDH, subdural hematoma; MMA, middle meningeal artery; RR, relative risk; OR, odds ratio; CI, confidence interval; NS, not statistically significant; NNT, number needed to treat.
Embolization as a Surgical Adjunct
The strongest signal comes from adding embolization to surgery. EMBOLISE, which enrolled patients scheduled for evacuation, found that adjunctive embolization reduced reoperation for recurrence or progression roughly threefold. STEM, using a broader composite of treatment failure, reported a similarly large reduction.
The picture is not uniform. EMPROTECT embolized high-recurrence-risk patients after surgery and found a numerically lower recurrence rate that did not reach statistical significance. Notably, that trial used gelatin microspheres rather than a liquid embolic agent.
Standalone Embolization Without Surgery
Whether embolization can replace surgery in minimally symptomatic patients is far less settled. In pooled subgroup analysis, embolization reduced progression in nonsurgically managed patients (RR 0.36, 95% CI 0.22–0.60), and STEM’s nonsurgical stratum showed a large effect.
These stratum-level findings are hypothesis-generating, not definitive. The trials were not powered to compare standalone embolization against surgery directly, so the apparent advantage in nonsurgical candidates needs confirmation from adequately powered head-to-head studies.
Embolic Agents and Timing
The trials with the clearest efficacy signals used liquid ethylene-vinyl-alcohol agents (Onyx or Squid), which penetrate the distal meningeal network. The neutral EMPROTECT trial used particulate embolics, and its authors raised the possibility that agent choice influenced results.
Timing also varied. Adjunctive embolization was generally performed around the time of drainage, whereas EMPROTECT embolized within seven days after surgery. How agent, particle size, and timing interact remains an open technical question.
Comparative Analysis: Does Meningeal Artery Embolization Work?
The apparent disagreement between trials largely dissolves once the endpoints are lined up. Trials measuring a hard outcome — reoperation or a composite of treatment failure — were positive. Trials measuring softer symptomatic recurrence in mixed populations were neutral on that specific endpoint.
That pattern is consistent across pooled analyses. One meta-analysis of five large trials found lower odds of treatment failure with embolization (OR 0.51). A GRADE-assessed synthesis reported a clear reduction in surgical rescue (RR 0.36, 95% CI 0.25–0.53).
The verb still has to match the endpoint. For preventing a second operation, the evidence is strong and directionally consistent. For preventing any symptomatic recurrence as a standalone measure, results are mixed, and one three-trial analysis found the overall effect fell just short of significance (RR 0.50, 95% CI 0.23–1.06).
When comparing these trials, read the primary endpoint first. “Reoperation avoided” and “no symptomatic recurrence on imaging” are different bars, and embolization clears the first more convincingly than the second.
Quality and Consistency of the Evidence
The evidence base is now genuinely randomized, but its strength varies sharply by outcome. The colour-coded summary below reflects that unevenness.
- Reoperation / surgical rescue (adjunct to surgery): Strong evidence supports a reduction. Two positive trials and multiple meta-analyses agree, with low heterogeneity for surgical rescue.
- Symptomatic recurrence (mixed and nonsurgical populations): Evidence is mixed. Individual trials were neutral on this endpoint, and pooled estimates are sensitive to which trials are included.
- Standalone embolization vs surgery: Preliminary evidence suggests benefit in nonsurgical candidates, drawn from subgroup analyses not powered for the comparison.
- Functional and cognitive outcome: Evidence does not show a benefit. Pooled functional-outcome estimates cluster around no difference (RR 1.01).
- Short-term safety: Serious embolization-related events were uncommon, and disabling stroke or death did not increase; one synthesis flagged higher infection rates.
What the Evidence Does Not Show
Several specific gaps remain, and none is closed by the current trials. Distinguishing what is proven from what is merely plausible matters for how the procedure is offered.
First, no trial has demonstrated that embolization improves how patients actually function or think, as opposed to how their imaging looks. Second, standalone embolization has not been confirmed superior or equivalent to surgery in an adequately powered head-to-head design.
Third, durability beyond about six months, the optimal embolic agent and particle size, and the best patient-selection criteria are unresolved. The MEMBRANE trial has since reported its primary results, which also favoured adjunctive embolization on a composite of residual hematoma or reintervention; even so, longer-term durability and a direct head-to-head comparison of standalone embolization against surgery still await dedicated trials. The infection signal from pooled data also warrants continued surveillance.
Practical Implications
Recent society statements, including a consensus from the Society of Vascular and Interventional Neurology, now position middle meningeal artery embolization as a reasonable adjunctive option in appropriately selected patients. This reflects the consistent reoperation benefit rather than any claim that it replaces surgery.
For a patient facing evacuation who carries a higher recurrence risk, the evidence supports discussing adjunctive embolization as a way to reduce the chance of a second operation. The decision is shared, weighing frailty, anticoagulation, anatomy, and local expertise.
For minimally symptomatic patients, standalone embolization remains an option best framed as evidence-developing rather than established. Framing the conversation around what the data support — fewer reoperations, uncertain functional gain — keeps expectations aligned with the trials.
Evidence Grade and Bottom Line
Grade: Moderate–High (endpoint-dependent)Adjunctive middle meningeal artery embolization reduces reoperation and surgical rescue after treatment of chronic subdural hematoma, supported by two positive randomized trials and concordant meta-analyses. Confidence is high for that specific outcome.
Confidence drops for broader claims. Benefit on symptomatic recurrence in mixed populations is inconsistent, standalone use rests on underpowered subgroups, and no functional-outcome advantage has been shown. Safety appears acceptable in the short term.
Bottom line: The procedure works to prevent repeat operations when added to surgery. It is not yet a proven substitute for surgery, and it has not been shown to make patients function better — distinctions that should shape how it is offered.
Article Information and References
- Chen H, McIntyre MK, Kan P, Gandhi D, Colasurdo M. Middle Meningeal Artery Embolization for Nonacute Subdural Hematoma: A Meta-Analysis of Large Randomized Controlled Trials. AJNR Am J Neuroradiol. 2025;46(10):2069–2074. DOI: https://doi.org/10.3174/ajnr.A8781
- Elgendy MS, Rifai M, Taha AM, et al. Adjunctive middle meningeal artery embolization for non-acute subdural hematoma: a GRADE-assessed meta-analysis and trial sequential analysis on randomized trials. Acta Neurochir (Wien). 2025. DOI: https://doi.org/10.1007/s00701-025-06574-9
- Gillespie CS, Veremu M, Cook WH, et al. Middle meningeal artery embolization for chronic subdural hematoma: meta-analysis of three randomized controlled trials and review of ongoing trials. Acta Neurochir (Wien). 2025. DOI: https://doi.org/10.1007/s00701-025-06587-4
- Society of Vascular and Interventional Neurology Guidelines and Practice Standards Committee. Consensus Statement on Middle Meningeal Artery Embolization in Chronic Subdural Hematoma Treatment. Stroke Vasc Interv Neurol. 2025. DOI: https://doi.org/10.1161/SVIN.125.001814
- ARISE I Consensus Statement on the Management of Chronic Subdural Hematoma. Stroke. 2024;55(5):1438–1448. DOI: https://doi.org/10.1161/STROKEAHA.123.044129
- Davies JM, Knopman J, Mokin M, et al. Adjunctive Middle Meningeal Artery Embolization for Subdural Hematoma. N Engl J Med. 2024;391(20):1890–1900. DOI: https://doi.org/10.1056/NEJMoa2313472
- Fiorella D, Monteith SJ, Hanel R, et al. Embolization of the Middle Meningeal Artery for Chronic Subdural Hematoma. N Engl J Med. 2025;392(9):855–864. DOI: https://doi.org/10.1056/NEJMoa2409845
- Liu J, Ni W, Zuo Q, et al. Middle Meningeal Artery Embolization for Nonacute Subdural Hematoma. N Engl J Med. 2024;391(20):1901–1912. DOI: https://doi.org/10.1056/NEJMoa2401201
- Shotar E, Mathon B, Salle H, et al. Meningeal Embolization for Preventing Chronic Subdural Hematoma Recurrence After Surgery: The EMPROTECT Randomized Clinical Trial. JAMA. 2025;334(2):127–135. DOI: https://doi.org/10.1001/jama.2025.7583
- Zuo Q, Ni W, Yang P, et al. Managing non-acute subdural hematoma using liquid materials: a Chinese randomized trial of middle meningeal artery treatment (MAGIC-MT) — protocol. Trials. 2023;24(1):586. DOI: https://doi.org/10.1186/s13063-023-07608-2
- Shotar E, Mathon B, Rouchaud A, et al. Embolization of the middle meningeal artery for the prevention of chronic subdural hematoma recurrence in high-risk patients: the EMPROTECT study protocol. J Neurointerv Surg. 2024;17(e1):e172–e177. DOI: https://doi.org/10.1136/jnis-2023-021249