
Letrozole vs Clomiphene: Critical Findings in 3 Subgroups
An evidence synthesis of ovulation induction in polycystic ovary syndrome, focused on live birth rates, multiple gestation, and BMI subgroup outcomes.
One-Minute Takeaway on Letrozole vs Clomiphene
One-Minute Takeaway
- For letrozole vs clomiphene in anovulatory polycystic ovary syndrome, the strongest single trial — the 750-woman PPCOS II RCT — showed letrozole produced a cumulative live-birth rate of 27.5% versus 19.1% with clomiphene (rate ratio 1.44, 95% CI 1.10–1.87).
- The 2022 Cochrane systematic review (41 RCTs) concluded letrozole likely improves live birth and clinical pregnancy compared with clomiphene citrate, with moderate-certainty evidence and no detected difference in miscarriage.
- Multiple-gestation rates trend lower with letrozole (typically 3–5% twins vs 5–9% with clomiphene), with pooled relative risks consistent with a reduction of roughly half.
- BMI subgroup analyses in PPCOS II found letrozole’s advantage was most pronounced in the highest BMI tertile, where the live-birth gap roughly doubled compared with the lowest tertile.
- The 2023 International Evidence-Based PCOS Guideline endorses letrozole as the preferred first-line pharmacologic agent for ovulation induction in anovulatory PCOS without other infertility factors.
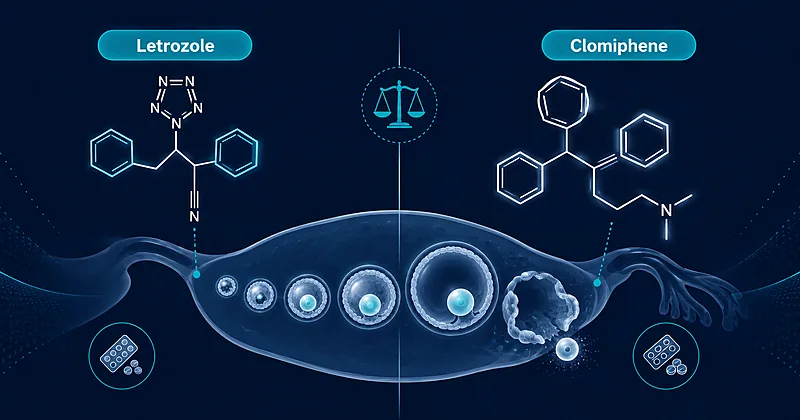
Why Letrozole vs Clomiphene Matters in PCOS
Polycystic ovary syndrome affects roughly 5–20% of women of reproductive age and accounts for most cases of anovulatory infertility. For decades, clomiphene citrate was the default first-line oral agent, having been used in clinical practice since the 1960s. The choice between letrozole vs clomiphene now sits at the centre of routine fertility counselling.
Clomiphene works as a selective estrogen-receptor modulator at the hypothalamus, raising FSH but also producing persistent peripheral anti-estrogenic effects on endometrium and cervical mucus. Letrozole, an aromatase inhibitor, transiently suppresses estrogen synthesis without blocking estrogen receptors. The mechanistic difference predicts a thicker endometrium and more monofollicular development with letrozole.
These pharmacologic predictions matter clinically. The two outcomes that drive shared decision-making are live birth per treatment course and the risk of multiple gestation, which carries excess maternal and neonatal morbidity. Subgroup behaviour by BMI further shapes counselling, because obesity is a major modifier of fertility-drug response in PCOS.
Over the past decade, the evidence base for letrozole vs clomiphene has shifted decisively. International guidelines from ASRM, ESHRE, and the 2023 International PCOS Network now recommend letrozole as the preferred first-line agent. Understanding the underlying evidence is essential for clinicians applying these recommendations in everyday practice.
Evidence Reviewed
This synthesis anchors on one landmark double-blind multicenter RCT, the most recent Cochrane systematic review, two additional contemporary meta-analyses, the largest available individual-participant data meta-analysis, the largest international guideline, and a safety-focused systematic review. Together these sources cover more than 9,000 randomised women across 40-plus trials.
| Study / Source | Design | Population (n) | Comparison | Primary Outcome |
|---|---|---|---|---|
| Legro 2014 (PPCOS II) | Double-blind RCT, 11 US sites | 750 PCOS women | Letrozole vs clomiphene, up to 5 cycles | Live birth: 27.5% vs 19.1% |
| Franik 2022 (Cochrane) | Systematic review & meta-analysis | 41 RCTs, ~6,000 women | Letrozole vs CC ± adjuncts | Improved live birth, moderate certainty |
| Wang 2019 (IPD-MA) | Individual participant data MA | 20 RCTs, 3,962 women | First-line OI agents in PCOS | Letrozole superior for live birth |
| Tsiami 2021 | Systematic review & MA | 26 RCTs, 4,168 women | Letrozole vs CC, TI/IUI | Ovulation RR 1.15 (1.08–1.22) |
| Roque 2015 | Systematic review & MA | 6 RCTs, ~1,300 women | Letrozole vs CC in PCOS | Higher live birth with letrozole |
| Diamond 2015 (AMIGOS) | RCT, NICHD Reprod Med Network | 900 women, unexplained infertility | Letrozole vs CC vs gonadotropin | Live birth lower with letrozole (non-PCOS) |
| Mejia 2019 | Randomised trial | 70 PCOS women | Letrozole + CC vs letrozole alone | Higher ovulation with combination |
| Tulandi 2006 | Retrospective multicenter cohort | 911 newborns | Letrozole vs CC pregnancies | Major anomaly: 1.2% vs 3.0% |
| Pundir 2021 | Systematic review & MA of safety | 46 studies, >6,000 pregnancies | Letrozole pregnancies vs comparators | No increased anomaly risk |
| Teede 2023 | International evidence-based guideline | 254 recommendations | PCOS-wide management | Letrozole = first-line OI |
The accordions below provide focused detail on the four sources that carry the most weight in current recommendations, including the trials that shaped guideline language.
The Pregnancy in Polycystic Ovary Syndrome II trial, led by Legro and the NICHD Reproductive Medicine Network, randomised 750 anovulatory women with PCOS (modified Rotterdam criteria) at 11 US sites. Treatment was double-blind for up to five cycles, with dose escalation in non-responders.
Cumulative live birth was the primary outcome. Letrozole produced 103 live births in 374 women (27.5%) versus 72 of 376 (19.1%) with clomiphene, a rate ratio of 1.44 (95% CI 1.10–1.87, p=0.007). Cumulative ovulation across cycles was 61.7% with letrozole and 48.3% with clomiphene.
Multiple gestation was 3.4% (letrozole) versus 7.4% (clomiphene); the trial was underpowered to detect significance for this secondary outcome (23% power). Congenital anomalies were rare and similar between groups. Side-effect profiles differed: more hot flushes with clomiphene, more fatigue and dizziness with letrozole.
The 2022 Cochrane update by Franik and colleagues pooled 41 randomised trials of aromatase inhibitors versus selective estrogen-receptor modulators in anovulatory PCOS women. The fourth iteration of this review applied GRADE certainty ratings to each outcome.
Letrozole was associated with higher live birth and clinical pregnancy than clomiphene, with moderate-certainty evidence after exclusion of high-risk-of-bias studies. The review found no meaningful difference in miscarriage rate or multiple pregnancy rate. The authors noted heterogeneity driven by dose, timing, and definition of PCOS.
The Cochrane synthesis is the basis for current ESHRE, ASRM, and 2023 International PCOS Network guideline language. Its conclusion that letrozole improves live birth aligns with the PPCOS II result while adding generalisability across populations.
The International Ovulation Induction IPD Collaboration pooled individual participant data from 20 randomised trials comparing first-line agents in PCOS, totalling 3,962 women. IPD methodology allowed analysis of treatment-by-subgroup interactions that aggregate meta-analysis cannot detect.
Letrozole was associated with higher pregnancy and live birth than clomiphene across the cohort. The IPD design permitted assessment of effect modification by BMI, baseline androgens, and PCOS phenotype. The advantage for letrozole was consistent across phenotypes, with magnitude greater at higher BMI.
Combination clomiphene plus metformin was compared with single-agent strategies; the marginal benefit of metformin in addition to clomiphene did not match the benefit of letrozole monotherapy in most subgroups. This finding supports a single-agent letrozole strategy as default for naive anovulatory PCOS patients.
The 2023 International Evidence-Based Guideline for the Assessment and Management of PCOS, led by Teede and the International PCOS Network, published in parallel across J Clin Endocrinol Metab, Hum Reprod, Fertil Steril, and Eur J Endocrinol. It includes 254 recommendations and practice points.
For infertility, the guideline recommends letrozole as the preferred first-line pharmacological therapy for ovulation induction in women with anovulatory PCOS and no other infertility factors. Clomiphene (alone or with metformin), gonadotropins, and ovarian surgery are positioned as second-line; IVF is third-line.
The guideline acknowledges that letrozole is used off-label for ovulation induction in many jurisdictions and notes no signal of increased teratogenicity compared with other agents. It calls for ongoing monitoring of offspring outcomes in registry studies.
Key Findings on Letrozole vs Clomiphene
Live birth: the central outcome
Across the major sources, letrozole vs clomiphene consistently favours letrozole for live birth in PCOS. PPCOS II delivered the cleanest single estimate at 27.5% versus 19.1% (rate ratio 1.44, 95% CI 1.10–1.87). Pooled meta-analyses produce a similar direction and magnitude.
Roque and colleagues reported a relative risk of 1.49 (95% CI 1.27–1.74) for live birth across eight randomised comparisons. The 2022 Cochrane review concluded the effect is moderate certainty, with the wider trial base reducing the chance that PPCOS II reflects a single-trial anomaly. The mechanism plausibly links to thicker endometrium and more physiologic follicular development.
Multiple gestation: consistently lower with letrozole
Multiple-gestation rate is the secondary outcome that most directly affects maternal and neonatal safety. In PPCOS II, twins occurred in 3.4% of letrozole pregnancies and 7.4% of clomiphene pregnancies; the trial was underpowered to confirm statistical significance for this outcome alone.
Larger cohorts and pooled analyses tell a more confident story. A 16,001-cycle IUI registry reported twins at 4.7% (letrozole) versus 7.5% (clomiphene) and triplets at 0.2% versus 1.3%. A recent pooled meta-analysis estimated a relative risk for multiple pregnancy of 0.42 (95% CI 0.18–0.97) favouring letrozole, consistent with the mechanistic prediction of more monofollicular ovulation.
PCOS subgroups: BMI tertiles in PPCOS II
PPCOS II prespecified analysis by maternal BMI tertile, and BMI proved to be a significant effect modifier (p<0.001 for BMI tertile, p=0.009 for treatment, with no significant interaction between the two factors in the original report). Both BMI and treatment independently predicted live birth.
In the lowest BMI tertile, cumulative live-birth rates were broadly similar across the two arms, in the range of roughly 30% for each agent. In the middle tertile, letrozole pulled ahead. In the highest BMI tertile (BMI greater than approximately 35 kg/m²), the live-birth gap roughly doubled, with letrozole producing about twice as many live births as clomiphene in that subgroup.
A secondary PPCOS II analysis examined metabolic syndrome as a modifier and found that the presence of metabolic syndrome was associated with a lower live-birth rate overall, with a more detrimental effect in clomiphene users. This pattern supports preferential use of letrozole in higher-BMI and metabolically-affected PCOS patients.
Ovulation and clinical pregnancy
Across trials, ovulation rates favour letrozole modestly but consistently. PPCOS II reported cumulative ovulation of 61.7% (letrozole) versus 48.3% (clomiphene), rate ratio 1.28 (95% CI 1.19–1.37). The Tsiami 2021 meta-analysis (26 RCTs) found ovulation RR 1.15 (95% CI 1.08–1.22).
Clinical pregnancy rates parallel the ovulation findings, with relative risks in the range of 1.3–1.5 across the larger meta-analyses. The translation from ovulation to clinical pregnancy is more efficient with letrozole, consistent with a more receptive endometrium during the implantation window.
Safety and side effects
Miscarriage rates are similar between letrozole vs clomiphene across the major sources, with no meta-analysis detecting a significant difference. Side-effect profiles differ qualitatively: clomiphene causes more hot flushes and visual disturbances; letrozole causes more fatigue, headache, and dizziness, all generally mild.
Concerns about teratogenicity dating from a 2005 abstract have not been borne out in subsequent studies. Tulandi and colleagues reported a major anomaly rate of 1.2% with letrozole versus 3.0% with clomiphene in 911 newborns, with cardiac anomalies higher in the clomiphene arm. The Pundir 2021 safety meta-analysis (46 studies, over 6,000 pregnancies) found no increased risk of major congenital anomalies, miscarriage, or adverse neonatal outcomes with letrozole.
Quality and Consistency of Evidence
Evidence quality varies by outcome. The figure that follows summarises certainty ratings derived from the 2022 Cochrane review (GRADE) and the 2023 International PCOS Guideline assessment.
Knowledge Gaps in Letrozole vs Clomiphene Research
Specific named gaps in the evidence
- Optimal letrozole dose and duration. Most trials used 2.5–7.5 mg daily for 5 days; head-to-head dosing comparisons and extended-letrozole protocols remain inadequately powered.
- Clomiphene-resistant subgroup. Whether letrozole produces equivalent outcomes in clomiphene-resistant women, or whether second-line strategies should differ, lacks adequately powered RCTs.
- Long-term offspring data. Beyond neonatal cardiac screening, prospective cohorts of letrozole-conceived offspring through childhood and adolescence are absent.
- Combination therapy. The signal that letrozole plus clomiphene improves ovulation over letrozole alone (Mejia 2019) has not been confirmed in adequately powered live-birth trials.
- Non-PCOS anovulation. Direct head-to-head data in non-PCOS anovulatory infertility are sparse; the AMIGOS trial in unexplained infertility suggested clomiphene may outperform letrozole in that population, but generalisation is limited.
- Cost-effectiveness across health systems. Comparative cost-effectiveness analyses are limited and country-specific; off-label use complicates pricing comparisons.
Practical Implications
The following considerations summarise how the current letrozole vs clomiphene evidence base may inform practice for anovulatory PCOS. They are not directive recommendations; they describe what the evidence supports for clinicians applying current guidelines.
Evidence Supports Letrozole as First-Line in Anovulatory PCOS
For naive PCOS patients without other infertility factors, the cumulative live-birth advantage seen in PPCOS II and confirmed by the 2022 Cochrane review supports letrozole as initial therapy, mirroring 2023 international guideline language.
Letrozole Shows Greater Advantage at Higher BMI
PPCOS II BMI-tertile analyses suggest the live-birth gap between letrozole and clomiphene widens at BMI above approximately 30 kg/m². For higher-BMI PCOS patients, the case for letrozole monotherapy is particularly evidence-based.
Lower Multiple-Gestation Risk Favours Letrozole
Pooled estimates point to roughly half the multiple-pregnancy rate with letrozole compared with clomiphene. For patients who would find a twin pregnancy unacceptable on obstetric grounds, this signal informs shared decision-making.
Counselling on Off-Label Use Remains Relevant
Letrozole is used off-label for ovulation induction in many jurisdictions. The 2023 guideline notes no signal of increased teratogenicity, and the Pundir 2021 safety meta-analysis supports counselling that the safety profile is comparable to clomiphene.
Practice context still matters. The AMIGOS trial signalled that in unexplained (non-PCOS) infertility, letrozole may not match clomiphene for live birth, so the PCOS-specific evidence above should not be generalised uncritically to other anovulatory or normo-ovulatory populations.
Evidence Grade and Bottom Line
Overall Evidence Grade: Moderate to Strong — for letrozole vs clomiphene as first-line ovulation induction in anovulatory PCOS. The position is unlikely to reverse with future data but may be refined by dosing trials and long-term offspring cohorts.
Bottom Line
- Based on the current evidence, letrozole produces higher cumulative live-birth rates than clomiphene citrate in anovulatory PCOS, with the strongest single trial showing 27.5% versus 19.1% across five cycles.
- The advantage is most pronounced at higher BMI, where the live-birth gap roughly doubles compared with lower-BMI tertiles in prespecified subgroup analysis.
- Multiple-gestation rates trend lower with letrozole, consistent with monofollicular development; pooled estimates suggest roughly half the risk.
- Major international guidelines now endorse letrozole as the preferred first-line agent in anovulatory PCOS without other infertility factors, replacing decades of clomiphene-first practice.
- Off-label status, side-effect profile differences, and limited long-term offspring data remain real considerations and should be addressed during informed-consent discussions.
Article Information & References
Disclaimer
For Educational Purposes Only. This is an original evidence synthesis informed by the studies listed below. It does not replace clinical judgement. Drug dosages should be verified against current prescribing information.
References
- Legro RS, Brzyski RG, Diamond MP, et al. Letrozole versus clomiphene for infertility in the polycystic ovary syndrome. N Engl J Med. 2014;371(2):119–129. DOI: 10.1056/NEJMoa1313517
- Franik S, Eltrop SM, Kremer JA, Kiesel L, Farquhar C. Aromatase inhibitors (letrozole) for ovulation induction in infertile women with polycystic ovary syndrome. Cochrane Database Syst Rev. 2022;9(9):CD010287. DOI: 10.1002/14651858.CD010287.pub4
- Teede HJ, Tay CT, Laven JJE, et al. Recommendations from the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. J Clin Endocrinol Metab. 2023;108(10):2447–2469. DOI: 10.1210/clinem/dgad463
- Wang R, Li W, Bordewijk EM, et al. First-line ovulation induction for polycystic ovary syndrome: an individual participant data meta-analysis. Hum Reprod Update. 2019;25(6):717–732. DOI: 10.1093/humupd/dmz029
- Tsiami AP, Goulis DG, Sotiriadis AI, Kolibianakis EM. Higher ovulation rate with letrozole as compared with clomiphene citrate in infertile women with polycystic ovary syndrome: a systematic review and meta-analysis. Hormones (Athens). 2021;20(3):449–461. DOI: 10.1007/s42000-021-00289-z
- Roque M, Tostes ACI, Valle M, Sampaio M, Geber S. Letrozole versus clomiphene citrate in polycystic ovary syndrome: systematic review and meta-analysis. Gynecol Endocrinol. 2015;31(12):917–921. DOI: 10.3109/09513590.2015.1096337
- Diamond MP, Legro RS, Coutifaris C, et al. Letrozole, gonadotropin, or clomiphene for unexplained infertility. N Engl J Med. 2015;373(13):1230–1240. DOI: 10.1056/NEJMoa1414827
- Mejia RB, Summers KM, Kresowik JD, Van Voorhis BJ. A randomized controlled trial of combination letrozole and clomiphene citrate or letrozole alone for ovulation induction in women with polycystic ovary syndrome. Fertil Steril. 2019;111(3):571–578.e1. DOI: 10.1016/j.fertnstert.2018.11.030
- Tulandi T, Martin J, Al-Fadhli R, et al. Congenital malformations among 911 newborns conceived after infertility treatment with letrozole or clomiphene citrate. Fertil Steril. 2006;85(6):1761–1765. DOI: 10.1016/j.fertnstert.2006.03.014
- Pundir J, Achilli C, Bhide P, et al. Risk of foetal harm with letrozole use in fertility treatment: a systematic review and meta-analysis. Hum Reprod Update. 2021;27(3):474–485. DOI: 10.1093/humupd/dmaa055
- Legro RS, Kunselman AR, Brzyski RG, et al. The Pregnancy in Polycystic Ovary Syndrome II (PPCOS II) trial: rationale and design of a double-blind randomized trial of clomiphene citrate and letrozole for the treatment of infertility in women with polycystic ovary syndrome. Contemp Clin Trials. 2012;33(3):470–481. DOI: 10.1016/j.cct.2011.12.005
- Casper RF, Mitwally MF. Review: aromatase inhibitors for ovulation induction. J Clin Endocrinol Metab. 2006;91(3):760–771. DOI: 10.1210/jc.2005-1923