
Sentinel Node Biopsy: When Axillary Staging Can Be Safely Omitted
De-escalation trials are redrawing the boundary between necessary axillary evaluation and avoidable surgery in early breast cancer.
One-Minute Takeaway
Sentinel node biopsy and completion axillary dissection can both be safely omitted in defined patient groups, and the strongest support comes from randomized noninferiority trials.
- After one or two positive sentinel nodes with breast conservation, skipping completion dissection did not lower ten-year survival in the Z0011 trial, and SENOMAC extended the finding to mastectomy and larger tumours.
- When the axilla still needs treatment, axillary radiotherapy matched dissection for regional control while roughly halving lymphedema in AMAROS.
- In small, ultrasound-negative tumours, omitting the biopsy entirely was noninferior for disease-free survival in both SOUND and INSEMA.
- Omission is best supported in older women with low-grade, hormone receptor-positive, HER2-negative disease, where the node result rarely changes treatment.
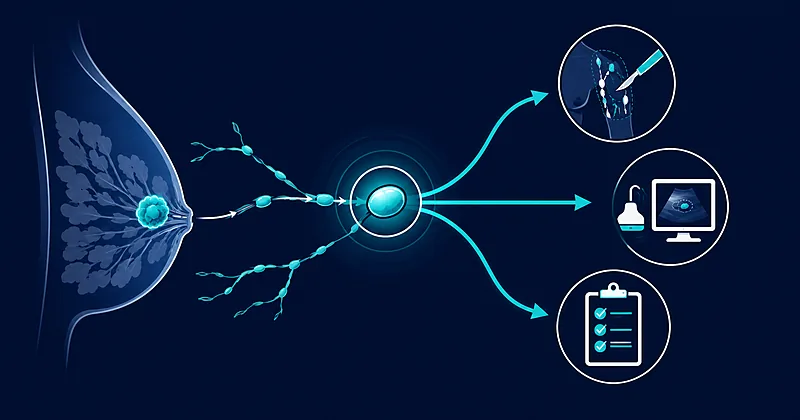
Why Sentinel Node Biopsy Matters
Sentinel node biopsy replaced routine axillary dissection as the way to stage the underarm in clinically node-negative breast cancer. It samples only the first nodes that drain the tumour. A clear sentinel node reliably predicts a clear axilla, which spares most patients a larger operation.
The result still guides treatment for many women. A positive node can influence choices about chemotherapy, endocrine therapy, and regional node irradiation. For that reason the procedure became the default axillary assessment in early breast cancer.
Two decades of randomized data have narrowed the answer. Rather than staging every axilla by the same rule, current evidence separates patients by tumour biology and by whether the node result will alter their plan. The procedure remains valuable, but no longer universal.
The Clinical Problem in Sentinel Node Biopsy
Even a limited axillary operation carries a real morbidity cost. Lymphedema, numbness, shoulder stiffness, and chronic pain follow a meaningful minority of procedures. Completion dissection after a positive node raises these risks substantially.
A parallel shift changed the calculation. Adjuvant therapy is increasingly selected from tumour biology and genomic risk rather than the exact node count. When extra nodal information will not alter treatment, the staging surgery delivers harm without matching benefit.
That mismatch is what the de-escalation trials set out to test. Each asked a focused question: can a specific group safely receive less axillary treatment? The answers now support three distinct strategies, examined below.
Available Approaches
Three strategies reduce axillary intervention, and each was tested in a randomized noninferiority trial. They differ in who they apply to and in how much surgery they remove. The table summarises the pivotal evidence, and the sections that follow examine each in turn.
| Trial (year) | Design | N | Population | Comparison | Key result |
|---|---|---|---|---|---|
| Z0011 (2017) | RCT, noninferiority | 891 | cT1–2, cN0, 1–2 positive sentinel nodes; breast conservation + whole-breast RT | ALND vs no further axillary surgery | 10-yr OS 86.3% vs 83.6%; HR 0.85 (1-sided 95% CI 0–1.16), noninferior |
| IBCSG 23-01 (2013) | RCT, noninferiority | 934 | Tumour ≤5 cm, cN0, sentinel micrometastases (≤2 mm) | ALND vs no ALND | 5-yr DFS 87.8% vs 84.4%; HR 0.78 (95% CI 0.55–1.11), noninferior |
| SENOMAC (2024) | RCT, noninferiority | 2,540 | cN0, T1–T3, 1–2 sentinel macrometastases; mastectomy allowed | Completion ALND vs SLNB only | 5-yr RFS 89.7% vs 88.7%; HR 0.89 (95% CI 0.66–1.19), noninferior |
| AMAROS (2023) | RCT, noninferiority | 1,425 | cT1–2, cN0, positive sentinel node | ALND vs axillary RT | 10-yr axillary recurrence 0.93% vs 1.82%; lymphedema 24.5% vs 11.9% |
| SOUND (2023) | RCT, noninferiority | 1,405 | Tumour ≤2 cm, cN0, negative axillary ultrasound | SLNB vs no axillary surgery | 5-yr distant DFS 94.7% vs 93.3% (P=.30), noninferior |
| INSEMA (2025) | RCT, noninferiority | 4,858 | cN0, T1–2, scheduled for breast conservation | SLNB vs no axillary surgery | 5-yr IDFS 91.7% vs 91.9%; HR 0.91 (95% CI 0.73–1.14), noninferior |
Omitting Completion Axillary Dissection
The first strategy keeps the sentinel biopsy but skips the completion dissection when a node is positive. Z0011 tested this in women with one or two positive nodes and breast conservation. Overall survival at ten years was noninferior without dissection, and regional recurrence stayed low in both arms.
SENOMAC widened the question to mastectomy and to tumours up to T3. Recurrence-free survival remained noninferior with biopsy alone across that broader population. Most patients in the trial also received nodal radiotherapy, so the result reflects omission of surgery, not of all axillary treatment.
IBCSG 23-01 addressed the smallest deposits, the micrometastatic nodes of two millimetres or less. Disease-free survival was noninferior without dissection, and the ten-year follow-up held. Together these three trials cover limited nodal disease from micrometastases up to two macrometastatic nodes.
Substituting Axillary Radiotherapy for Dissection
The second strategy treats the axilla without removing it. AMAROS randomized node-positive patients to dissection or axillary radiotherapy. Regional control was comparable through ten years, with very low recurrence in both arms.
Radiotherapy roughly halved the lymphedema rate compared with dissection. That morbidity advantage makes it the preferred option when the axilla warrants treatment but surgery is undesirable. It is especially relevant after mastectomy, where completion dissection adds considerable arm morbidity.
The trade-off is not zero. AMAROS recorded more second primary cancers after radiotherapy over ten years. The choice therefore weighs a clear reduction in arm morbidity against a small radiation-associated risk.
Omitting Sentinel Node Biopsy Entirely
The third strategy removes the biopsy itself. SOUND tested this in tumours of two centimetres or less with a negative axillary ultrasound. Distant disease-free survival was noninferior without any axillary surgery.
INSEMA reached the same conclusion in a larger cohort scheduled for breast conservation. Invasive disease-free survival was noninferior with omission, and overall survival was similar. Axillary recurrence stayed at or below one percent in both arms.
The benefit concentrates in a low-risk profile. The INSEMA investigators pointed to women aged fifty or older with low-grade, hormone receptor-positive, HER2-negative, clinical T1 disease. In these patients the node result seldom changes systemic therapy.
Comparative Analysis
The three approaches sit at different points on the treatment path. Omitting dissection applies once a node is known to be positive. Omitting the biopsy applies before any nodal information exists.
Axillary radiotherapy sits between them. It treats the axilla without removing it, and it is most useful when nodal treatment is indicated but surgery carries high morbidity. The population overlap across the strategies is partial rather than complete.
The safe boundary tracks tumour biology. It widens with small size, low grade, and hormone receptor-positive, HER2-negative disease. It narrows with larger tumours, higher grade, and more aggressive subtypes, where nodal status carries more weight.
Quality and Consistency of the Evidence
The strength of the evidence differs by outcome and by population. The strongest signals are concordant across several randomized trials; the weaker ones rest on shorter follow-up or narrower cohorts.
- Strong — survival after omitting completion dissection in limited nodal disease. Concordant across Z0011, SENOMAC, and IBCSG 23-01, all randomized noninferiority trials.
- Strong — regional control with axillary radiotherapy versus dissection. Demonstrated at ten years in AMAROS, with low recurrence in both arms.
- Moderate — omitting the biopsy entirely. Consistent across SOUND and INSEMA, but follow-up is shorter and cohorts were enriched for low-risk, hormone receptor-positive disease.
- Moderate — omission in mastectomy or larger-tumour macrometastasis. Supported by SENOMAC, though the mastectomy subgroup is smaller and mostly received nodal radiotherapy.
- Limited — omitting the biopsy in higher-risk biology. Grade 3, HER2-positive, or triple-negative disease, and larger tumours, are not established by the current omission trials.
What the Evidence Does Not Show
- It does not show the biopsy can be skipped in higher-risk disease. SOUND and INSEMA enrolled mostly small, low-grade, hormone receptor-positive tumours.
- It does not fully resolve the macrometastasis-plus-mastectomy question. INSEMA’s second randomization showed a non-significant signal toward worse invasive disease-free survival with biopsy alone than with dissection (HR 1.69, 95% CI 0.98–2.94), and this preliminary finding warrants caution.
- It does not establish very-long-term outcomes for biopsy omission, since the longest reported follow-up is around six years.
- It does not apply to the neoadjuvant setting, where nodal response after chemotherapy follows different rules.
- It does not remove the need for accurate axillary ultrasound, which underpins safe omission of the biopsy.
Practical Implications
The trials translate into a graded set of options, framed by what the evidence supports rather than by fixed directives.
- For one or two positive sentinel nodes with breast conservation and planned whole-breast radiation, completion dissection can reasonably be omitted. Regional control and survival were preserved in Z0011 and later trials.
- When the axilla warrants treatment but surgery is undesirable, axillary radiotherapy is a lower-morbidity alternative to dissection. It matched surgical control in AMAROS with about half the lymphedema.
- For small, ultrasound-negative, biologically favourable tumours where nodal status will not change systemic therapy, the biopsy itself may be omitted. SOUND and INSEMA support this in carefully selected patients.
- In women aged seventy or older with hormone receptor-positive, HER2-negative, node-negative disease, professional guidance already supports routine omission of the biopsy.
- Accurate preoperative axillary imaging underpins every omission decision and should be documented before surgery is planned.
Evidence Grade and Bottom Line
Overall grade: High for omitting completion dissection in limited nodal disease; Moderate for omitting the biopsy in low-risk small tumours.
- Less axillary surgery is now the evidence-based default for many women with early breast cancer.
- The safe boundary is defined by tumour biology and by whether the node result will change treatment.
- Higher-risk disease, larger tumours, and the neoadjuvant setting remain outside the current omission evidence and still call for standard staging.
Article Information and References
- Giuliano AE, Ballman KV, McCall L, et al. Effect of Axillary Dissection vs No Axillary Dissection on 10-Year Overall Survival Among Women With Invasive Breast Cancer and Sentinel Node Metastasis: The ACOSOG Z0011 (Alliance) Randomized Clinical Trial. JAMA. 2017;318(10):918–926. DOI: https://doi.org/10.1001/jama.2017.11470
- de Boniface J, Filtenborg Tvedskov T, Rydén L, et al. Omitting Axillary Dissection in Breast Cancer with Sentinel-Node Metastases. N Engl J Med. 2024;390(13):1163–1175. DOI: https://doi.org/10.1056/NEJMoa2313487
- Reimer T, Stachs A, Veselinovic K, et al. Axillary Surgery in Breast Cancer — Primary Results of the INSEMA Trial. N Engl J Med. 2025;392(11):1051–1064. DOI: https://doi.org/10.1056/NEJMoa2412063
- Gentilini OD, Botteri E, Sangalli C, et al. Sentinel Lymph Node Biopsy vs No Axillary Surgery in Patients With Small Breast Cancer and Negative Results on Ultrasonography of Axillary Lymph Nodes: The SOUND Randomized Clinical Trial. JAMA Oncol. 2023;9(11):1557–1564. DOI: https://doi.org/10.1001/jamaoncol.2023.3759
- Bartels SAL, Donker M, Poncet C, et al. Radiotherapy or Surgery of the Axilla After a Positive Sentinel Node in Breast Cancer: 10-Year Results of the Randomized Controlled EORTC 10981-22023 AMAROS Trial. J Clin Oncol. 2023;41(12):2159–2165. DOI: https://doi.org/10.1200/JCO.22.01565
- Galimberti V, Cole BF, Zurrida S, et al. Axillary dissection versus no axillary dissection in patients with sentinel-node micrometastases (IBCSG 23-01): a phase 3 randomised controlled trial. Lancet Oncol. 2013;14(4):297–305. DOI: https://doi.org/10.1016/S1470-2045(13)70035-4
- Galimberti V, Cole BF, Viale G, et al. Axillary dissection versus no axillary dissection in patients with breast cancer and sentinel-node micrometastases (IBCSG 23-01): 10-year follow-up of a randomised, controlled phase 3 trial. Lancet Oncol. 2018;19(10):1385–1393. DOI: https://doi.org/10.1016/S1470-2045(18)30380-2
- Donker M, van Tienhoven G, Straver ME, et al. Radiotherapy or surgery of the axilla after a positive sentinel node in breast cancer (EORTC 10981-22023 AMAROS): a randomised, multicentre, open-label, phase 3 non-inferiority trial. Lancet Oncol. 2014;15(12):1303–1310. DOI: https://doi.org/10.1016/S1470-2045(14)70460-7
- Tinterri C, Canavese G, Gatzemeier W, et al. Sentinel lymph node biopsy versus axillary lymph node dissection in breast cancer patients undergoing mastectomy with one to two metastatic sentinel lymph nodes: sub-analysis of the SINODAR-ONE multicentre randomized clinical trial. Br J Surg. 2023;110(9):1143–1152. DOI: https://doi.org/10.1093/bjs/znad215
- Sávolt Á, Péley G, Polgár C, et al. Eight-year follow up result of the OTOASOR trial: The Optimal Treatment Of the Axilla — Surgery Or Radiotherapy after positive sentinel lymph node biopsy in early-stage breast cancer. Eur J Surg Oncol. 2017;43(4):672–679. DOI: https://doi.org/10.1016/j.ejso.2016.12.011
- Park KU, Somerfield MR, Anne N, et al. Sentinel Lymph Node Biopsy in Early-Stage Breast Cancer: ASCO Guideline Update. J Clin Oncol. 2025. DOI: https://doi.org/10.1200/JCO-25-00099